



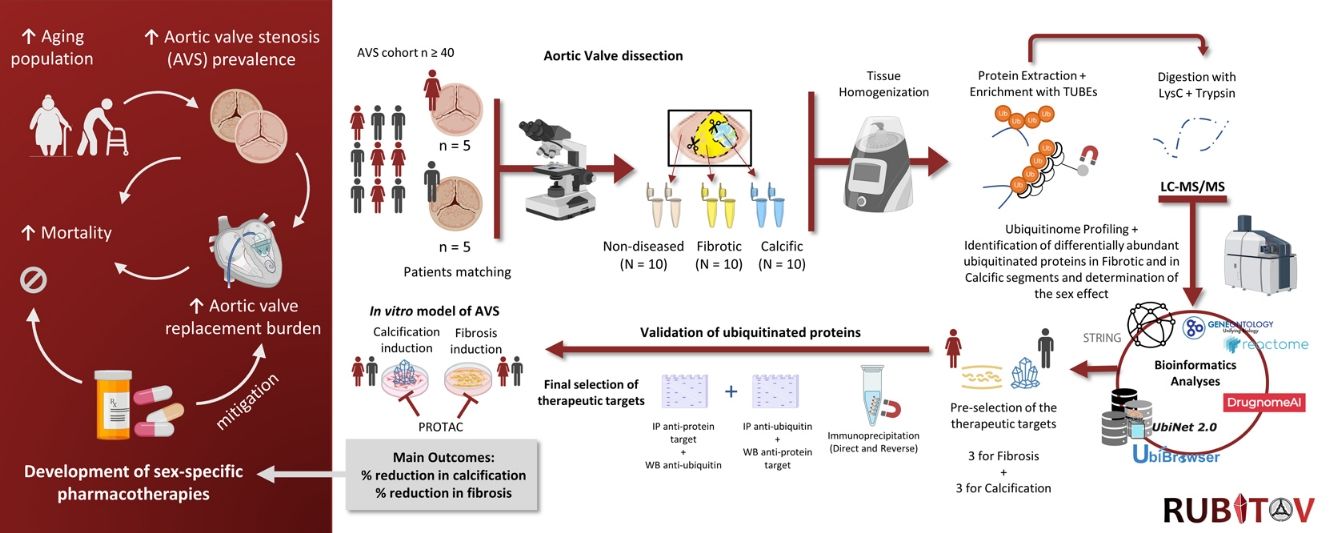
Aortic valve stenosis (AVS) is a growing healthcare burden and a paradigmatic example of sexual dimorphism in cardiovascular disease. Degenerative AVS results from valve fibrosis and calcification, affecting mainly women and men, respectively. Despite >20 years of clinical trials testing drugs such as statins, actaciguat, or vitamin K, aortic valve replacement (AVR) remains the only effective treatment. Evidence points to the relevance of protein ubiquitination in AVS progression, yet a holistic characterization of the ubiquitinome using mass spectrometry (MS) is lacking. Such an approach could uncover new targets for proteolysis-targeting chimeras (PROTACs), which remain underexplored in cardiovascular disease. RUBITAV aims to characterize the ubiquitinome landscape associated with fibrotic and calcific transformation of the valve and unveil sex-specific therapeutic targets. RUBITAV also aims to test the effect of modulating ubiquitinated proteins with PROTACs to mitigate fibrosis and calcification.
MethodsAortic valves will be collected from a sex-balanced and comorbidities-matched AVS cohort and dissected into morphologically normal, fibrotic, and calcified sections. Following protein extraction, ubiquitinated proteins will be enriched and quantified by MS. Putative sex-specific targets identified using bioinformatics will be modulated in vitro with PROTACs using valve interstitial cells maintained under pro-fibrotic or pro-calcific conditions. The primary outcome is defined as the % reduction in fibrosis (females) and calcification (males).
ResultsNot applicable.
ConclusionRUBITAV is expected to advance our understanding of the role of protein ubiquitination in AVS, identify new sex-specific therapeutic targets, and pave the way for the application of PROTACs in the treatment of AVS.
A estenose valvular aórtica (EVA) é um exemplo paradigmático do dimorfismo sexual nas doenças cardiovasculares. A EVA degenerativa resulta da fibrose e da calcificação da válvula, afetando principalmente mulheres e homens, respetivamente. Apesar de >20 anos de ensaios clínicos com estatinas, ataciguat ou vitamina K, a substituição da válvula aórtica (SVA) continua a ser o único tratamento eficaz. As evidências apontam para a relevância da ubiquitinação de proteínas na progressão da EVA, mas ainda não foi feita uma caracterização holística do ubiquitinoma, que poderá revelar novos alvos para proteolysis-targeting chimeras (PROTACs), praticamente inexploradas em doenças cardiovasculares. No RUBITAV iremos caracterizar o ubiquitinoma associado à transformação fibrótica e calcífica da válvula para identificar alvos terapêuticos específicos por sexo. Depois testaremos o efeito da modulação de proteínas ubiquitinadas com PROTACs para mitigar a fibrose e a calcificação.
MétodosVálvulas obtidas de uma coorte de EVA, emparelhadas por sexo e comorbidades, serão dissecadas em secções não doentes, fibróticas e calcificadas. Após a extração da proteína, as espécies ubiquitinadas serão enriquecidas e quantificadas por espectrometria de massa. Os potenciais alvos, específicos por sexo, serão modulados in vitro com PROTACs usando células intersticiais valvulares mantidas em condições pró-fibróticas ou pró-calcificantes. O indicador primário será a % de redução da fibrose (mulheres) e da calcificação (homens).
ResultadosNão aplicável.
ConclusãoEspera-se que o RUBITAV melhore a nossa compreensão do papel da ubiquitinação na EVA, identifique novos alvos terapêuticos específicos por sexo e abra caminho para a aplicação de PROTACs no tratamento da EVA.

Aortic valve stenosis (AVS) is the valve disease leading to most valve surgeries and catheter interventions in Europe, with a rising prevalence due to an ageing population.1 An alarming scenario is anticipated in Portugal regarding the management of this disease over the coming decades, making it a priority area of intervention, according to the Strategic Plan for Cardiovascular Health in Portugal (PESCP-SPC), an initiative led by the Portuguese Society of Cardiology.2
Aortic valve stenosis is the advanced stage of aortic valve sclerosis and is characterized by a fibrocalcific remodeling of the aortic valve (AV). In AVS, the AV progressively thickens and narrows, obstructing blood outflow and increasing left ventricle pressure afterload, which triggers left ventricular hypertrophic remodeling – a substrate of heart failure.3 AVS is initially silent and diagnosed by imaging (echocardiography, cardiac computed tomography – CCT) after valve fibro-calcification has become significant. Angina, syncope, and other heart failure symptoms remain the main indications for intervention.3
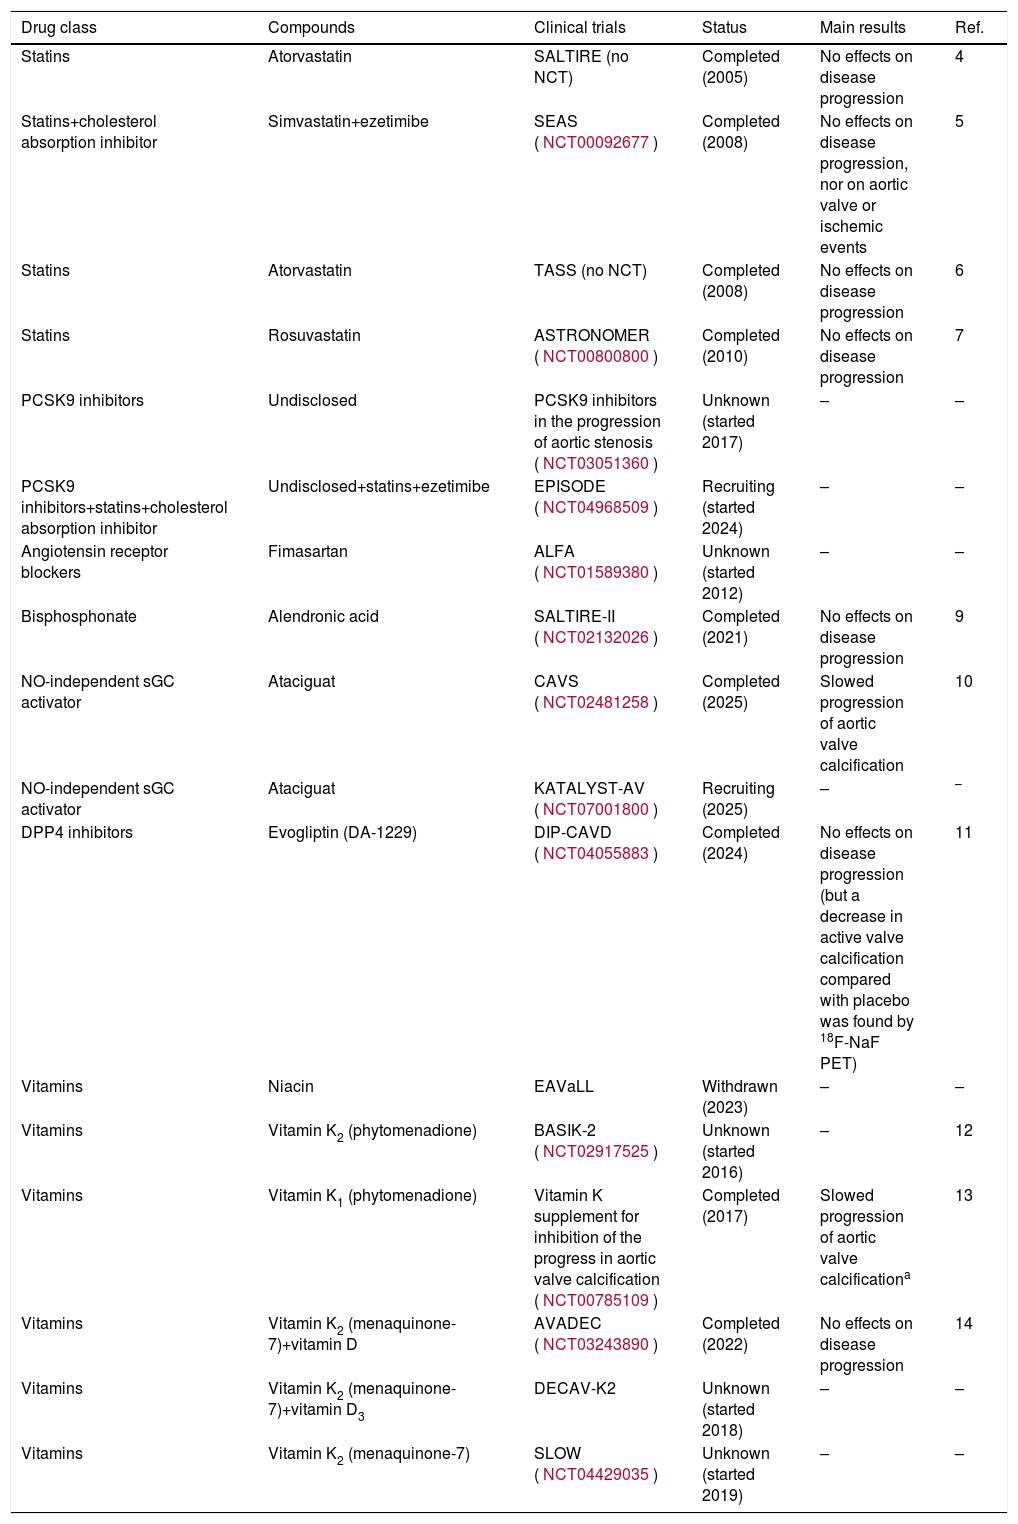
Aortic valve sclerosis, the underlying pathology of degenerative AVS, shares many pathological features with coronary artery disease, including lipoprotein deposition and oxidation, inflammation, monocytes and T cell infiltration, and risk factors, such as hypertension, dyslipidemia, and diabetes. Therefore, initial trials aiming at treating AVS pharmacologically tried to repurpose atherosclerosis-directed therapies. This and other examples reaching clinical testing are summarized in Table 1. Despite the promise, statin repurposing trials (e.g., SALTIRE,4 SEAS,5 TASS,6 ASTRONOMER7) have failed to revert or stall AVS. Other more recent cholesterol-lowering drugs, such as PCSK9 inhibitors, are also promising, but only two trials are currently known, one with unknown status (NCT03051360) and the other still recruiting patients (NCT04968509). Antihypertensive drugs or bisphosphonates also failed to show benefit in clinical trials.8,9
Summary of clinical trials aiming to treat or mitigate aortic valve stenosis using pharmacotherapeutic approaches.
| Drug class | Compounds | Clinical trials | Status | Main results | Ref. |
|---|---|---|---|---|---|
| Statins | Atorvastatin | SALTIRE (no NCT) | Completed (2005) | No effects on disease progression | 4 |
| Statins+cholesterol absorption inhibitor | Simvastatin+ezetimibe | SEAS (NCT00092677) | Completed (2008) | No effects on disease progression, nor on aortic valve or ischemic events | 5 |
| Statins | Atorvastatin | TASS (no NCT) | Completed (2008) | No effects on disease progression | 6 |
| Statins | Rosuvastatin | ASTRONOMER (NCT00800800) | Completed (2010) | No effects on disease progression | 7 |
| PCSK9 inhibitors | Undisclosed | PCSK9 inhibitors in the progression of aortic stenosis (NCT03051360) | Unknown (started 2017) | – | – |
| PCSK9 inhibitors+statins+cholesterol absorption inhibitor | Undisclosed+statins+ezetimibe | EPISODE (NCT04968509) | Recruiting (started 2024) | – | – |
| Angiotensin receptor blockers | Fimasartan | ALFA (NCT01589380) | Unknown (started 2012) | – | – |
| Bisphosphonate | Alendronic acid | SALTIRE-II (NCT02132026) | Completed (2021) | No effects on disease progression | 9 |
| NO-independent sGC activator | Ataciguat | CAVS (NCT02481258) | Completed (2025) | Slowed progression of aortic valve calcification | 10 |
| NO-independent sGC activator | Ataciguat | KATALYST-AV (NCT07001800) | Recruiting (2025) | – | – |
| DPP4 inhibitors | Evogliptin (DA-1229) | DIP-CAVD (NCT04055883) | Completed (2024) | No effects on disease progression (but a decrease in active valve calcification compared with placebo was found by 18F-NaF PET) | 11 |
| Vitamins | Niacin | EAVaLL | Withdrawn (2023) | – | – |
| Vitamins | Vitamin K2 (phytomenadione) | BASIK-2 (NCT02917525) | Unknown (started 2016) | – | 12 |
| Vitamins | Vitamin K1 (phytomenadione) | Vitamin K supplement for inhibition of the progress in aortic valve calcification (NCT00785109) | Completed (2017) | Slowed progression of aortic valve calcificationa | 13 |
| Vitamins | Vitamin K2 (menaquinone-7)+vitamin D | AVADEC (NCT03243890) | Completed (2022) | No effects on disease progression | 14 |
| Vitamins | Vitamin K2 (menaquinone-7)+vitamin D3 | DECAV-K2 | Unknown (started 2018) | – | – |
| Vitamins | Vitamin K2 (menaquinone-7) | SLOW (NCT04429035) | Unknown (started 2019) | – | – |
Abbreviations: DPP4: dipeptidyl peptisase-4; NCT: national clinical trial; NO: nitric oxide; PCSK9: proprotein convertase subtilisin/kexin type 9; PET: positron emission tomography; sGC: soluble guanylate cyclase.
There have been, however, modest advances with other strategies. Evogliptin, a dipeptidyl peptidase-4 inhibitor, did not significantly affect disease progression, but reduced active calcium deposition measured by positron emission tomography.11 A 6-month treatment with ataciguat, a NO-independent soluble guanylyl cyclase activator, slowed the progression of AV calcification but failed to translate into an improvement in valvular function in patients with moderate AVS.10 Finally, trials testing the efficacy of vitamin K are amassing. Vitamin K is an essential cofactor for the carboxylation of the matrix-Gla protein (MGP), a post-translational modification (PTM) required for its maximal inhibition of calcium precipitation. Most vitamin K trials are of unknown status, but results are known for two. In one trial, which combined vitamin K with vitamin D, no effect on valve calcification was observed.14 In a small proof-of-concept trial, vitamin K was found to slow the progression of AV calcification over a 12-month period. Patients supplemented with vitamin K showed an increase of 10% in AV calcium score versus 22% in the placebo group.13 Its relevance is further supported by studies showing that vitamin K antagonists, such as warfarin, but not the new oral anticoagulants, such as rivaroxaban, significantly increase AV calcification score.15 Currently, no pharmacotherapy is implemented to reverse or halt AVS, making AV replacement (AVR), by surgery (SAVR) or transcatheter implantation (TAVI), the only effective treatment despite the significant costs, long-term complications, and the clinical importance of timely intervention for optimal outcomes.3
The development of pharmacotherapies for AVS is even more challenging when accounting for the outstanding sexual dimorphism in the AV. Men exhibit more calcification, while women exhibit more fibrosis for the same clinical severity.16 According to the latest European guidelines (2025), sex-specific cut-offs for calcium score assessed by multi-slice computed tomography were reiterated: men with scores >2000 and women with scores >1200 Agatston units are likely to have severe AVS, while scores >3000 in men and >1600 in women indicate a very high likelihood of severe AVS.17 One possible reason for this dimorphism is the higher resistance of women's valvular interstitial cells (VICs) to apoptosis, due to a higher expression of the apoptosis suppressant B-cell lymphoma 2 and lower expression of annexin V.18 Male VICs, in turn, show higher calcification rates when grown in osteogenic media, with a higher expression of bone morphogenetic protein 2 and alkaline phosphatase.18,19 Through AV proteomics, we have shown that sexual dimorphism is further evidenced by greater infiltration of leukocytes, lower protection against oxidative stress in men, and a higher degree of fibrotic remodeling in women. Hence, a sex-tailored approach is of paramount importance.20
Traditionally, the development of pharmacotherapies has been grounded in epidemiological (e.g., lp(a) association with AVS progression in the case of PCSK9 inhibition, NCT03051360) or experimental observations (e.g., bisphosphonates reducing valvular calcification in preclinical models, SALTIRE-II9). Yet, therapeutic targets can be uncovered using unbiased omics approaches. The extracellular matrix-associated fibronectin type III domain containing 1 (FNDC1) and the matrix-remodeling-associated protein 5 (MXRA5) were unveiled by proteomics.21 Within the proteomics domain, therapeutic specificity can be bolstered by targeting protein PTMs, as these are critical modulators of protein function. Despite the study's small size (72 participants), the success of vitamin K, in the trial led by Brandenburg et al.13, in reducing AV calcification was bound to a higher rate of MGP carboxylation (a PTM), as confirmed by a decreased circulation of the undercarboxylated MGP proteoform (less protective against matrix calcification). This further demonstrates the potential of targeting PTMs for developing therapies focused on mitigating or reversing valve fibrosis and calcification.
PTMs remain a major gap in AVS research. We and others have shown the potential of PTM profiling for opening new treatment perspectives. S-nitrosylation of USP9X (ubiquitin-specific peptidase 9, X-linked) has, for instance, been shown to prevent calcification in vitro.22 We identified DYRK1A as a target for post-AVR incomplete myocardial reverse remodeling through phosphoproteomics.23 In particular, the modulation of protein ubiquitination holds promise for AVS treatment. For example, the transcription factor FOXO1, downregulated in AVS, leads to the degradation of the osteogenesis-inducer Runt-related transcription factor 2 (RUNX2) by promoting its ubiquitination by the E3 ubiquitin ligase (E3UL) SMAD-specific E3 ubiquitin ligase 2 (SMURF2).24 Another example is the Murine Double Minute 2 (MDM2), which promotes the ubiquitination and subsequent degradation of dipeptidyl-peptidase 4 (DPP4), helping prevent AV calcification.25 The underlying mechanism likely involves limiting the DPP4-driven insulin-like growth factor 1 proteolysis (another PTM).26 The inhibition of DPP4 in the DIP-CAVD trial was one of the few trials that significantly reduced active calcification,11 further suggesting that promoting DPP4 ubiquitination-degradation could be a promising therapeutic avenue in AVS. Although few examples of clinical trials have shown an effect on mitigating AVS disease, the evidence from vitamin K and DPP4 inhibition trials points to a promising potential of therapies centered on PTM regulation in tackling AVS progression.
Given the dysregulation of ubiquitination in AVS, developing or implementing drugs that target this PTM is of the utmost importance. There is an untapped potential for applying PROTACs (proteolysis-targeting chimeras) in the treatment of AVS, or, in fact, in any form of atherosclerotic disease. PROTACs are hijackers of the ubiquitin–proteasome system (UPS) that facilitate E3UL binding and target protein degradation.27 PROTACs have shown promise in treating cancer, having reached clinical trials several times.28 However, in the field of atherosclerotic cardiovascular diseases, PROTACs remain in an experimental stage with minimal evidence available. Examples include a von Hippel-Lindau (VHL)-based PROTAC for the simultaneous reduction of cholesterol and degradation of the 3-hydroxy-3-methylglutaryl coenzyme A reductase (compensatorily upregulated upon statin treatment) in a mouse model of hypercholesterolaemia29 and a transcription intermediary factor 1-alpha (TRIM-24)-based PROTAC to reduce atherosclerotic plaque accumulation and polarization of the macrophages to the M2 phenotype, in an ApoE−/− mouse model of atherosclerosis.30 Unlike the oncological field, no PROTAC has entered clinical trials for cardiovascular disease.
In summary, pharmacological treatment of AVS is imperative in the coming decades; otherwise, the need for AVR will escalate, overwhelming healthcare services even further. In this regard, profiling the AV ubiquitinome specifically in relation to fibrosis in women and calcification in men represents a promising avenue for uncovering new sex-specific therapeutic targets. The application of PROTACs on such targets, fueled by the advancements in the oncology field, may hold the key to developing new pharmacotherapies to mitigate the disease and prevent or delay AVR.
ObjectivesThe primary objective of RUBITAV is to profile the ubiquitinome associated with valve fibrosis and calcification, affecting mainly women and men, respectively, to uncover a potential new path in the treatment of AVS in a sex-specific manner. RUBITAV is divided into two main parts: the first is hypothesis-generating, and the second is hypothesis-driven.
Part ARUBITAV first aims to answer the following question: what are the differences in the ubiquitinome landscape associated with fibrotic (women-specific) and calcific (men-specific) AV remodeling?
For this part, we will characterize the ubiquitinome landscape of fibrotic and calcified sections of the AV and uncover the sex differences using a mass spectrometry (MS)-based proteomics approach. We are firmly convinced that this approach will identify new sex-specific therapeutic targets to hinder AVS progression, while giving insights into the molecular underpinnings of the fibrotic and calcific transformation of the valve. AVs will be collected from patients undergoing AVR (n>40). For the exploratory analysis of AVS ubiquitinome, 10 patients (5 men, 5 women) will be matched to minimize the effect of confounders (age, comorbidities, and cardiovascular risk factors) and maximize the translational value of the analysis. AVs will be dissected into non-diseased (ND), fibrotic, and calcific sections, and the proteins will be extracted from these sections. ND sections will be used as in-patient controls. Ubiquitinated proteins will be enriched from 30 matched fractions (3 sections/patient) and analyzed by MS. We will focus on polyubiquitinated species, because polyubiquitination is the canonical signal for proteasomal degradation, while mono-ubiquitination serves other non-proteolytic regulatory functions,31 and PROTACs specifically hijack the ubiquitin–proteasome axis. The effect of sex on the difference in polyubiquitinated proteins between fibrotic or calcific tissue and ND controls will be gauged by analysis of covariance (ANCOVA) while adjusting for the unmatched variables. Bioinformatics will prioritize the putative therapeutic targets (ubiquitinated proteins, E3UL or deubiquitinases, DUB).
The specific aims of Part A are to:
- 1.
Recruit at least 40 AVS patients undergoing elective surgical valve replacement. Collect demographics, echocardiographic, and CCT-derived calcium score data. Obtain the AV from surgery [Task 1];
- 2.
Match at least 10 patients for age, comorbidities, and disease severity [Task 1];
- 3.
Dissect the valves into three sections (non-diseased, fibrotic, and calcific sections) [Task 1];
- 4.
Extract the proteins, enrich polyubiquitinated proteins with TUBEs (tandem ubiquitin binding entities) [Task 2];
- 5.
Digest and quantify the ubiquitinated proteins by MS and identify the dysregulated proteins (fold-change in expression and the estimated effect by sex) in fibrotic and calcific sections [Task 2];
- 6.
Prioritize 3 therapeutic targets for fibrosis and 3 for calcification by integrated bioinformatics analysis, encompassing functional enrichment analysis, protein-protein interaction analysis, prediction of E3UL and DUB, and prediction of their druggability by PROTACs [Task 3];
- 7.
Validate the differentially expressed ubiquitinated proteins, regarded as top-tier targets, with an independent approach (pull-down assay of the target proteins and subsequent Western blotting (WB) for ubiquitin and vice-versa) [Task 4].
We hypothesize that fibrosis and calcification, the two main disease hallmarks, can be mitigated by modulating dysregulated ubiquitinated proteins (uncovered in Part A) using PROTACs, drugs designed to redirect the UPS towards the degradation of specific proteins.
In this part, we will assess the effect of targeting specific polyubiquitinated proteins or regulatory enzymes on fibrosis and calcification. We plan to use PROTACs to modulate the levels of the dysregulated proteins. PROTACs are available for >440 targets32 but have not yet been trialed in the cardiovascular setting. The primary outcome is defined as the reduction (%) in fibrosis or calcification in cells treated with the drug relative to cells treated in parallel with the respective vehicle for the same time. The effect of PROTACs will be tested in vitro, as in vivo models such as the murine and leporine do not precisely replicate human AVS and require the use of cholesterol-rich diets or gene knockout strategies, which introduce confounding factors (e.g., by stimulating coronary atherosclerosis).33 Although closer to humans, swine models, which develop AVS with age, require a lengthy protocol or, alternatively, the implementation of a high-cholesterol diet for faster phenotype development.33 Therefore, we have grounds to believe that utilizing human AV-derived VICs is an optimal strategy to bypass inter-species confounding factors and facilitate the translation to clinics. Specifically, we believe that subjecting male and female VICs to pro-fibrotic and pro-osteogenic stimuli, and modulating the targets derived from Part A, will provide the necessary proof-of-concept for identifying novel sex-specific therapeutic targets for AVS, which can subsequently be tested in vivo.
The specific aims of Part B are to:
- 1.
Assess the effect of targeting specific proteins with PROTACs on fibrosis in male and female VICs grown under pro-fibrotic conditions (levels of the target protein, extracellular matrix accumulation, and fibrosis markers) [Task 5].
- 2.
Assess the effect of targeting specific proteins with PROTACs on calcification in male and female VICs grown under osteogenic conditions (levels of the target protein, hydroxyapatite mineral accumulation, and calcification markers) [Task 5].
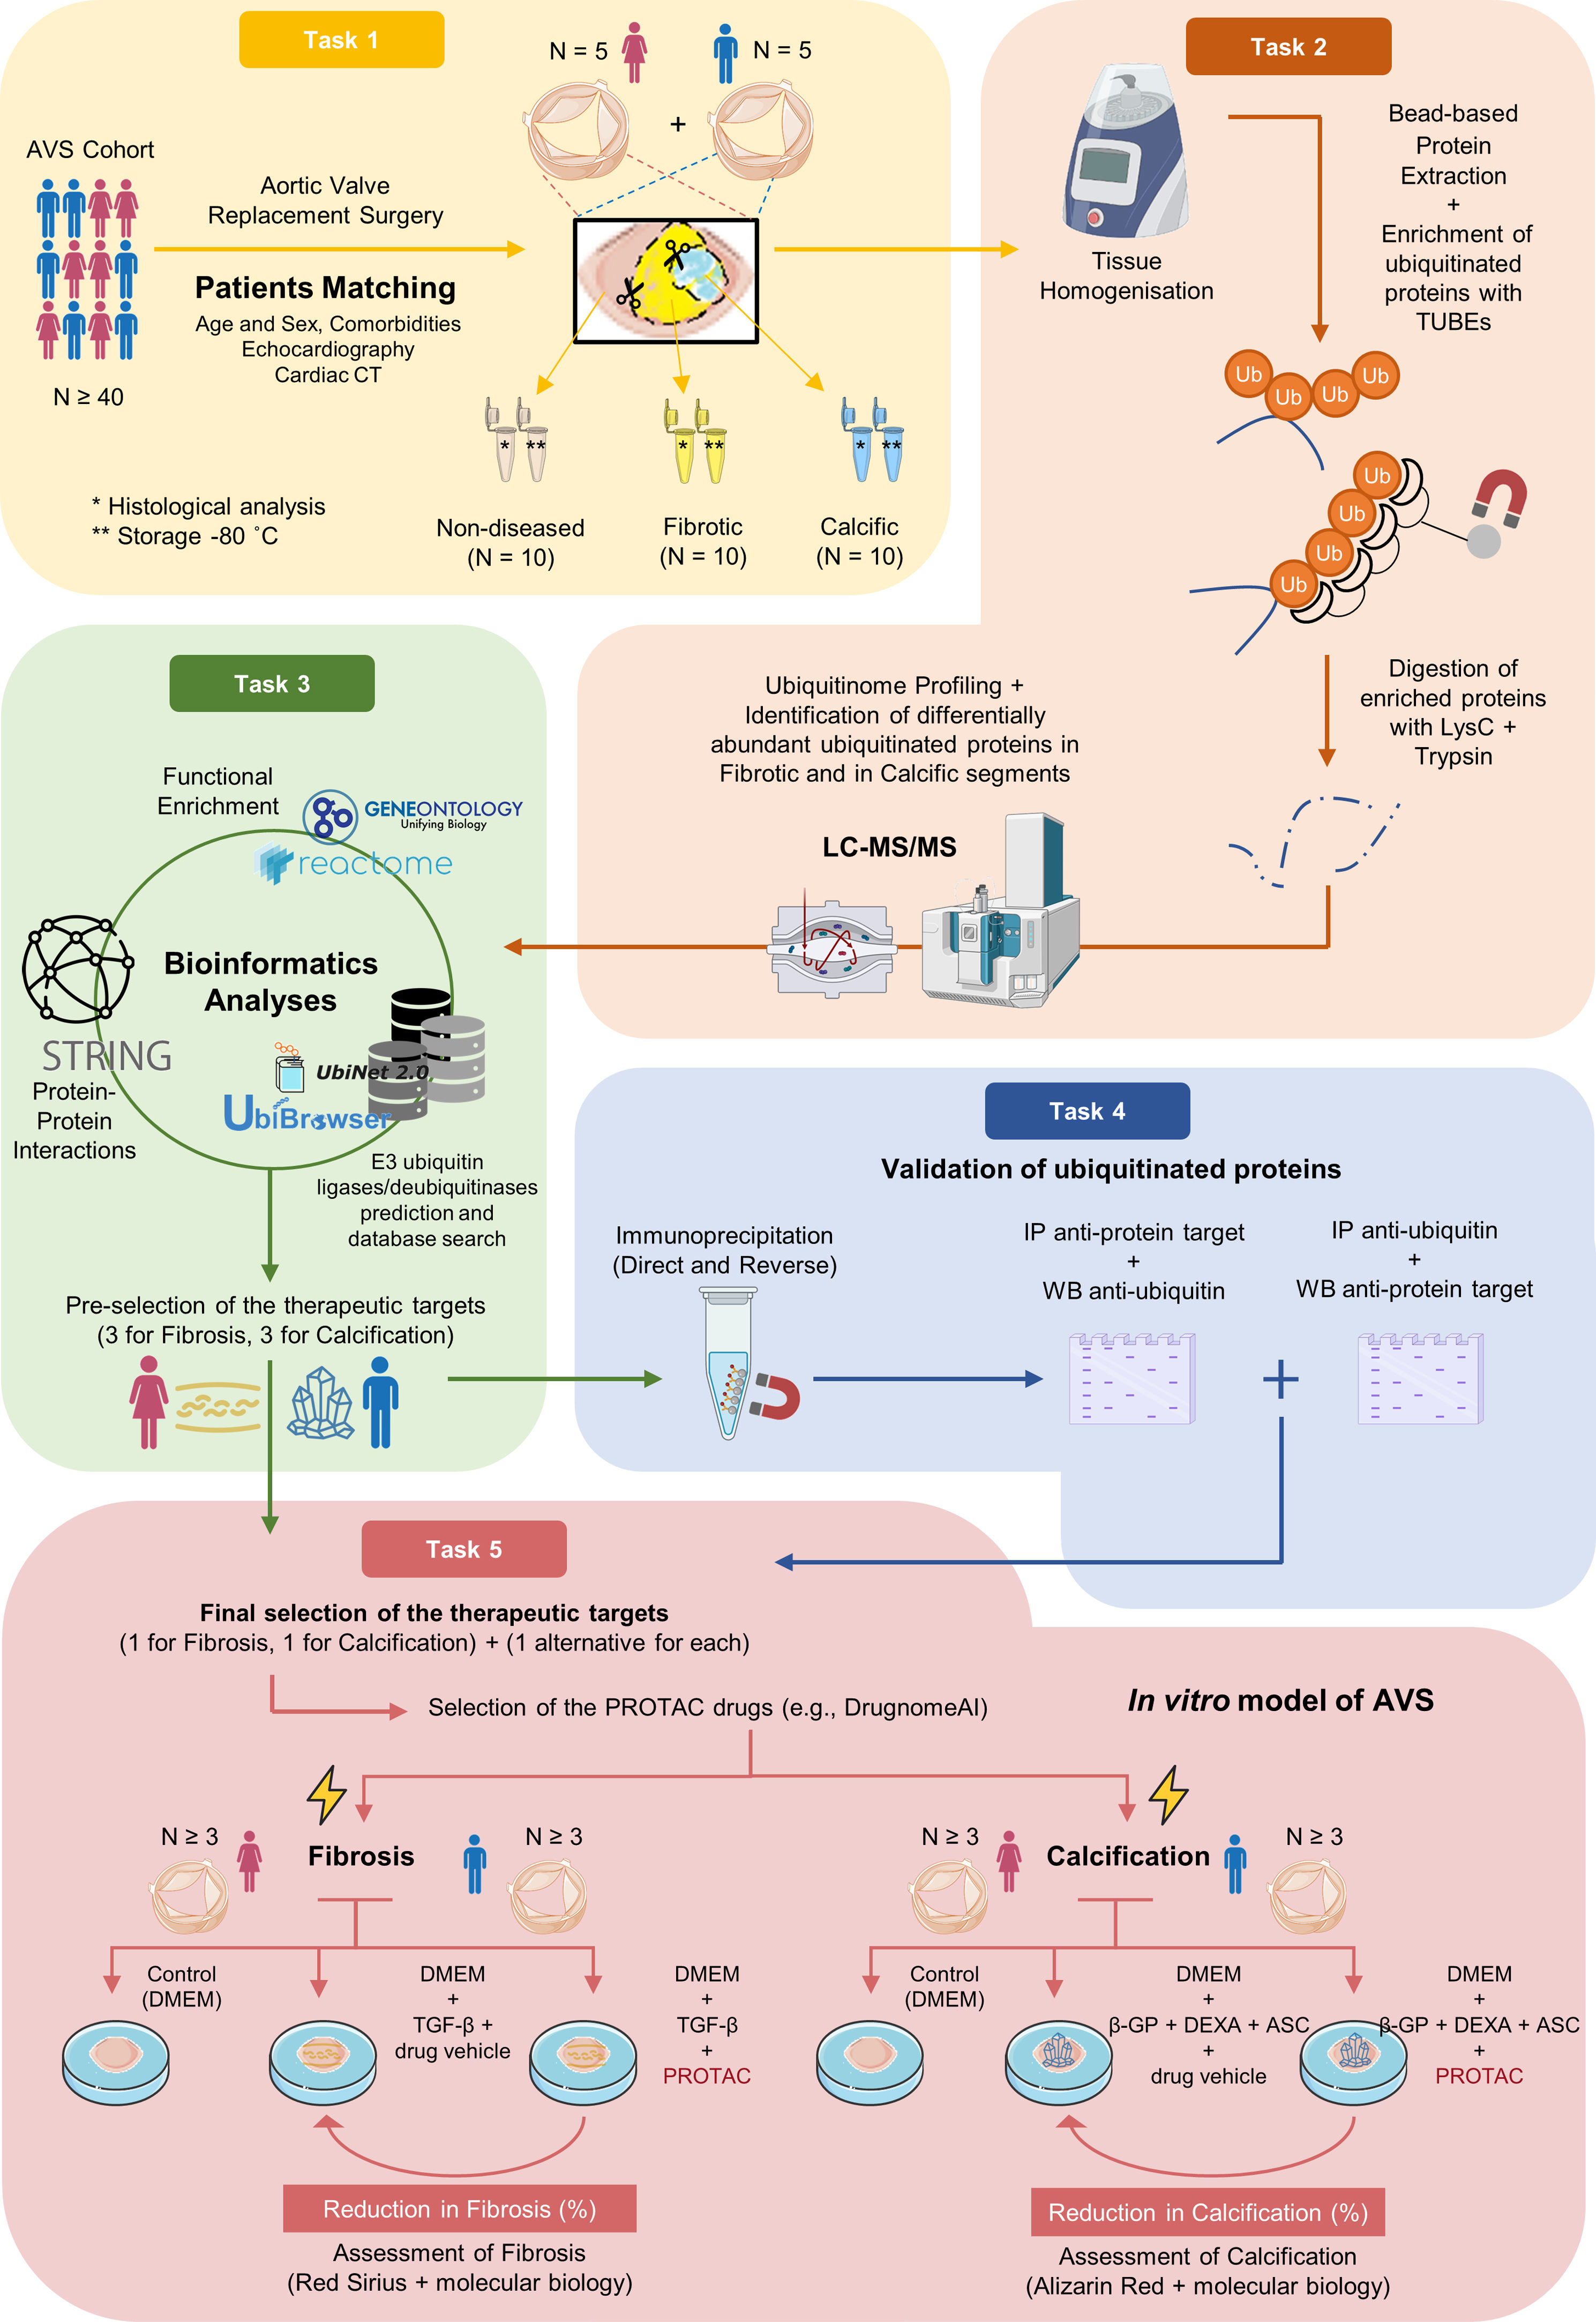
In RUBITAV, we will characterize the valve ubiquitinome using an MS-based proteomics approach. We will then identify and prioritize PROTAC-druggable polyubiquitinated targets using bioinformatics. Finally, VICs will be used as an in vitro model of AVS to test the effect of targeting specific proteins on two disease hallmarks: fibrosis (women-specific) and calcification (men-specific). A summary of the experimental plan is shown in Figure 1. The project is planned to last 36 months, divided into the following tasks:

Overview of the experimental plan. Abbreviations: ASC: ascorbic acid; AVS: aortic valve stenosis; CT: computed tomography; DEXA: dexamethasone; DMEM: Dulbecco's modified eagle medium; IP: immunoprecipitation; LC–MS/MS: liquid chromatography–tandem mass spectrometry; LysC: endoproteinase LysC; PROTACs: proteolysis-targeting chimeras; TGF-β: transforming growth factor-beta; TUBEs: tandem ubiquitin binding entities; WB: western blot; β-GP: beta-glycerophosphate.
Some graphical elements were created with BioRender.com.
Patients with AVS flagged at the Cardiology services of both Hospital Pedro Hispano – Unidade Local de Saúde de Matosinhos (ULSM) and Hospital Centre of São João – Unidade Local de Saúde de São João (ULSSJ) and undergoing elective AVR at the Department of Cardiothoracic Surgery of ULSSJ will be invited to participate. The inclusion criteria include (1) willingness to participate; (2) >18 years; (3) echocardiographic evidence of severe degenerative AVS. The exclusion criteria comprise (1) inability to give consent; (2) severe AV insufficiency; (3) bicuspid AVs; (4) rheumatic AVS; (5) active infection or steroid therapy in the last 3 months; (6) severe kidney disease (glomerular filtration rate <30 mL/min/1.73 m2); (7) severe liver disease; (8) endocrine disorders affecting phosphocalcic metabolism.
Patients’ clinical data will be collected, including the most relevant cardiovascular risk factors (e.g., hypertension, diabetes mellitus, dyslipidemia) and comorbidities (e.g., chronic kidney disease, coronary artery disease). Disease severity (e.g., aortic jet velocity, transvalvular gradients, aortic valve area) will be characterized by echocardiography, following the European Echocardiography Association guidelines.34 The calcium score will be collected by CCT.
The valves excised during surgery will be collected in a preservative solution (Custodiol) and transported to the laboratory. As a byproduct of AVR, the collection of the AV does not compromise the patient's safety. Each valve will be dissected by gross macroscopy, ensuring safety margins, to obtain 3 sections: non-diseased (internal control, ND), fibrotic (F), and calcific sections (C). ND is transparent, F is stiff and yellowish, and C is the thickest and most irregular. To ensure correct assignment, a representative transversal section will be obtained from each section for histological analysis. Fibrosis will be assessed by Sirius Red staining and calcification will be assessed by Alizarin Red staining. For all fragments, the % of each stain will be determined in relation to the total tissue area. Following distribution analysis, specific % cutoffs will be set to define ND, F and C sections. All sections for proteomics will be stored at −80°C until further analysis.
We expect to use valves from at least 10 matched patients (50% men) from a total of >40 patients, resulting in 30 fractions (10 ND, 10 F, 10 C). The remaining valves will be used in Task 4 (validation). The total sample size (n=30) was estimated based on our previous study reporting sex differences in aortic valve tissue proteome.20 In this study we found that the proteins dysregulated by sex displayed large effect sizes (minimum Cohen's d: 0.84; mean Cohen's d: 1.00; maximum Cohen's d: 1.23). For a more conservative target of Cohen's d=0.7, with α=0.05 and 80% power, 24 fractions would suffice to determine the effect of sex by ANCOVA. However, to account for the differences between the proteome and ubiquitinome, we inflate this number by 25%, giving a total target of 30.
As a contingency plan for the lack of in-patient non-diseased controls, we will use non-fibrotic and non-calcific valve tissue sections obtained from patients undergoing AVR due to severe aortic regurgitation (without concomitant severe AVS).
The recruitment of AVS patients has been approved by the ethics committee of Unidade Local de Saúde São João (ref. CEC109-2020, reviewed on September 26th 2025). All patients willing to participate will be asked to sign an informed consent. This study will adhere to the 1964 Declaration of Helsinki and its subsequent amendments. The collection of clinical information and echocardiography data abides by the 58/2019 Portuguese Law, warranting General Data Protection Regulation UE/2016/679 regarding the protection of the singular person, including personal treatment and free movement of such data.
Protein extraction, ubiquitin enrichment, and ubiquitinome profiling (Task 2)The AV is a challenging tissue for molecular analysis, not only due to its heterogeneity, but also due to extensive fibrosis and calcification. For this reason, the AV proteins will be extracted using a bead-based mechanical disruption method we have already optimized for this sample type.35 A lysis buffer enriched with deubiquitinase inhibitor (PR-619) will be used to preserve the modifications. Polyubiquitinated species will be enriched using magnetic Tandem-repeated Ubiquitin-Binding Entities (TUBEs). TUBEs stabilize ubiquitinated substrates and protect them from DUBs and proteasomal degradation during sample handling, thereby improving recovery and sensitivity. The efficiency of the enrichment assay will be controlled by semi-quantification of ubiquitin by WB. A technical negative control, run in triplicate, using ethanolamine-blocked TUBE matrix will control for specificity.
The proteins in the enriched fraction will be digested with LysC+trypsin and the peptides will be analyzed by nano-high-performance liquid chromatography–tandem MS in a data-independent acquisition mode to increase the quantification accuracy. Spectra will be analyzed by sourcing the SwissProt human database and defining Lys ubiquitination as a variable modification. A 5% false discovery rate will be applied for identifications, and the abundance of ubiquitinated proteins will be estimated by label-free quantification. Analysis of covariance (ANCOVA) will be used to assess the effect of sex on the difference in ubiquitinated protein abundances between fibrotic or calcific tissue and non-diseased control tissue. Furthermore, shotgun analysis of the whole proteome in, at least 3 random samples per group, will help filter off proteins whose variation in ubiquitination solely reflects variation at the total level. Data will be deposited in a public repository for proteome datasets: ProteomeXchange.
Ultimately, we anticipate identifying differentially expressed ubiquitinated proteins between the ND, F, and C sections, as well as between men and women, and establishing sex-specific correlations with echocardiography- or CCT-derived parameters of AVS severity.
Bioinformatics to predict and prioritize therapeutic targets (Task 3)To shortlist the targets to tackle fibrosis and calcification (each down to 3), the dysregulated ubiquitinated proteins will be prioritized combining 5 main analyses: (1) Functional enrichment analysis (Gene Ontology, Reactome) to map the proteins according to disease-relevant pathways and processes (with particular attention to ubiquitination and proteasome degradation pathways), with standard overrepresentation test for hypergeometric distributions; (2) Protein–protein interaction (STRING) and network topological analyses (Cytoscape), including node degree and betweenness centrality, to assign proteins their hub/bottleneck features (prioritization based on major disease modulation activity); (3) Prediction of the E3UL/DUB responsible for shaping the fibrotic- and calcific-specific valve ubiquitinome. Databases like UbiNet and prediction tools like UbiBrowser will be used to infer E3UL-substrate relationships, with emphasis on E3ULs associated with ubiquitination-mediated proteasomal degradation pathways (e.g., SCF complex); (4) Cross-referencing with publicly available datasets reporting sensitivity to proteasome inhibition (e.g., MG132-responsive proteins), to support the identification of targets more likely to undergo proteasomal turnover; (5) Prediction of the druggability of the putative targets with a machine-learning framework such as DrugnomeAI (this tool specifically provides a scoring function for PROTACs).
This multi-level target prioritization accounts not only for disease relevance but also for the likelihood of proteasomal regulation, thereby increasing the suitability of selected targets for targeted protein degradation approaches.
After statistical and bioinformatic analyses, a final set of proteins will be selected for Tasks 4 and 5.
Validation of ubiquitinated proteins and associated E3UL/DUB (Task 4)The final selection of the potential therapeutic targets will take into account an independent validation of the differentially expressed ubiquitinated proteins. First, target proteins will be pulled down from AV lysates by immunoprecipitation. Then, WBs targeting ubiquitin will be used to confirm the changes in the degree of ubiquitination of the target proteins in fibrotic and calcific sections from ND. To confirm this dysregulation, the inverse strategy will be applied: ubiquitinated proteins will be immunoprecipitated first with a pan-ubiquitin antibody and then the target proteins will be validated by WB. Additional WBs are also envisioned to clarify underlying pathways, such as UPS or autophagy.
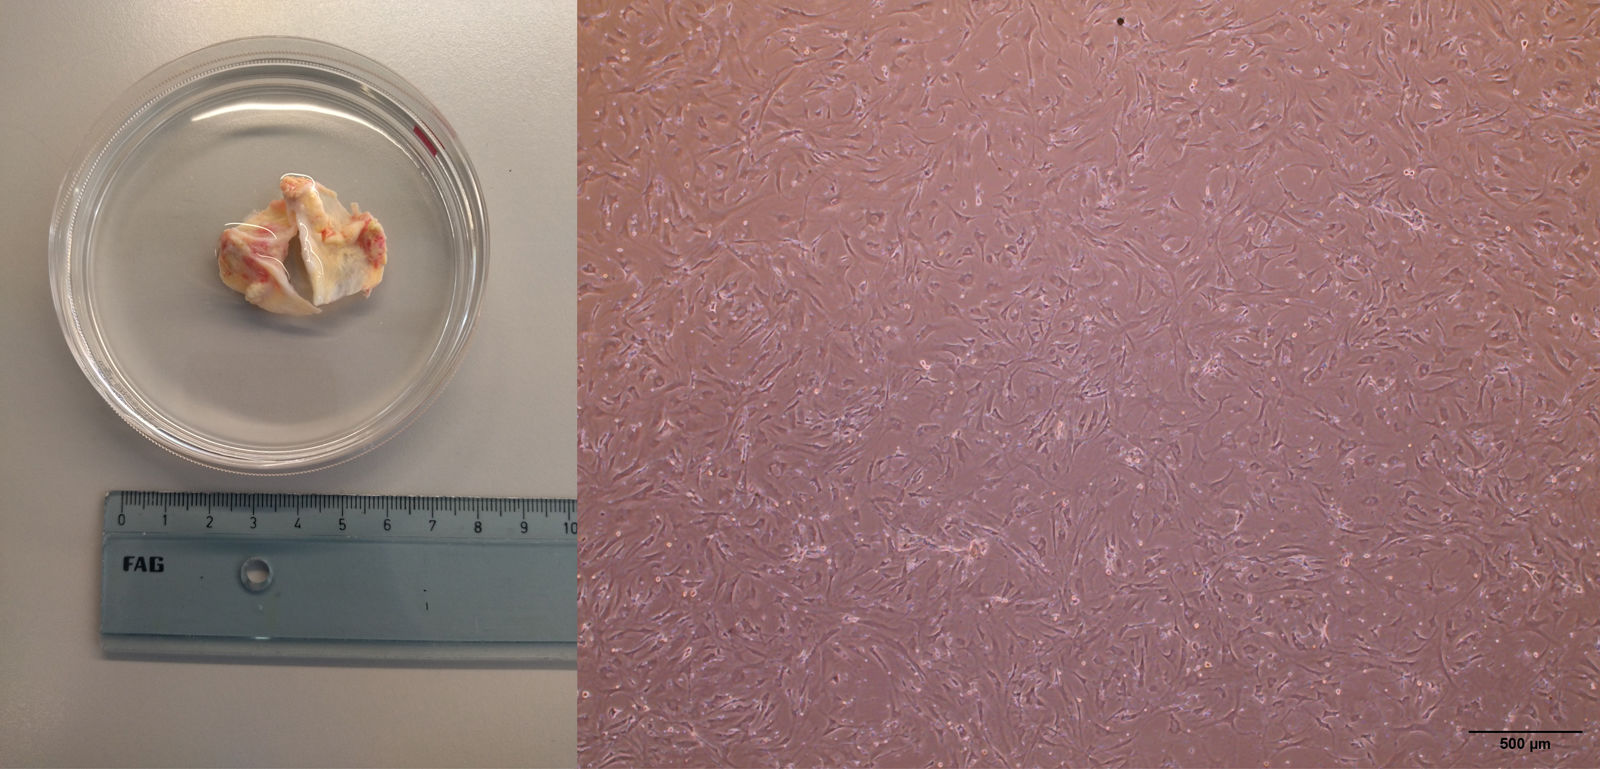
Ubiquitination-driven pharmacomodulation of the disease in vitro (Task 5)Once the final targets (ubiquitinated proteins, E3UL, or DUBs) are defined in Task 4, we aim to assess the effect of modulating their expression using PROTACs in two disease hallmarks: fibrosis and calcification. To do that, VICs from both sexes will be isolated from human valves (already implemented in our laboratory, Figure 2). Briefly, valve tissue is subjected to collagenase digestion, and the VICs are cultured in DMEM, supplemented with fetal bovine serum (FBS) and antibiotics, at 37°C and 5% CO2, according to Cuevas et al.,36 with slight modifications. Then, a protocol will be implemented to induce fibrosis and calcification.

The growth medium of female and male VICs will be enriched with 5 ng/mL of transforming growth factor-β (or vehicle as control), the master regulator of fibrosis. This treatment will be performed for at least 3 days, the time required for significant extracellular matrix synthesis.
Stimulation of calcificationThe growth medium of male and female VICs will be enriched with 10 nM β-glycerophosphate, 0.1 μM dexamethasone, and 50 μM ascorbic acid (or vehicle as control). This treatment will be performed for at least 3 weeks, the time required for significant deposition of calcific minerals. Alternatively, a pro-calcifying medium containing 2 mM NaH2PO4 and 50 μg/mL of ascorbic acid will be used to increase sensitivity in calcium deposition analysis.
Each VIC line (at least, 3 females and 3 males) will be treated in parallel under standard conditions (DMEM+FBS+antibiotics), under pro-fibrotic and pro-calcific stimuli with the drug vehicle, and under pro-fibrotic and pro-calcific stimuli with a specific PROTAC directed for a fibrosis-specific or calcification-specific target. The drug will be selected based on the interpretation of DrugnomeAI output (a raw score specific for PROTAC), retaining targets with a high probability of being modulated by PROTACs. Available PROTACs for these targets will then be sourced from PROTAC-DB (https://cadd.zju.edu.cn/protacdb/), prioritizing those commercially available.
The extent of fibrosis and calcification will be quantified by Sirius Red and Alizarin Red staining, respectively. The primary outcome will be determined as the % reduction in Sirius Red and Alizarin Red staining as compared to cells treated with the vehicle. For stain quantification, the medium will be removed after the pro-fibrotic or pro-calcific treatment are completed, and the cells will be washed with phosphate-buffered saline (PBS), fixed with formalin, and stained with Sirius Red 0.1% or Alizarin Red 2% for 1 h or 0.5 h in the dark. After differentiation with 0.5% HCl (Sirius Red only) and serial washes, the plates will be dried and photographed. Finally, the Sirius Red stain will be completely extracted with 0.1 M NaOH and directly quantified by spectrophotometry at 540 nm, while Alizarin Red stain will be extracted with 10% cetylpyridinium chloride and directly quantified at 562 nm. Additionally, markers of fibrosis, such as collagen I, fibronectin, or tenascin C, as well as markers of calcification, such as alkaline phosphatase, osteocalcin, and Runx2, will be quantified in cell lysates (RNA and protein) or secretome (protein) and their % change will define secondary outcomes.
To control for the efficacy of the PROTAC, the target protein will be measured by WB or equivalent immunoassay. The PROTAC treatment-driven differences in the extent of fibrosis and calcification at both the histological and molecular levels will be assessed using a mixed-effect model, followed by a post hoc Dunnett's test to compare means. The experiments will be performed at least in triplicate.
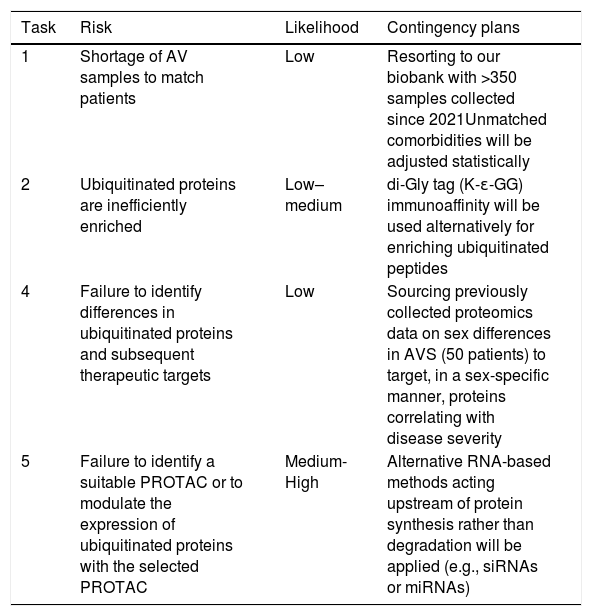
Risks and contingency plansThe major risks associated with the various tasks, along with their corresponding mitigation strategies, are presented in Table 2.
Major risks for the project RUBITAV and the corresponding contingency plans.
| Task | Risk | Likelihood | Contingency plans |
|---|---|---|---|
| 1 | Shortage of AV samples to match patients | Low | Resorting to our biobank with >350 samples collected since 2021Unmatched comorbidities will be adjusted statistically |
| 2 | Ubiquitinated proteins are inefficiently enriched | Low–medium | di-Gly tag (K-ɛ-GG) immunoaffinity will be used alternatively for enriching ubiquitinated peptides |
| 4 | Failure to identify differences in ubiquitinated proteins and subsequent therapeutic targets | Low | Sourcing previously collected proteomics data on sex differences in AVS (50 patients) to target, in a sex-specific manner, proteins correlating with disease severity |
| 5 | Failure to identify a suitable PROTAC or to modulate the expression of ubiquitinated proteins with the selected PROTAC | Medium-High | Alternative RNA-based methods acting upstream of protein synthesis rather than degradation will be applied (e.g., siRNAs or miRNAs) |
Not applicable.
DiscussionExpected outcomes and clinical relevanceRUBITAV builds on the recent findings of our group demonstrating sexual dimorphism in AVS from a proteomics perspective.20 The AV proteome supports an alternative splicing program that contributes to the more pronounced fibrotic remodeling in females and an increased propensity for lipoprotein accumulation, immune system activation, and oxidative stress in males, which primes a more pronounced pro-calcific phenotype. With RUBITAV, we expect to build on these findings, clarifying the role of the UPS, specifically ubiquitination, in the pathological transformation of the valve. We also expect to uncover sex-specific therapeutic targets to tackle fibrosis and calcification in AVS, and to open the way for repurposing PROTACs in atherosclerotic cardiovascular disease, specifically in AVS.
Overall, this project aligns with the UN Sustainable Development Goals 2030 Agenda, specifically goal 3.4, which aims to reduce premature mortality from non-communicable diseases through prevention and treatment. This project will also contribute specifically to goal 5.1, aiming at achieving gender equality concerning the personalization of the diagnosis and treatment. In fact, women have been chronically underrepresented in many milestone trials, resulting in suboptimal treatment. By developing sex-specific therapeutic strategies to target not only valve calcification (mainly afflicting men) but also fibrosis (mainly afflicting women), we will promote equality in the treatment of AVS.
ConclusionRUBITAV is the first study to holistically characterize the ubiquitinome in AVS, associated with two disease hallmarks: fibrosis and calcification, afflicting mainly women and men, respectively. By profiling the dysregulated ubiquitinated proteins by MS and assessing their interactions and roles by bioinformatics, we will uncover new sex-specific mechanisms involved in disease progression and pinpoint new therapeutic targets. Moreover, RUBITAV will pave the way for widening the scope of PROTAC-based pharmacotherapy from oncology to the cardiovascular field, through a proof-of-concept demonstration of mitigating the fibrocalcific phenotype by promoting a targeted degradation of dysregulated proteins.
Ethical approvalEthics Committee of the Local Health Unit of São João (reference number CEC109-2020; reviewed on September 26th 2025).
FundingThis project is supported by the João Porto Study Grant (2025) from the Portuguese Society of Cardiology and by national funds through Fundação para a Ciência e Tecnologia (FCT), I.P., within the scope of the former Cardiovascular Research and Development Centre – UnIC (UIDB/00051/2020 and UIDP/00051/2020) and current RISE-Health. F.T. and F.S. are funded by national funds through FCT, I.P., and under the Recovery and Resilience Plan (PRR) within the scope of the “Ciência Mais Capacitação”, under the FCT-Tenure program (2023.13694.TENURE.022 and 2023.13694.TENURE.021, respectively). R.N.F. is also supported by FCT through the research contract CEECIND/03935/2021 under the CEEC Individual 2021 (https://doi.org/10.54499/2021.03935.CEECIND/CP1685/CT0001).
Conflicts of interestThe authors have no conflicts of interest to declare.
The authors thank the continuous and dedicated collaboration of the nurse and medical staff from the Cardiothoracic Surgery Department of the ULSSJ in patient recruitment and the collection of biological samples.



