





To assess long-term outcomes of acute myocarditis (AM).
MethodsProspective, single-center observational study including patients admitted with AM between 2007 and 2022, followed at a tertiary cardiology center. Follow-up (FUP) included annual clinical evaluations, treadmill testing, Holter and echocardiography. Statistical analysis was performed using chi-square test and Cox regression.
ResultsWe included 158 patients, 12.7% female, with a mean age of 32±12 years. Most presented with chest pain (94.3%). Severe complications, including cardiogenic shock or arrhythmic storm, occurred in 3.6%. Upon admission, the mean left ventricle ejection fraction (LVEF) was 57%. Out of the 140 patients who underwent cardiac magnetic resonance imaging (CMR), myocardial oedema and late gadolinium enhancement (LGE) were present in 47.8% and 88.5%, respectively. During a mean FUP time of 6±4.3 years, 13.3% patients were readmitted, 80.9% of them due to recurrent myocarditis. Only one patient with LVEF <50% at admission did not recover at FUP. No patients exhibited significant arrhythmias during Holter monitoring or treadmill stress tests. Six patients died at FUP. Three patients had experienced fulminant myocarditis (FM) at index admission; two of them died due to CV causes. There was a statistically significant association between death and fulminant presentation during index admission (p<0.001).
ConclusionAM in adults typically followed a benign course with favorable short- and long-term outcomes. In contrast, a small but significant subset with FM had a markedly poorer prognosis, with severe recurrences frequently proving fatal. Clinical presentation was the sole determinant of prognosis, prompting consideration of whether patients with milder cases truly require extended FUP.
Avaliar o prognóstico a longo prazo da miocardite aguda (AM).
MétodosEstudo prospetivo observacional incluindo doentes internados com AM entre 2007 e 2022, seguidos num centro terciário de cardiologia. O seguimento (FUP) incluiu avaliações clínicas anuais, prova de esforço, Holter e ecocardiograma. Foi realizada análise estatística com teste do qui-quadrado e regressão de Cox.
ResultadosForam incluídos 158 doentes, dos quais 12,7% do sexo feminino, com uma idade média de 32±12 anos. A maioria apresentou dor torácica (94,3%). Complicações graves, incluindo choque cardiogénico ou tempestade arrítmica, ocorreram em 3,6%. À admissão, a fração de ejeção do ventrículo esquerdo (LVEF) média foi de 57%. Dos 140 doentes submetidos a ressonância magnética cardíaca (RMC), foi documentado edema miocárdico e realce tardio pelo gadolínio em 47,8% e 88,5% dos doentes, respetivamente. Durante FUP de 6±4,3 anos, 13,3% doentes foram reinternados, sendo que 80,9% por recorrência de miocardite. Apenas um doente com LVEF < 50% à admissão não melhorou no FUP. Não se verificaram arritmias significativas em Holter ou prova de esforço. Seis doentes faleceram no FUP; três tinham apresentado miocardite fulminante (FM) no episódio inicial, dois dos quais faleceram por causa cardiovascular. Observou-se associação estatisticamente significativa entre morte e apresentação fulminante no episódio índice (p < 0,001).
ConclusãoA AM em adultos apresentou, na maioria dos casos, evolução benigna e prognóstico favorável a curto e longo prazo. Em contraste, os doentes com FM apresentaram, na sua maioria, um prognóstico pior, com recidivas graves frequentemente fatais. A apresentação clínica foi o único determinante de prognóstico, levantando a questão de se os casos mais ligeiros requerem efetivamente seguimento prolongado.

Acute myocarditis (AM) is an inflammatory disease of the myocardium caused by different infectious and noninfectious triggers. In 1995, myocarditis was defined by the World Health Organization (WHO)/International Society and Federation of Cardiology (ISFC) as an inflammatory disease of the heart muscle, diagnosed by established histological, immunological, and immunohistochemical criteria.1 Although it is generally caused by a postviral immune response, other triggers such as drug hypersensitivity reactions, infections, immune checkpoint inhibitors or systemic autoimmune disorders may be involved.2–5
The true incidence of myocarditis is difficult to determine, mainly due to infrequent utilization of the diagnostic gold standard, endomyocardial biopsy.6 According to hospital discharge forms spanning from 1990 to 2013, the Global Burden of Disease Study estimated an annual incidence of 22 cases per 100000 patients.7 Among patients presenting to the emergency department, AM constituted the second most frequent cardiac cause of chest pain in a French registry.8 While myocarditis can affect individuals of all ages, it is notably more prevalent in the young and affects men more than women.9,10
Although most cases present with mild symptoms, myocarditis appears to be an important cause of sudden cardiac death in young individuals, ranging from 6% to 10% in autopsy-based series.11–13 In some patients, inflammation may cause extensive scarring that triggers left ventricular remodeling, leading eventually to dilated cardiomyopathy. In adults with unexplained non-ischemic dilated cardiomyopathy, chronic, EMB-proven inflammation can be found in 9–30% of cases.14
Advanced diagnostic techniques such as cardiovascular magnetic resonance (CMR) imaging or immunohistologic and molecular analysis of endomyocardial biopsies (EMB) have shed new light on this inadequately characterized disease.15,16 Nevertheless, effective clinical management remains challenging, and the long-term mortality, risk of developing dilated cardiomyopathy, future arrhythmias, and potential risk factors contributing to poor clinical outcomes remain largely uncertain. Contemporary prospective studies on the long-term prognosis of AM are limited, resulting in insufficient evidence to support an optimal follow-up strategy for these patients.
ObjectivesThe aim of this study was to prospectively assess the natural history of AM from the time of its diagnosis up to a median FUP of at least five years, evaluating progression to chronic heart failure, ventricular arrhythmia and long-term mortality, while establishing the long-term prognostic value of various clinical, laboratory and imaging parameters.
MethodsPatient selectionThis was a single-center, prospective, observational study conducted at a tertiary university hospital (ULSSM, Lisbon, Portugal) since January 2007. The current dataset comprised patients with a minimum 1-year follow-up, i.e., through December 2022. We selected patients aged >18 years who were admitted with a final diagnosis of AM. Only patients with AM diagnosed according to the criteria proposed by the 2013 European Society of Cardiology Working Group on Myocardial and Pericardial Diseases (“Patients presenting with acute or new-onset chest pain, dyspnea, signs of left and/or right heart failure, and/or unexplained arrhythmias or aborted sudden death, with at least one mandatory diagnostic test being positive (preferably CMR), in the absence of significant coronary artery disease, valvular or congenital heart disease, or other identifiable causes”) were included.5 Patients hospitalized before 2013 were selected using the same inclusion criteria.
Data collectionBaseline hospitalization phasePatients underwent daily clinical assessment. A laboratory panel was obtained on admission as standard. The troponin assay was a 4th generation troponin I until 2015. From 2016 onwards a high sensitivity troponin T assay (Roche) was used.
A standard 12-lead ECG assessment was undertaken at admission and per physician request during the remaining hospitalization. Given the frequent focal nature of myocarditis, the presence of ST-segment elevation (STE) in a single lead was considered positive for each cardiac wall: anterior (STE in leads V1–V4), inferior (STE in leads II, III, and aVF), and lateral (STE in leads I, aVL, V5–V6). The posterior wall was excluded from the analysis.
Echocardiographic examination was performed on admission and on discharge for assessment of ventricular volumes, regional and global systolic function, diastolic function, valvular and pericardial changes. Additional assessments were performed as necessary on an individual basis.
Electrocardiography-gated CMR imaging was performed as early as possible, either during the index admission or shortly thereafter. The imaging protocol included a cine cardiac sequence to T2-short-tau inversion recovery (STIR) fast spin-echo sequence for oedema; a late gadolinium enhancement (LGE) sequence, using gradient echo inversion recovery and PSIR, 10–20min after bolus injection of 0.2 mmol/kg of gadolinium, for focal myocardial lesion.
Endomyocardial biopsy was performed only in selected cases (details in “Results” section). Samples were stained with Masson's trichrome as well as Giemsa and examined by light microscopy. For immunohistology, tissue sections were treated with an avidin-biotin-immunoperoxidase method (Vectastain Elite Kit, Vector, Burlingame, California), applying the following monoclonal antibodies: CD3 (T-cells, Novocastra Laboratories, Newcastle, United Kingdom), CD68 (macrophages, DAKO, Hamburg, Germany), and human leukocyte antigen-DR (DAKO).
Fulminant myocarditis (FM) was defined as clinical presentation with new-onset severe heart failure or arrhythmic storm requiring parenteral inotropic support or mechanical circulatory support, as outlined by the European Society of Cardiology Working Group on Myocardial and Pericardial Diseases.5
Follow-upPatients were followed with an annual Cardiology appointment for a minimum of five years, after which they had the option to either continue FUP or be discharged. Those who chose discharge received a telephone FUP in November 2023.
Annual assessments consisted of clinical evaluation, transthoracic echocardiogram, exercise stress test to evaluate exercise tolerance and exercise-induced arrhythmias and 24-hour Holter monitoring to detect the presence of atrial and/or ventricular arrhythmias.
Statistical analysisCategorical variables were expressed as frequency counts and percentages, and continuous variables as means and standard deviations (SDs). Normal distribution was assessed using the Shapiro–Wilk test or by examining skewness and kurtosis. Data analysis was performed using the independent samples t-test or the Mann–Whitney U test to compare continuous variables, and the chi-squared test or Fisher's exact test to compare categorical variables, as appropriate based on their distribution. Multivariate analysis was conducted using univariate and multivariate Cox regression. Statistical significance was defined as a p value <0.05. The statistical software used to analyze the data was SPSS® version 26 (IBM).
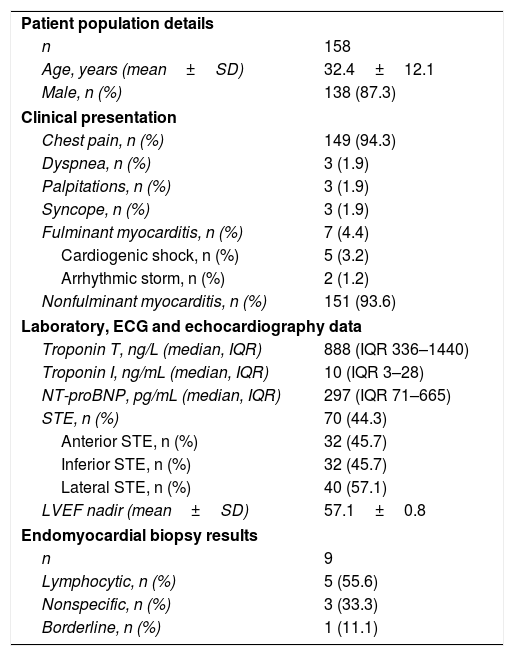
ResultsBetween 2007 and 2022, 158 patients were admitted with AM in our department. Table 1 provides a detailed overview of the primary clinical characteristics. The mean age was 32.4±12.1 years, with 138 being male (87.3%). The predominant clinical presentation was chest pain in 149 patients (94.3%) and heart failure in three patients (1.9%), while the remainder reported either palpitations or syncope.
Demographic, clinical, laboratory, ECG, echocardiography and EMB during hospitalizations. Population and hospitalization characteristics.
| Patient population details | |
| n | 158 |
| Age, years (mean±SD) | 32.4±12.1 |
| Male, n (%) | 138 (87.3) |
| Clinical presentation | |
| Chest pain, n (%) | 149 (94.3) |
| Dyspnea, n (%) | 3 (1.9) |
| Palpitations, n (%) | 3 (1.9) |
| Syncope, n (%) | 3 (1.9) |
| Fulminant myocarditis, n (%) | 7 (4.4) |
| Cardiogenic shock, n (%) | 5 (3.2) |
| Arrhythmic storm, n (%) | 2 (1.2) |
| Nonfulminant myocarditis, n (%) | 151 (93.6) |
| Laboratory, ECG and echocardiography data | |
| Troponin T, ng/L (median, IQR) | 888 (IQR 336–1440) |
| Troponin I, ng/mL (median, IQR) | 10 (IQR 3–28) |
| NT-proBNP, pg/mL (median, IQR) | 297 (IQR 71–665) |
| STE, n (%) | 70 (44.3) |
| Anterior STE, n (%) | 32 (45.7) |
| Inferior STE, n (%) | 32 (45.7) |
| Lateral STE, n (%) | 40 (57.1) |
| LVEF nadir (mean±SD) | 57.1±0.8 |
| Endomyocardial biopsy results | |
| n | 9 |
| Lymphocytic, n (%) | 5 (55.6) |
| Nonspecific, n (%) | 3 (33.3) |
| Borderline, n (%) | 1 (11.1) |
LVEF: left ventricular ejection fraction; STE: ST segment elevation.
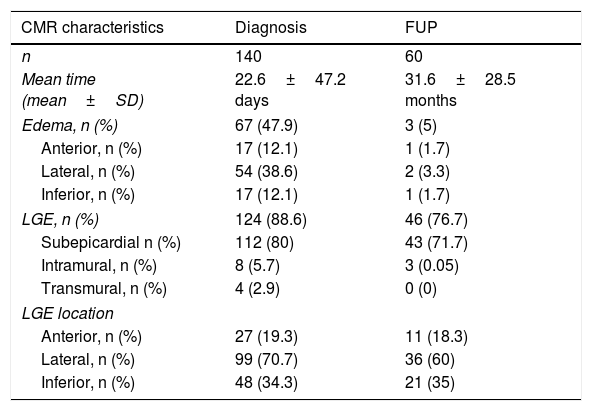
Most patients had an abnormal electrocardiogram upon admission, with ST-segment abnormalities as the most common finding. 44.3% of patients exhibited ST elevation, more frequently in the anterior and inferior walls (45.7% each). The mean LVEF upon admission was 57.1±0.8%. Regarding laboratory results, the median peak troponin T level was 888 ng/L (IQR 336–1440), the median NT-proBNP level was 297 pg/mL (IQR 71–665), and the mean C-reactive protein (CRP) level was 19 mg/L. CMR was performed in 140 (88.6%) patients. Myocardial oedema and LGE were present in 47.9% and 88.6% of patients, respectively. LGE was subepicardial in 80% of cases, intramural in 5.7%, and transmural in 2.9%. Specifically, 19.3% exhibited anterior LGE, 70.7% manifested lateral LGE, and 34.3% presented with inferior LGE (Table 2).
Characteristics in CMR at the time of diagnosis and during follow-up.
| CMR characteristics | Diagnosis | FUP |
|---|---|---|
| n | 140 | 60 |
| Mean time (mean±SD) | 22.6±47.2 days | 31.6±28.5 months |
| Edema, n (%) | 67 (47.9) | 3 (5) |
| Anterior, n (%) | 17 (12.1) | 1 (1.7) |
| Lateral, n (%) | 54 (38.6) | 2 (3.3) |
| Inferior, n (%) | 17 (12.1) | 1 (1.7) |
| LGE, n (%) | 124 (88.6) | 46 (76.7) |
| Subepicardial n (%) | 112 (80) | 43 (71.7) |
| Intramural, n (%) | 8 (5.7) | 3 (0.05) |
| Transmural, n (%) | 4 (2.9) | 0 (0) |
| LGE location | ||
| Anterior, n (%) | 27 (19.3) | 11 (18.3) |
| Lateral, n (%) | 99 (70.7) | 36 (60) |
| Inferior, n (%) | 48 (34.3) | 21 (35) |
CMR: cardiac magnetic resonance imaging; FUP: follow-up; LGE: late gadolinium enhancement.
Of the total cohort, nine patients underwent endomyocardial biopsy for etiological investigation. Four of these biopsies were performed due to cardiogenic shock, while the remaining five were conducted due to recurrent myocarditis episodes. The most frequent finding was a lymphocytic infiltrate.
Seven patients progressed to FM, with cardiogenic shock or arrhythmic storm:
Patient 1: 30-year-old man admitted with cardiogenic shock and severe systolic dysfunction (LVEF 10%), requiring inotropic and mechanical support with intra-aortic balloon pump (IABP) and orotracheal intubation. CMR confirmed AM with subepicardial LGE in the posterior and lateral walls. Despite partial recovery of left ventricular function (LVEF 32%) at discharge and optimized, maximally tolerated guideline-directed medical therapy (bisoprolol 5 mg once daily, ramipril 5 mg twice daily, spironolactone 25 mg once daily and empagliflozin 10 mg once daily), the patient experienced recurrent hospitalizations and progressed to advanced heart failure, ultimately being evaluated for heart transplantation. He died two years after the initial hospitalization.
Patient 2: 25-year-old man initially admitted for infectious colitis. His hospitalization was complicated by cardiac arrest, which was reverted with defibrillation, followed by multiple episodes of sustained monomorphic ventricular tachycardia requiring cardioversion. Despite antiarrhythmic therapy, he required orotracheal intubation, sedation and ventilatory support due to recurrent episodes. CMR showed moderate systolic dysfunction (LVEF 35%) and extensive subepicardial LGE. After correcting electrolyte disturbances, his condition stabilized. He remained asymptomatic and free of rehospitalizations. He suffered non-cardiovascular death eight years later.
Patient 3: 24-year-old woman initially hospitalized with acute Coxsackie myocarditis, confirmed by CMR findings of subepicardial late gadolinium enhancement in the lateral and septal walls. Her condition was complicated by new-onset atrial fibrillation with fast ventricular response, requiring multiple cardioversions and antiarrhythmic therapy. She initially presented with reduced LVEF 35% and was discharged in sinus rhythm on antiarrhythmic therapy, along with prognostic-modifying medications (ramipril 5 mg once daily, bisoprolol 5 mg once daily, and spironolactone 25 mg once daily). Left ventricular function subsequently improved, with LVEF increasing to 50%. During follow-up, however, she experienced recurrent episodes of atrial fibrillation despite ongoing antiarrhythmic therapy with amiodarone. One year later, she was readmitted with uncontrolled atrial fibrillation with fast ventricular response, refractory to antiarrhythmic treatment and repeated electrical cardioversions. She died in the emergency department.
Patient 4: 47-year-old woman with flu-like symptoms admitted with cardiogenic shock and severe systolic dysfunction (LVEF 15%), requiring IABP and orotracheal intubation. Endomyocardial biopsy confirmed active lymphocytic myocarditis. Her course was complicated by pulseless electrical activity arrest, requiring VA-ECMO. She developed hypoxic–ischemic encephalopathy with cognitive and motor deficits. At discharge, she was receiving maximally tolerated prognostic-modifying medical therapy (bisoprolol 5 mg once daily, sacubitril/valsartan 49/51 mg twice daily, spironolactone 25 mg once daily, and dapagliflozin 10 mg once daily). LVEF had improved to 40% at discharge, and no further heart failure-related events were reported during FUP.
Patient 5: 27-year-old man with initial symptoms of gastroenteritis was admitted in cardiogenic shock (LVEF 10%). He required both IABP and VA-ECMO support. Endomyocardial biopsy confirmed active lymphocytic myocarditis. He experienced a favorable recovery and was discharged with an LVEF of 38%. FUP was uneventful, with full recovery of systolic function while on maximally tolerated guideline-directed, prognostic-modifying medical therapy (bisoprolol 5 mg once daily, ramipril 5 mg twice daily, spironolactone 25 mg once daily, and dapagliflozin 10 mg once daily), which was maintained.
Patient 6: 56-year-old man admitted with arrhythmic storm following a recent respiratory infection. Cardiac MRI confirmed myocarditis with an LVEF of 30% and extensive subepicardial late gadolinium enhancement involving the anterior, lateral, and inferior walls. His condition improved with antiarrhythmic therapy, and during hospitalization he underwent implantation of an implantable cardioverter-defibrillator (ICD) for secondary prevention. Guideline-directed, prognostic-modifying medical therapy was initiated and titrated, resulting in partial recovery of left ventricular systolic function, with LVEF improving to 48% during FUP. FUP was uneventful, with no rehospitalizations.
Patient 7: 51-year-old man admitted with cardiogenic shock following a recent flu-like syndrome, presenting with severe global systolic dysfunction (LVEF 20%) and requiring inotropic support. The diagnosis of FM was confirmed by endomyocardial biopsy. During FUP guideline-directed, prognostic-modifying medical therapy was titrated to the maximally tolerated doses, and the patient demonstrated recovery of left ventricular function, with no rehospitalizations reported.
All patients presenting with heart failure were treated with state-of-the-art heart failure medication according to guidelines. Regarding myocarditis etiology, 86% of cases were presumed to be post-viral, with a possible causative virus identified in 23 patients (14%). The identified pathogens included Coxsackie virus in 10 patients (6%), parvovirus in 4 (2%), adenovirus in 3 (1.8%), echovirus in 3 (1.8%), Epstein–Barr virus in 2 (1.2%), and cytomegalovirus in 1 (0.6%). Other etiologies included lupus-related myopericarditis (n=2), streptococcal tonsillitis-associated myocarditis (n=2), Chlamydia pneumoniae infection (n=2), Q fever (n=2), and rickettsial infection (n=1). No patient in this cohort received additional immunosuppressive, immunomodulatory, or antiviral therapy. The average length of hospital stay was 8.3±6.8 days. No deaths occurred during hospitalization.
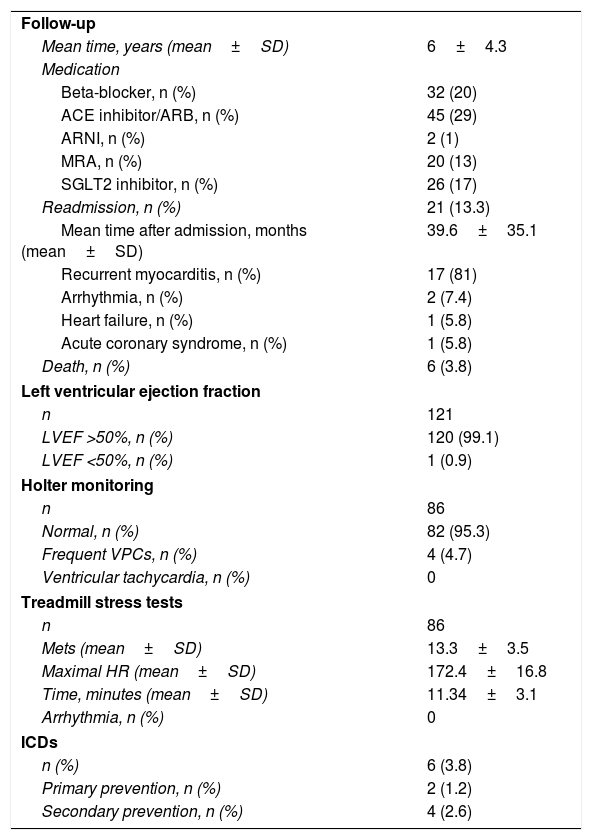
Progression during follow-upDuring a mean FUP period of 6±4.3 years, 21 patients (13.3% of patients) were readmitted, the majority due to recurrent myocarditis (17 patients), all of whom had both the initial admission and recurrence for non-fulminant myocarditis (Table 3). Two patients were readmitted due to arrhythmia (patient 3). There was one readmission for decompensated heart failure. This was patient 1, whose initial admission was for FM with severe left ventricular dysfunction, and who later died during FUP. Another patient was readmitted for acute coronary syndrome, having previously been admitted for uncomplicated AM.
Characteristics during follow-up.
| Follow-up | |
| Mean time, years (mean±SD) | 6±4.3 |
| Medication | |
| Beta-blocker, n (%) | 32 (20) |
| ACE inhibitor/ARB, n (%) | 45 (29) |
| ARNI, n (%) | 2 (1) |
| MRA, n (%) | 20 (13) |
| SGLT2 inhibitor, n (%) | 26 (17) |
| Readmission, n (%) | 21 (13.3) |
| Mean time after admission, months (mean±SD) | 39.6±35.1 |
| Recurrent myocarditis, n (%) | 17 (81) |
| Arrhythmia, n (%) | 2 (7.4) |
| Heart failure, n (%) | 1 (5.8) |
| Acute coronary syndrome, n (%) | 1 (5.8) |
| Death, n (%) | 6 (3.8) |
| Left ventricular ejection fraction | |
| n | 121 |
| LVEF >50%, n (%) | 120 (99.1) |
| LVEF <50%, n (%) | 1 (0.9) |
| Holter monitoring | |
| n | 86 |
| Normal, n (%) | 82 (95.3) |
| Frequent VPCs, n (%) | 4 (4.7) |
| Ventricular tachycardia, n (%) | 0 |
| Treadmill stress tests | |
| n | 86 |
| Mets (mean±SD) | 13.3±3.5 |
| Maximal HR (mean±SD) | 172.4±16.8 |
| Time, minutes (mean±SD) | 11.34±3.1 |
| Arrhythmia, n (%) | 0 |
| ICDs | |
| n (%) | 6 (3.8) |
| Primary prevention, n (%) | 2 (1.2) |
| Secondary prevention, n (%) | 4 (2.6) |
ACEi: angiotensin-converting enzyme inhibitor; ARB: angiotensin receptor blocker; ARNI: angiotensin receptor–neprilysin inhibitor; FUP: follow-up; HR: heart rate; ICDs: implantable cardioverter-defibrillators; LVEF: left ventricular ejection fraction; MRA: mineralocorticoid receptor antagonist; SGLT2i: sodium–glucose cotransporter 2 inhibitor; VPCs: ventricular premature contractions.
During FUP, all patients recovered LVEF and maintained values above 50%, except for patient 1 (described above), who progressed to advanced heart failure and died during FUP. No patients exhibited significant arrhythmias on Holter monitoring or treadmill stress tests (see appendices 1 and 2). FUP CMR was performed on 60 patients, with 5% showing persistent myocardial oedema and 76.7% demonstrating LGE. Six patients had implantable cardioverter-defibrillators (ICDs) placed during FUP. Four of the patients received ICDs during their index hospitalization for secondary prevention due to episodes of sustained ventricular tachycardia requiring cardioversion. Two patients received ICDs for primary prevention: one was diagnosed with Brugada syndrome, and the other had reduced LVEF combined with a high percentage of gadolinium enhancement on cardiac MRI at admission. Only one patient experienced an appropriate shock, a female with an ICD implanted for secondary prevention after an episode of ventricular tachycardia during hospitalization. She was later readmitted and successfully underwent ablation.
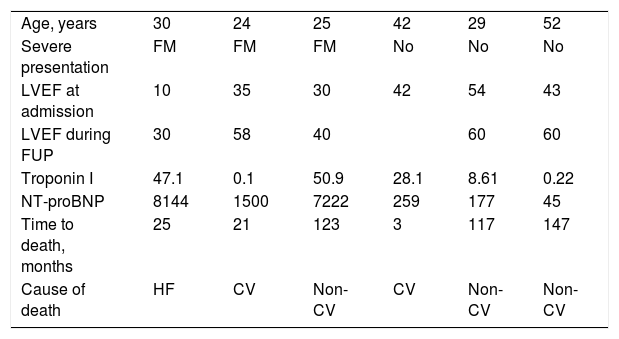
During FUP, six patients died (3.8%), with a five-year all-cause mortality rate of 1.9% and a 10-year mortality rate of 2.5%. Three (1.9%) of these patients suffered from cardiac causes, while the remaining patients died from non-cardiovascular (CV) causes. A detailed overview of the clinical, laboratory and imaging characteristics of these patients is presented in Table 4.
Characteristics of the population that died during FUP.
| Age, years | 30 | 24 | 25 | 42 | 29 | 52 |
| Severe presentation | FM | FM | FM | No | No | No |
| LVEF at admission | 10 | 35 | 30 | 42 | 54 | 43 |
| LVEF during FUP | 30 | 58 | 40 | 60 | 60 | |
| Troponin I | 47.1 | 0.1 | 50.9 | 28.1 | 8.61 | 0.22 |
| NT-proBNP | 8144 | 1500 | 7222 | 259 | 177 | 45 |
| Time to death, months | 25 | 21 | 123 | 3 | 117 | 147 |
| Cause of death | HF | CV | Non-CV | CV | Non-CV | Non-CV |
CV: cardiovascular; FM: fulminant myocarditis; HF: heart failure; LVEF: left ventricular ejection fraction.
There was a statistically significant association between all-cause mortality and severe complications during the index admission (p<0.001). A composite event of readmission and cardiovascular-related death was also significantly associated with FM during the index admission (p=0.014), as illustrated by the Kaplan-Meier curve in Figure 1. Additionally, higher NT-proBNP levels (5471±1447 pg/mL vs. 748±133 pg/mL, p<0.001) and reduced LVEF (23.5±4% vs. 58.6±0.6%, p=0.005) were observed in patients with severe complications during the index admission. Both elevated NT-proBNP levels and reduced nadir LVEF were strongly associated with all-cause mortality, with p-values of <0.001 and 0.01, respectively.

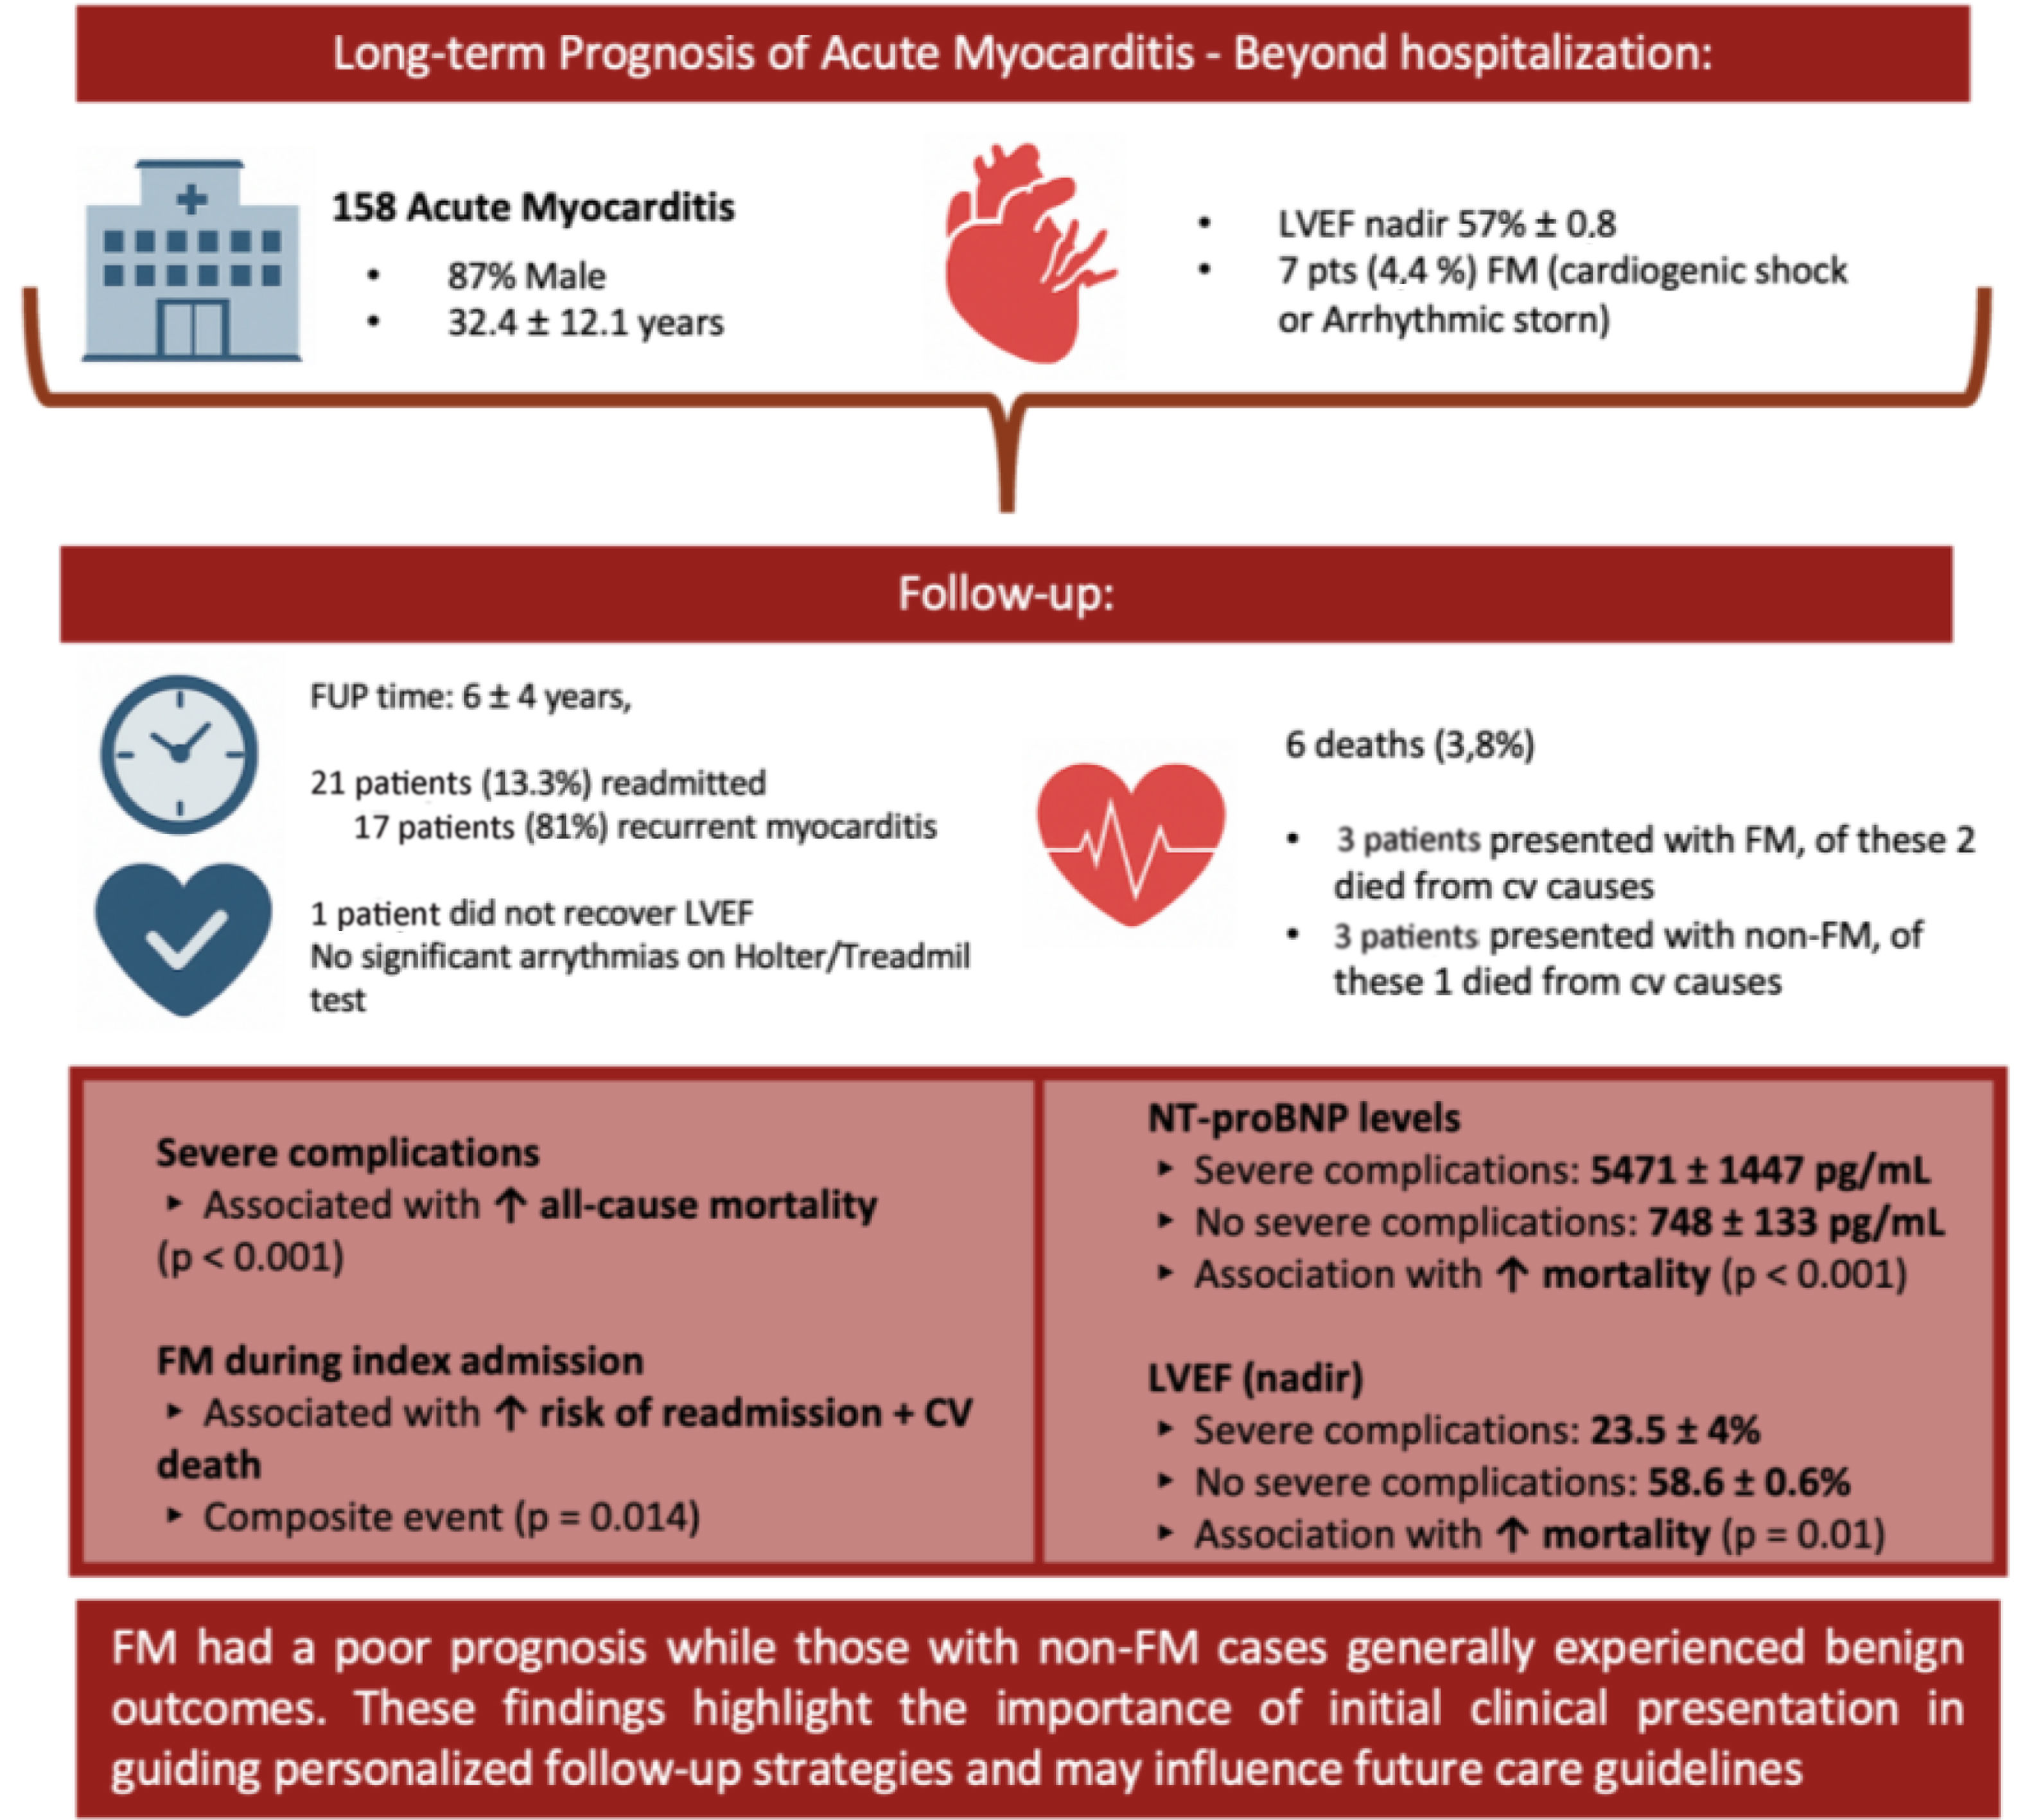
Central illustration. The prognostic impact of acute myocarditis. Fulminant myocarditis was associated with higher mortality and recurrence rates. Two of three fulminant myocarditis patients died from cardiovascular causes, while only one of three deaths in non-fulminant case was cardiovascular. Most non-fulminant myocarditis patients had favorable outcomes with preserved function and no significant arrhythmias during follow-up. CV: cardiovascular; FM: fulminant myocarditis; FUP: follow-up; LVEF: left ventricular ejection fraction.
The main findings of our study can be summarized as follows: (1) AM in adults had a mostly benign clinical course, with favorable short and long term prognosis; (2) the small but non-negligible minority of patients with FM had a much worse prognosis – despite surviving the initial episode, a similarly severe recurrent episode was often fatal; (3) by contrast, the dominant mild clinical presentation cases were uneventful during both hospitalization and FUP; (4) most patients did not experience recurrence, but for those who do, the clinical presentation tended to reproduce that of the original episode, for both mild and severe cases.
The demographic and clinical characteristics of this myocarditis population are aligned with those reported in previous studies. The cohort consisted primarily of young adults aged 20–51 years, with a male predominance – a typical profile for myocarditis. Most patients presented with chest pain and mild dyspnea, which is consistent with findings in other studies (1, 2, 4). These parallels underscore the representativeness of our population.
In our cohort, patients with uncomplicated myocarditis showed favorable outcomes during FUP, with only two non-cardiovascular deaths reported. Annual evaluations, including echocardiograms, Holter monitoring and exercise testing, revealed no significant changes, confirming the benign course of the disease. These findings are consistent with previous studies, such as Ammirati et al., which reported no changes in LVEF, arrhythmias or cv mortality in 132 similar patients.17 Our study underscores not only the low event rate but also the preserved functional status of these patients, as evidenced by normal imaging, stable rhythms, and good exercise performance.
In a study by Grani et al. including a large population of patients with myocarditis, the presence/absence of LVEF <40% and the presence/absence of LGE stratified patients at 12-years’ FUP for MACE. In our study, the subgroup of uncomplicated myocarditis showed a normal LVEF at baseline, but the presence of LGE was not a predictor of mortality, possibly because most patients showed this abnormality.18
The reported incidence of FM has evolved over time, with older studies indicating higher rates compared to more recent ones. This trend likely reflects advancements in diagnostic capabilities, which now allow for the identification of myocarditis in patients with milder clinical presentations. Furthermore, differences in patient cohorts and study design may also explain, at least in part, the discrepancies with previous studies, which generally included smaller numbers of patients and employed nonuniform criteria for diagnosing AM without distinguishing between those with fulminant and non-fulminant presentations. In our prospective study, the incidence of FM was 4.4%, aligning closely with rates reported in recent observational studies, such as 7.4% by Grossman et al. (2017) and 8% by Younis et al.9,19
Additionally, when comparing our findings with studies that have reported significant outcomes during FUP, such as the Danish Civil Registration System's nationwide registry-based study of 2523 hospitalized patients with myocarditis, 419 of whom presented with severe cases,20 it is important to note that this study did not distinguish between mild and severe initial presentations. This limitation may have contributed to higher reported rates of heart failure, ventricular arrhythmias, cardiac arrest, and ICD implantation compared to our findings.
A concerning complication of myocarditis is the development of DCM. Traditionally, it has been considered relatively common, with estimates suggesting that 25% of patients may develop persistent cardiac dysfunction, and 12–25% may experience acute deterioration, progressing to end-stage DCM or requiring heart transplantation, as outlined in the 2013 European Society of Cardiology position statement. However, our findings contrast with these estimates, as only one patient developed DCM, who was initially admitted with LVEF <50%. Similar to our results, recent studies, such as Grossman et al. (2017), have reported a low incidence of DCM in myocarditis patients – only 2.5% of patients developed DCM in that cohort. These findings suggest a lower-than-expected incidence of DCM, indicating a more favorable long-term prognosis for patients with myocarditis, especially if the initial presentation is mild.
As previously discussed, cardiac mortality in the long term was predominantly observed in patients with complicated myocarditis. Our findings are consistent with recent studies, such as Ammirati et al., which analyzed a cohort of 443 patients – 118 with complicated myocarditis and 325 with uncomplicated myocarditis. In this study, the overall mortality rates were 6 (5.7%) in the complicated myocarditis group compared to 1 (0.3%) in the uncomplicated myocarditis group.10 Similarly, Grossman et al. reported notably higher mortality rates in the FM group (26.7%) compared to the non-fulminant group (2.7%), with deaths primarily attributed to non-cardiac causes.19 It is also worth mentioning that patients who died of FM during FUP did so within the initial 2 years after the initial diagnosis. Only 2 patients with uncomplicated AM died during FUP, and the causes were non-CV.
In this study, 13.3% of patients experienced readmission, with 81% of these cases occurring within the initial 3 years of FUP. Remarkably, severity during recurrence was evident exclusively in patients with an initially severe presentation as presented in other studies as well, such as in Grossman et al; Ammirati et al. and Younis et al.8,10,19 In our cohort, we were not able to identify any predictors of recurrence, using either hospitalization or FUP data.
The study reinforces the significant challenge of predicting future events in the context of myocarditis, highlighting the urgent need for ongoing research aimed at identifying predictive factors and refining risk stratification strategies. These data also make clear that regular FUP and routine examinations are unnecessary after the diagnosis of uncomplicated AM. Such measures should be reserved for cases with complicated initial presentations, given that these patients have an increased risk of complications and mortality during FUP.
LimitationsOur study has several relevant limitations. It is a single-center study. Early and routine availability of CMR was sometimes limited, leading to a presumed diagnosis in a minority of patients. Left ventricular endomyocardial biopsy only became available in our center from 2017 onwards. Prior to that, only right ventricular endomyocardial biopsy was available and was seldom undertaken.
Notably, while there was no clinical loss to FUP, as either in-office or phone FUP was available for all patients, a sizable proportion of patients became unwilling to undergo complementary examinations since they remained entirely asymptomatic. This was especially true for Holter, treadmill and, especially, CMR.
Future avenuesDespite the overall good prognosis we observed in the cohort presented here, the very long-term prognosis of AM in adult patients remains poorly characterized. We aim to continue following these patients on a long-term basis.
ConclusionsIn a cohort of adult patients with new-onset AM, most patients had an uneventful clinical course both acutely and long-term, provided the initial presentation was non-fulminant, as evidenced by both the paucity of events and normal functional status in echocardiography, Holter or treadmill tests.
Notwithstanding, the prognosis of the small minority of patients who experienced a FM picture, was dismal. Despite surviving the initial episode, recurrence was very frequent and often fatal. Furthermore, a fulminant clinical presentation was the sole predictor of a poor prognosis.
As a result, this study emphasizes the crucial role of risk stratification linked to the initial presentation. Uncovering the generally benign course in most AM cases calls into question the need for universally rigorous FUP. Tailoring strategies to the initial presentation, especially for high-risk individuals, emerges as a nuanced approach. These findings may influence future guidelines, underscoring the importance of personalized care.
FundingNo funding grants were used for this study.
Conflicts of interestThe authors have no conflicts of interest to declare.
I would like to express my sincere gratitude to my colleagues, especially Margarida Martins, for her invaluable contribution to the development of the statistical analysis for this study. I also wish to extend my thanks to all those who participated in the review of this manuscript. A special thanks goes to Professor Miguel Menezes, who has followed these patients for many years and conceptualized this project from its inception. Without his unwavering support, dedication, and guidance, this work would not have been possible.
The following are the supplementary data to this article:




