





Atrial flutter (AFL) is a common supraventricular arrhythmia, often associated with an increased risk of thromboembolic events. Current guidelines recommend catheter ablation of the cavotricuspid isthmus as first-line therapy. However, thrombotic risk assessment remains essential, particularly through transesophageal echocardiography (TEE) to detect left atrial appendage (LAA) thrombi prior to ablation. This study aimed to determine the prevalence of LAA thrombi in patients with AFL undergoing pre-ablation TEE and to identify clinical, laboratory, and echocardiographic variables associated with thrombus formation.
MethodsThis retrospective, single-center, cohort study analyzed TEE reports of patients with AFL treated between 2015 and 2022 at a tertiary referral center in Brazil. Demographic, clinical, laboratory, and echocardiographic data were collected and analyzed using chi-square tests, Student's t-tests, and multivariate logistic regression. A clinical score incorporating key predictive variables was developed to improve risk stratification. Receiver operating characteristic (ROC) curves, net reclassification improvement (NRI), and five-fold stratified cross-validation were used for performance assessment.
ResultsA total of 528 patients were included (mean age: 63.9±14.2 years; 69.9% male). Pre-ablation TEE identified LAA thrombi in 18.8% of cases. Independent predictors of thrombus formation included heart failure, prior stroke/TIA, left atrial enlargement, and reduced glomerular filtration rate. The clinical score demonstrated 85.4% sensitivity (95% CI: –), 53.2% specificity (95% CI: –), and an area under the curve (AUC) of 0.726, indicating improved discriminative ability compared to the CHA2DS2-VASc score (87.6% sensitivity [95% CI: –], 22.2% specificity [95% CI: –]). The model achieved a positive NRI of 28.8% compared with the CHA2DS2-VASc score.
ConclusionsThe prevalence of LAA thrombus was higher than previously reported in similar populations. The newly developed clinical score showed improved discriminative performance relative to the CHA2DS2-VASc score and may help identify high-risk patients who could benefit from pre-ablation TEE in the context of AFL.
O flutter auricular (FLA) é uma arritmia supraventricular comum, frequentemente associada a risco aumentado de eventos tromboembólicos. As diretrizes atuais recomendam a ablação por cateter do istmo cavotricúspide como tratamento de primeira linha. No entanto, a avaliação do risco trombótico permanece essencial, especialmente por meio da ecocardiografia transesofágica (ETE) para detectar trombos no apêndice auricular esquerdo (AAE) antes da ablação. Este estudo teve como objetivo determinar a prevalência de trombos no AAE em doentes com FLA submetidos à ETE pré-ablação e identificar variáveis clínicas, laboratoriais e ecocardiográficas associadas à formação de trombos.
MétodosEstudo de coorte retrospectivo, transversal e de centro único que analisou laudos de ETE de doentes com FLA tratados entre 2015 e 2022 em um centro terciário no Brasil. Foram recolhidos dados demográficos, clínicos, laboratoriais e ecocardiográficos, analisados por testes do qui-quadrado, teste t de Student e regressão logística multivariada. Um score clínico foi desenvolvido a partir de variáveis preditivas-chave para aprimorar a estratificação de risco. Curvas ROC, índice de reclassificação líquida (NRI) e validação cruzada estratificada em cinco blocos foram utilizados para avaliação de desempenho.
ResultadosForam incluídos 528 doentes (idade média: 63,9±14,2 anos; 69,9% homens). A ETE pré-ablação identificou trombos no AAE em 18,8% dos casos. Preditores independentes incluíram insuficiência cardíaca, AVC/AIT prévio, aumento do átrio esquerdo e taxa de filtração glomerular reduzida. O score clínico apresentou sensibilidade de 85,4% (IC 95%: –), especificidade de 53,2% (IC 95%: –) e área sob a curva (AUC) de 0,726, indicando melhor capacidade discriminatória em comparação ao CHA2DS2-VASc (sensibilidade de 87,6% [IC 95%: –], especificidade de 22,2% [IC 95%: –]). O modelo apresentou NRI positivo de 28,8% em relação ao CHA2DS2-VASc.
ConclusõesA prevalência de trombos no AAE foi superior à previamente relatada em populações semelhantes. O score desenvolvido demonstrou desempenho discriminatório aprimorado em relação ao CHA2DS2-VASc e pode auxiliar na identificação de doentes com maior risco tromboembólico que se beneficiariam da ETE antes da ablação do FLA.

Atrial fibrillation (AF) is the most prevalent sustained arrhythmia in clinical practice, associated with significant morbidity and mortality, largely due to its embolic potential and elevated risk of stroke.1 Atrial flutter (AFL), although less common, often coexists with AF and carries a similarly heightened risk of thromboembolic events.4 According to the literature, the incidence of AFL ranges from 88 per 100000 people per year globally, while in Brazil, AFL and AF accounted for over 335000 hospitalizations between 2019 and 2023.2,3
Atrial flutter encompasses a heterogeneous group of arrhythmias, including typical CTI-dependent right atrial flutter and atypical forms, frequently originating from the left atrium, particularly in patients with prior atrial fibrillation ablation. These subtypes may differ in underlying atrial substrate and thromboembolic risk. However, data addressing LAA thrombus prevalence across the broader spectrum of AFL referred for ablation remain limited.
Catheter ablation, specifically cavotricuspid isthmus (CTI) ablation, is the recommended first-line therapy for AFL, demonstrating a procedural success rate of approximately 90% with a low complication rate.5 Despite its efficacy, the risk of post-ablation thromboembolic events persists, driven by the potential reversion to sinus rhythm or myocardial injury during ablation.1 To mitigate this risk, the 2020 ESC guidelines for AF recommend either at least 3 weeks of effective oral anticoagulation before the procedure or TEE to exclude left atrial appendage thrombus.6 Although these recommendations were developed for AF, the ESC advises that patients with AFL should be managed according to the same anticoagulation principles. More recently, the 2024 ESC AF guidelines recommend initiating oral anticoagulation ≥3 weeks prior to catheter ablation in patients at elevated thromboembolic risk, performing the procedure on uninterrupted anticoagulation, and considering pre-procedural cardiac imaging to exclude thrombus in high-risk patients despite anticoagulation.7
However, evidence suggests that even in anticoagulated patients, the presence of thrombi in the LAA remains a concern. Previous studies have reported thrombus prevalence rates of up to 8% in patients using vitamin K antagonists (VKAs) and 4% in those treated with new oral anticoagulants (NOACs).8 Identifying clinical predictors of thrombus formation is therefore essential to optimize the use of TEE, particularly in high-risk populations. Atrial flutter encompasses a heterogeneous group of arrhythmias, including typical CTI-dependent right atrial flutter and atypical forms, frequently originating from the left atrium, particularly in patients with prior atrial fibrillation ablation. These subtypes may differ in underlying atrial substrate and thromboembolic risk. However, data addressing LAA thrombus prevalence across the broader spectrum of AFL referred for ablation remain limited.
ObjectivesThe present study aimed to evaluate the prevalence of LAA thrombi in AFL patients referred for ablation and to identify key clinical and echocardiographic variables associated with thrombus formation, with the goal of developing a practical clinical score to aid in risk stratification.
MethodsStudy design and populationThis study is a retrospective, single-center, cohort study, based on the analysis of TEE reports from patients in the Brazilian public health system who underwent AFL ablation at the Instituto de Cardiologia in Porto Alegre, Brazil, between 2015 and 2022. Patients were included if they were 18 years or older, had a confirmed diagnosis of AFL, and underwent TEE to evaluate the presence of LAA thrombus prior to ablation. Both typical cavotricuspid isthmus CTI-dependent and non-CTI-dependent atrial flutter patterns were included. Due to the retrospective nature of the study and reliance on ECG-based diagnosis at the time of referral, a systematic distinction between typical right atrial flutter and left atrial flutter was not consistently available in the medical records. Similarly, detailed information regarding prior atrial arrhythmia ablation was not uniformly documented and therefore could not be reliably quantified. AFL was identified based on the 12-lead ECG pattern at diagnosis, characterized by regular atrial activity with flutter waves and a ventricular response consistent with atrial flutter rhythm, irrespective of CTI dependency. Patients in sinus rhythm on the day of the procedure were excluded to avoid confounding by non-AFL atrial activity and to minimize selection bias related to rhythm variability at the time of TEE. Additional exclusion criteria included the presence of LAA occlusion devices, active malignancy, and recent thromboembolic events. Patients with conditions associated with an increased risk of intracardiac thrombus formation or stroke despite adequate anticoagulation were deliberately included to reflect the heterogeneity and real-world thromboembolic risk of the AFL population.
Data collectionPatient demographics, clinical comorbidities, anticoagulation status, and echocardiographic findings were collected from medical records. Vascular disease was defined as documented history of coronary artery disease, peripheral arterial disease, aortic plaque or prior myocardial infarction. Specific etiologies such as cardiac amyloidosis, rheumatic heart disease, hypertrophic cardiomyopathy, as well as detailed information on prior cardiac surgeries or the presence of mechanical prosthetic valves were not consistently available in the electronic medical records and therefore could not be extracted.
For patients on NOACs, adherence data (last dose timing, refill history, or pill counts/interview) were not systematically recorded in the medical records and were therefore unavailable for this analysis. Adherence to direct oral anticoagulants (DOACs) was thus considered unknown.
The TEE reports were reviewed to assess the anteroposterior diameter of the left atrium (LA), left ventricular ejection fraction (LVEF), and the presence of thrombi in the LAA.
The presence of LAA thrombus was defined as a discrete, well-circumscribed echodense mass within the LAA, distinct from the endocardium, visible in multiple planes (0°, 45°, 90°, and 135°), and persisting throughout the cardiac cycle. Dense spontaneous echo contrast (SEC) or ‘sludge’ was characterized by a swirling echogenic pattern without a definite mass, occupying the LAA cavity, and not classified as thrombus. Images were obtained following standard TEE protocols with optimized gain and sweep speed settings; contrast agents were not routinely used. All examinations were performed and reported by board-certified echocardiographers experienced in transesophageal imaging. For the purposes of this study, interpretation was based on official TEE reports available in the medical records. The original images were not re-evaluated; therefore, interobserver variability or blinded adjudication could not be assessed, which is acknowledged as a study limitation.
Data were independently extracted by two reviewers to ensure accuracy and resolve discrepancies. Data validation was performed to minimize bias. Potential confounders were identified a priori based on clinical relevance and prior literature, including age, sex, hypertension, diabetes, vascular disease, anticoagulation status, left ventricular dysfunction, and renal function. These variables were included in the multivariate models to adjust for confounding.
Ethics statementThe study protocol was approved by the Research Ethics Committee of IC-FUC, and informed consent was obtained from all patients, in accordance with Resolution 466/2012 of the Brazilian National Health Council.
Statistical analysisData analysis was conducted using SPSS version 25. For continuous variables, mean and standard deviation were reported for normally distributed data, while median and interquartile range (IQR) were used for non-normally distributed data. Categorical variables were presented as frequencies and percentages.
Comparative analyses between groups (patients with and without LAA thrombi) were performed using chi-square tests for categorical variables and Student's t-test for continuous variables. A multivariate logistic regression model was employed to determine the independent predictors of thrombus occurrence, considering variables with a p-value <0.05 in univariate analysis. Missing data were handled using a complete-case analysis approach. Variables with missingness <5% were analyzed without imputation. GFR and NRI had higher missingness rates and were therefore included only in complete-case multivariate models. No multiple imputation was performed.
The receiver operating characteristic (ROC) curve was used to assess the discriminatory ability of the newly developed clinical score, with area under the curve (AUC), sensitivity, and specificity calculated for different cutoff points. The comparison between AUCs was performed using the non-parametric DeLong test, which is the standard method for comparing correlated ROC curves.
A stratified five-fold cross-validation was conducted to assess the robustness and generalizability of the predictive model. The dataset was divided into five subsets, with the model trained on four subsets and tested on the fifth, repeating this process for all subsets. Mean AUC, sensitivity, and specificity values across all five subsets were calculated to provide a comprehensive evaluation of model performance.
Additionally, the net reclassification index (NRI) was calculated to compare the performance of the clinical score with the CHA2DS2-VASc score. A category-free NRI approach was applied, quantifying both upward and downward reclassification without predefined risk categories. The NRI analysis quantified the proportion of patients correctly reclassified into higher or lower risk categories by the new score compared to the CHA2DS2-VASc score, separately for thrombus-positive and thrombus-negative cases. NRI estimates were reported along with 95% confidence intervals derived from 2000 bootstrap resamples.
A post hoc power analysis was conducted for transparency, using conventional assumptions (α=0.05, β=0.20) commonly applied in retrospective observational studies. Under these parameters, the final sample size of 528 participants provided sufficient statistical power (>80%) to detect moderate associations between clinical predictors and LAA thrombus.
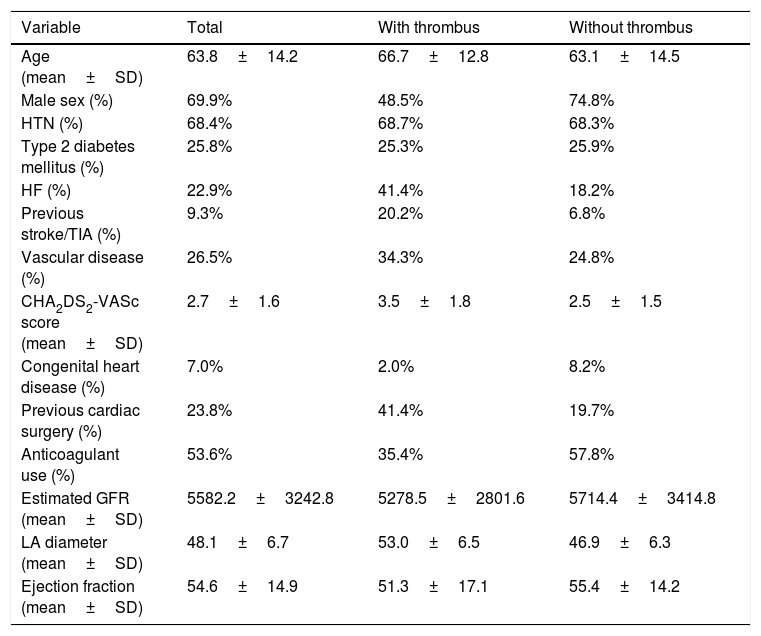
ResultsPatient characteristicsDuring the study analysis period, 528 patients diagnosed with AFL who underwent pre-ablation assessment with TEE were included. The mean age was 63.9±14.2 years, with 122 (23.1%) patients aged between 65 and 74 years and 96 (18.2%) aged 75 years or older. Among them, 369 (69.9%) were men. Regarding risk comorbidities, 361 (68.4%) patients had hypertension (HTN), 136 (25.8%) were diabetic, and 121 (22.9%) were diagnosed with heart failure (HF). Additionally, 49 (9.3%) had a previous stroke or TIA, 140 (26.5%) had a history of vascular disease, 37 (7%) had congenital heart disease, and 125 (23.7%) had undergone prior cardiac surgery. The mean CHA2DS2-VASc score was 1.9±0.43, with a median of 2, indicating an overall moderate risk of thromboembolic events in the studied population. Among the 528 patients, the most common scores were 3 (23.7%) and 2 (22.7%). Moreover, the mean LVEF and mean LA size were 54.65±14.9% and 48.1±6.73 mm, respectively. About renal function, assessed by the glomerular filtration rate (GFR) calculated using the MDRD formula, we observed a mean of 66.96±24.4 mL/min/1.73 m2. Clinical characteristics of the 528 patients are described in Table 1. Missing data were handled using a complete-case analysis approach. Variables with missingness <5% were analyzed without imputation. GFR and NRI had higher missingness rates and were therefore included only in complete-case multivariate models. No multiple imputation was performed.
Patient characteristics – clinical and echocardiographic characteristics of the sample, stratified according to the presence of thrombus on transesophageal echocardiography.
| Variable | Total | With thrombus | Without thrombus |
|---|---|---|---|
| Age (mean±SD) | 63.8±14.2 | 66.7±12.8 | 63.1±14.5 |
| Male sex (%) | 69.9% | 48.5% | 74.8% |
| HTN (%) | 68.4% | 68.7% | 68.3% |
| Type 2 diabetes mellitus (%) | 25.8% | 25.3% | 25.9% |
| HF (%) | 22.9% | 41.4% | 18.2% |
| Previous stroke/TIA (%) | 9.3% | 20.2% | 6.8% |
| Vascular disease (%) | 26.5% | 34.3% | 24.8% |
| CHA2DS2-VASc score (mean±SD) | 2.7±1.6 | 3.5±1.8 | 2.5±1.5 |
| Congenital heart disease (%) | 7.0% | 2.0% | 8.2% |
| Previous cardiac surgery (%) | 23.8% | 41.4% | 19.7% |
| Anticoagulant use (%) | 53.6% | 35.4% | 57.8% |
| Estimated GFR (mean±SD) | 5582.2±3242.8 | 5278.5±2801.6 | 5714.4±3414.8 |
| LA diameter (mean±SD) | 48.1±6.7 | 53.0±6.5 | 46.9±6.3 |
| Ejection fraction (mean±SD) | 54.6±14.9 | 51.3±17.1 | 55.4±14.2 |
In terms of anticoagulant use, 280 (53%) were on NOACs, and 176 (33%) were taking warfarin. Of the remaining patients, 66 (12.5%) were not anticoagulated, and 6 (1.1%) had no recorded data. The reasons for lack of anticoagulation in this subgroup were not documented in medical records, as this information was not systematically collected in the retrospective database. In this subgroup, the mean CHA2DS2-VASc score was 2.9±2.0, with a median of 3, indicating a high thromboembolic risk despite the absence of anticoagulation therapy. For patients anticoagulated with warfarin, the mean NRI was 1.91±0.82 and the mean time in the therapeutic range (TTR) was 42.91±32.57%, highlighting considerable variability in anticoagulation control. Furthermore, thrombi were observed in TEE in 99 (18.8%) patients, while 428 (81.2%) had no thrombi.
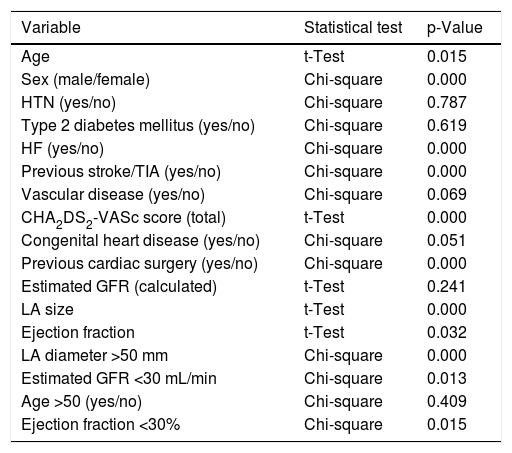
Thrombus related factorsAs shown in Table 2, the Student's t-test for independent samples revealed that age was significantly higher in the thrombus group than in the non-thrombus group (p=0.015), with a mean difference of 3.60 years (95% CI: 0.49–6.71). Additionally, LA size was markedly larger in the thrombus group (p<0.001), with a mean difference of 6.06 mm (95% CI: 4.64–7.48). The t-test also revealed lower LVEF in the thrombus group (p=0.032), with a mean difference of −4.13% (95% CI: −7.47 to −0.79). No statistically significant correlation was found between GFR and thrombi (p=0.241).
Bivariate analysis of clinical and echocardiographic variables associated with LAA thrombus in patients with AFL.
| Variable | Statistical test | p-Value |
|---|---|---|
| Age | t-Test | 0.015 |
| Sex (male/female) | Chi-square | 0.000 |
| HTN (yes/no) | Chi-square | 0.787 |
| Type 2 diabetes mellitus (yes/no) | Chi-square | 0.619 |
| HF (yes/no) | Chi-square | 0.000 |
| Previous stroke/TIA (yes/no) | Chi-square | 0.000 |
| Vascular disease (yes/no) | Chi-square | 0.069 |
| CHA2DS2-VASc score (total) | t-Test | 0.000 |
| Congenital heart disease (yes/no) | Chi-square | 0.051 |
| Previous cardiac surgery (yes/no) | Chi-square | 0.000 |
| Estimated GFR (calculated) | t-Test | 0.241 |
| LA size | t-Test | 0.000 |
| Ejection fraction | t-Test | 0.032 |
| LA diameter >50 mm | Chi-square | 0.000 |
| Estimated GFR <30 mL/min | Chi-square | 0.013 |
| Age >50 (yes/no) | Chi-square | 0.409 |
| Ejection fraction <30% | Chi-square | 0.015 |
Note: LA: left atrium (mm); LVEF: left ventricular ejection fraction (%); GFR <30 mL/min/1.73 m2 defined by MDRD; vascular disease as defined in “Methods”.
Furthermore, the chi-square test was used to assess the relationship between qualitative variables. A statistically significant association between female sex and thrombus presence (p<0.001) was found. This result suggests that sex plays a relevant role in the occurrence of thrombi, with a potential protective effect on male. Additionally, statistically significant correlations were found between thrombus findings in TEE and HF (p<0.001), as well as stroke/TIA (p<0.001) and previous cardiac surgery (p<0.001). No statistically significant correlation was found between thrombus presence and HTN, diabetes, previous vascular disease and congenital cardiac disease. Moreover, the parameters GFR <30 mL/min, LA >50 mm, LVEF <30%, and age >50 years were created and evaluated using the chi-square test. The results demonstrated a statistically significant association between GFR <30 mL/min and thrombus presence (p<0.05), suggesting that severe renal impairment was linked to a higher risk of thrombus formation. Similarly, LA enlargement (>50 mm) showed a strong statistically significant association with thrombus presence (p<0.001), reinforcing its role as a major predictor of thrombus formation. LVEF <30% was also significantly associated with thrombus presence (p=0.015). In contrast, no statistically significant association was found between age >50 years and thrombus presence (p>0.05), suggesting that, in this sample, age alone was not an independent predictor of thrombus occurrence.
Finally, when comparing anticoagulant use versus non-use and thrombus presence, a statistically significant association was also observed (χ2=53.32, p<0.05), indicating a higher risk of thrombotic events associated with the lack of anticoagulation. However, among the 455 anticoagulated patients, no statistically significant relevance was found between NOAC versus warfarin administration and thrombus occurrence (χ2=1.78; p=0.182).
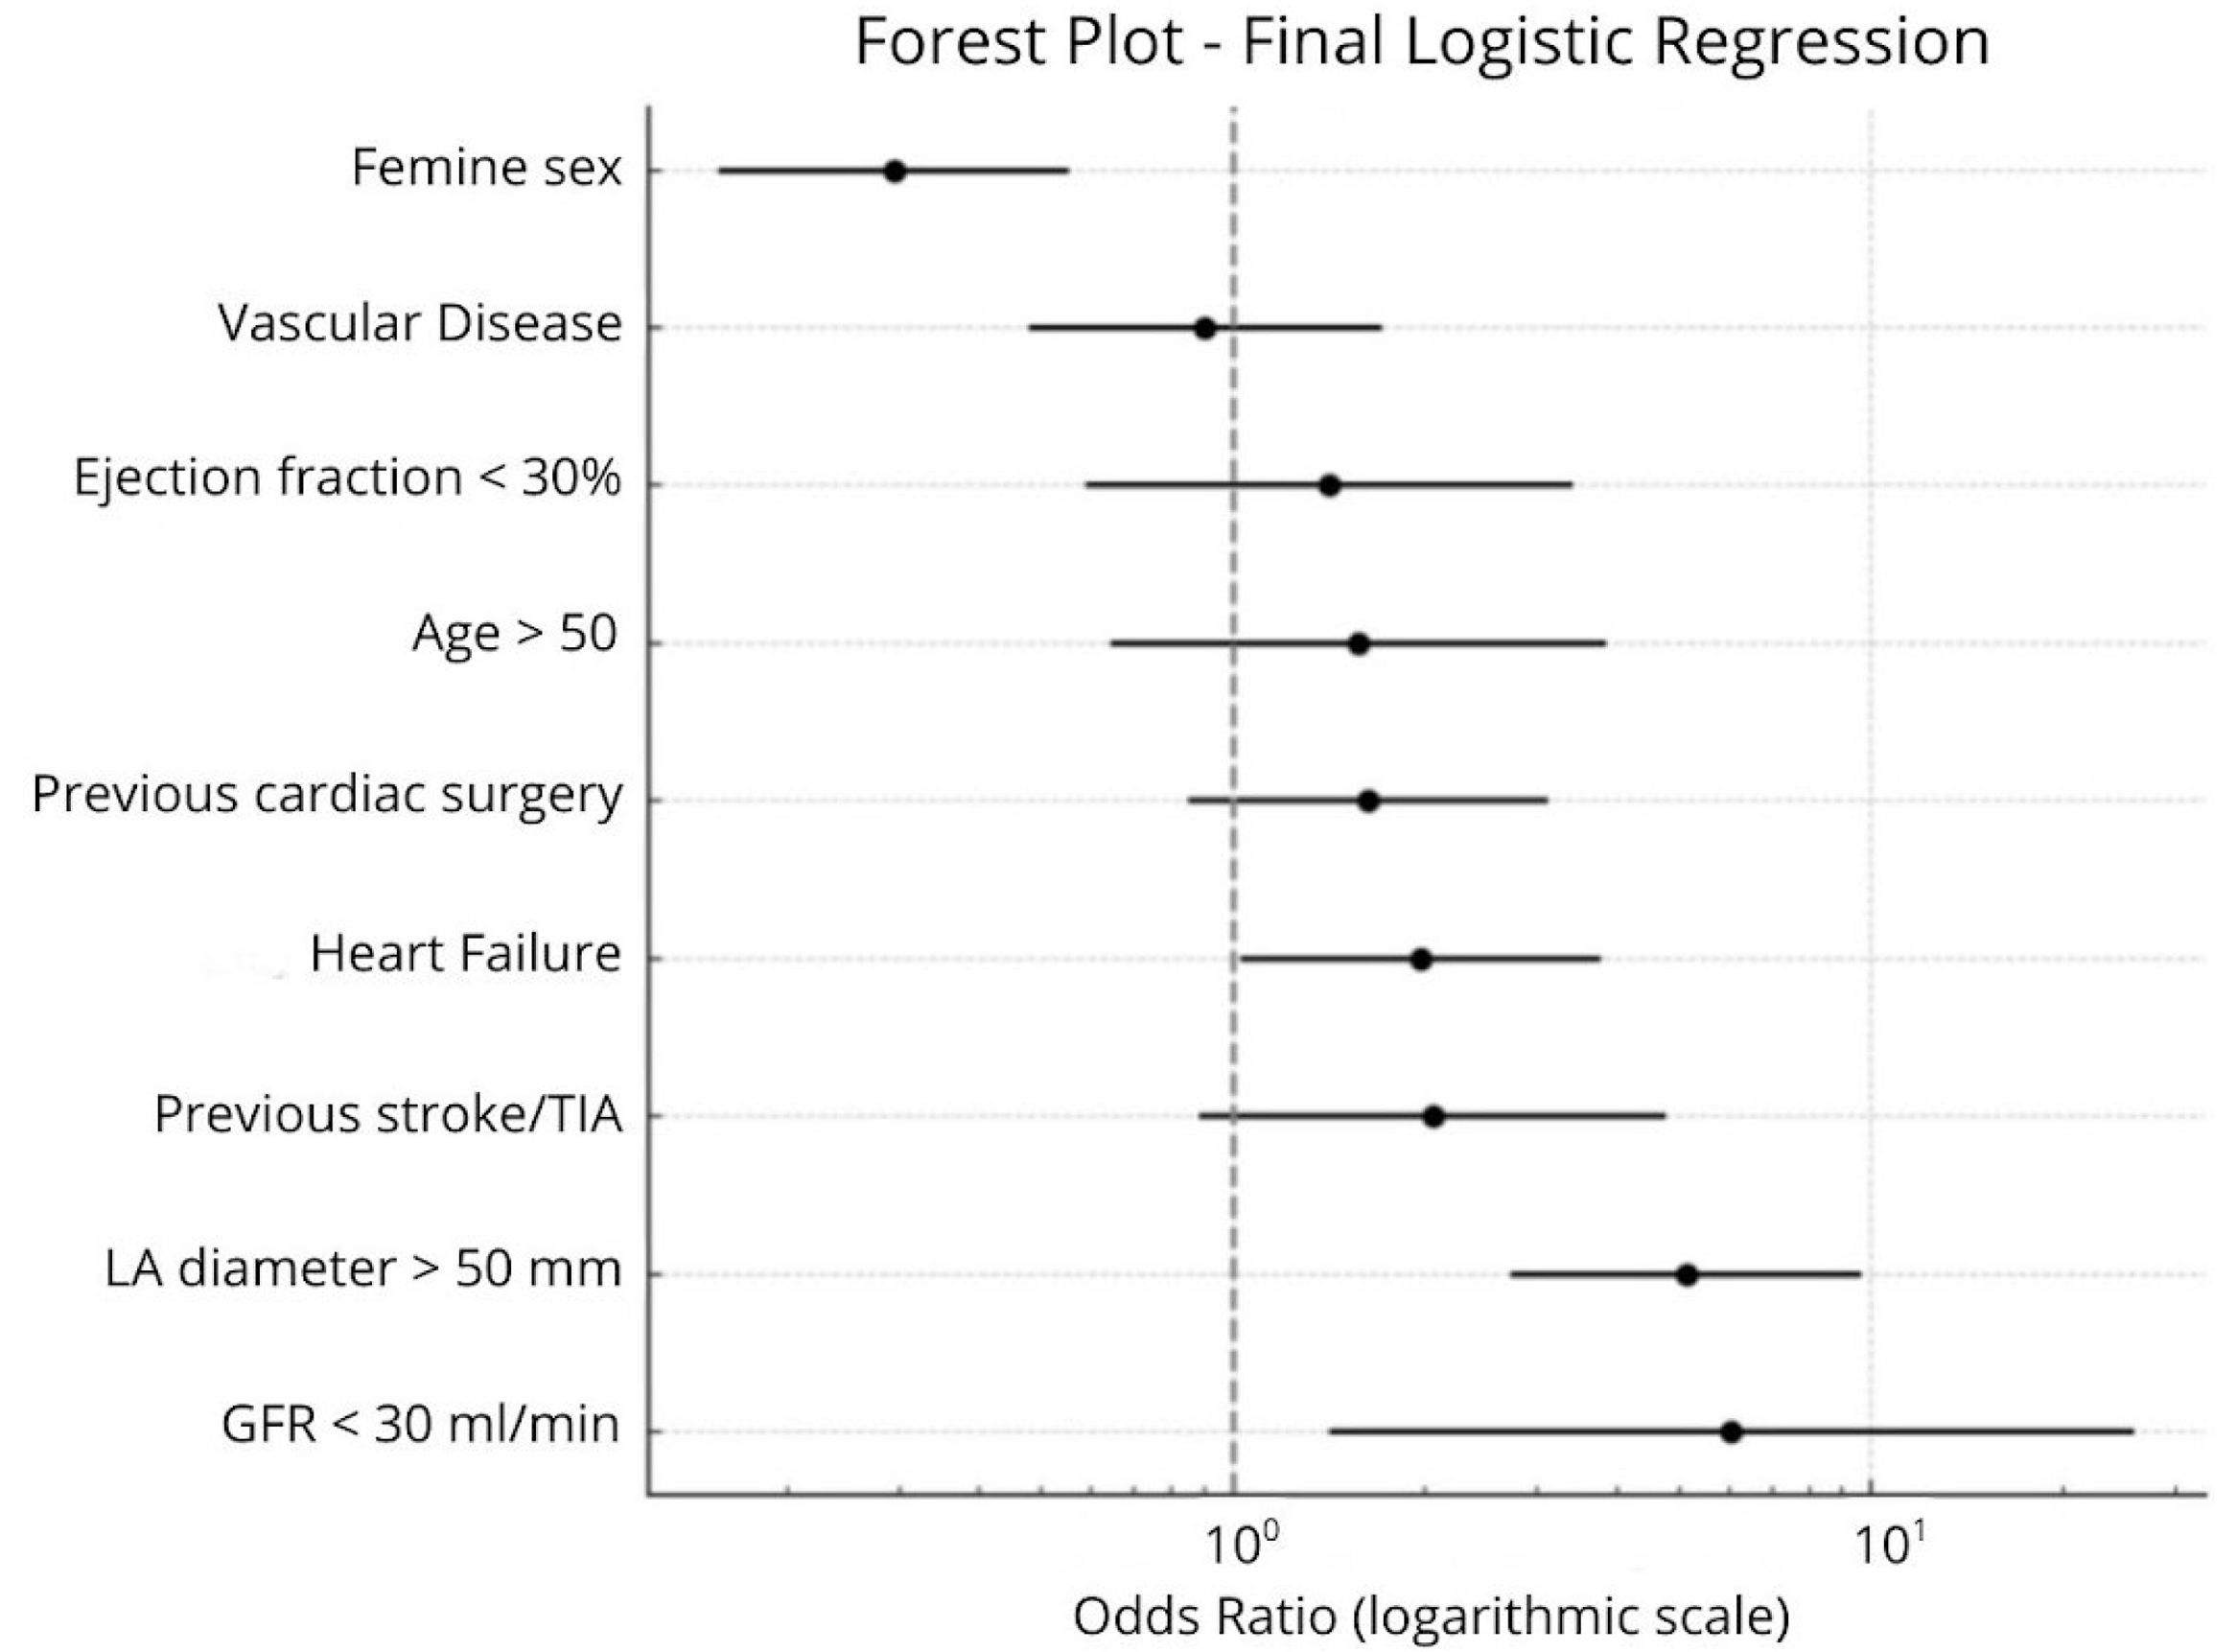
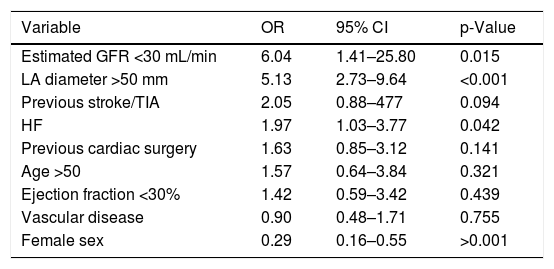
Variables with statistical significance in the bivariate analysis (p<0.05) were included in the multivariate logistic regression using the enter method, and the results are presented in Table 3. The final model included the following variables: sex, HF, previous stroke/TIA, GFR <30 mL/min, LA diameter >50 mm, previous cardiac surgery, vascular disease, LVEF <30%, and age >50 years. In the logistic regression analysis (Figure 1), female sex remained an independent protective factor against LAA thrombus formation (OR=0.294; p<0.001), indicating a significantly lower risk compared to males. Conversely, heart failure (OR=1.966; p=0.042) and reduced glomerular filtration rate (GFR <30 mL/min/1.73 m2; OR=6.038; p=0.015) were confirmed as independent risk factors. Left atrial diameter ≥50 mm was the strongest predictor, associated with a markedly higher risk of thrombus (OR=5.128; p<0.001). Variables such as prior cardiac surgery (p=0.141), age >50 years (p=0.321), previous vascular disease (p=0.755), and left ventricular ejection fraction <30% (p=0.439) showed no statistically significant association with the outcome.
Multivariate logistic regression identifying independent predictors of LAA thrombus formation in patients with AFL.
| Variable | OR | 95% CI | p-Value |
|---|---|---|---|
| Estimated GFR <30 mL/min | 6.04 | 1.41–25.80 | 0.015 |
| LA diameter >50 mm | 5.13 | 2.73–9.64 | <0.001 |
| Previous stroke/TIA | 2.05 | 0.88–477 | 0.094 |
| HF | 1.97 | 1.03–3.77 | 0.042 |
| Previous cardiac surgery | 1.63 | 0.85–3.12 | 0.141 |
| Age >50 | 1.57 | 0.64–3.84 | 0.321 |
| Ejection fraction <30% | 1.42 | 0.59–3.42 | 0.439 |
| Vascular disease | 0.90 | 0.48–1.71 | 0.755 |
| Female sex | 0.29 | 0.16–0.55 | >0.001 |
Note: CI: confidence interval; OR: odds ratio; LA ≥50 mm, LVEF <30%; GFR <30 mL/min/1.73 m2 categorized according to established clinical cutoffs; vascular disease as defined in “Methods”.

The discriminatory performance of the models was assessed based on ROC curves generated from the probabilities estimated by logistic regression. The inclusion of the variable previous stroke/TIA, although not statistically significant in isolation (p=0.094), resulted in an improvement in the AUC (0.801 vs. 0.792) and was maintained in the clinical score due to its predictive contribution and clinical plausibility.
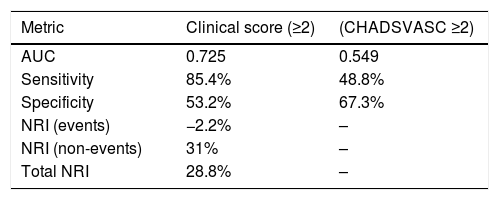
Based on the regression results, a clinical score was developed with weights proportional to the OR values. The clinical score assigns points to specific risk factors as follows: male sex=1 point, previous stroke/TIA=1 point, HF=1 point, GFR <30 mL/min=3 points, and left atrial diameter >50 mm=3 points. In this context, the ROC curve analysis revealed a moderate discriminative performance of the clinical score for identifying patients with LA thrombus. The AUC was 0.725 (95% CI: 0.664–0.786; p<0.001), indicating statistically significant discrimination (Figure 2). The Youden-derived optimal cutoff was ≥3 points; however, to prioritize sensitivity given the clinical relevance of thrombus detection, a cutoff of ≥2 points was selected. With this threshold, the score achieved a sensitivity of 85.4% and a specificity of 53.2%, representing an improvement in specificity with a modest reduction in sensitivity compared with the Youden optimum. For comparison, the CHA2DS2-VASc score ≥2 yielded a sensitivity of 87.6% but a markedly lower specificity of 22.2%, demonstrating that the new model provides fewer false positives while maintaining a high sensitivity.

To further assess reclassification performance, we computed the category-free NRI, using the CHA2DS2-VASc score as the reference model. As shown in Table 4, the NRI for events was −2.2%, indicating minimal change in upward reclassification among patients with thrombus. In contrast, the NRI for non-events was 31.0%, reflecting substantial improvement in correctly reclassifying patients without thrombus into lower-risk categories. The overall NRI was 28.8%, which reveals that the new score provides a meaningful improvement in risk discrimination primarily by reducing false-positive classifications.
Comparative performance of the score.
| Metric | Clinical score (≥2) | (CHADSVASC ≥2) |
|---|---|---|
| AUC | 0.725 | 0.549 |
| Sensitivity | 85.4% | 48.8% |
| Specificity | 53.2% | 67.3% |
| NRI (events) | −2.2% | – |
| NRI (non-events) | 31% | – |
| Total NRI | 28.8% | – |
Note: AUC: area under the curve; CI: confidence interval; NRI: net reclassification improvement; sensitivity and specificity reported at the prespecified cutoff (≥2 points).
Lastly, to assess the robustness and generalization of the proposed clinical score, a stratified five-fold cross-validation was performed. The performance of the clinical score using the cutoff point ≥2 was evaluated in each of the five rounds, with an average AUC of 0.726±0.041, a mean sensitivity of 85.4±5.8%, and a mean specificity of 53.1±7.0%.
DiscussionThrombi prevalenceIn this analysis, the overall prevalence of thrombi detected by TEE in our population was 18.8%, significantly higher than previously reported in the literature. Lurie et al. demonstrated, in a meta-analysis evaluating patients with AF/AFL on oral anticoagulation for at least three weeks, a prevalence of 2.73%.9 Similarly, McCready et al. identified the presence of thrombi in 1.9% of cases despite anticoagulant therapy,10 and Marques et al. found thrombus in the LAA in 2.8% of pre-ablation TEE exams.11 These significant differences support the systematic use of pre-ablation TEE as part of a standard protocol, even in patients under anticoagulation, as the risk of thromboembolism, although reduced in some studies, is present.
The entire sample in this study was composed exclusively of patients treated within the Brazilian public health system, which may have contributed to the high prevalence of LAA thrombi (18.8%) observed in this population. Indeed, evidence suggests that the quality of anticoagulation control in public healthcare settings in Brazil remains suboptimal. Additionally, most anticoagulated patients in this cohort were using warfarin rather than DOACs, despite current ESC guidelines recommending DOACs as the preferred agents for stroke prevention in patients with atrial fibrillation or flutter, given their superior safety and efficacy profiles.7 It is also important to note that the predominance of warfarin use in our cohort reflects the reality of the Brazilian public healthcare system, where access to DOACs remains limited despite current guideline recommendations. A study conducted in a Brazilian public tertiary hospital reported a mean TTR of only 52.2% among patients using warfarin, with just 36.5% of individuals reaching the recommended threshold of TTR ≥60%, which is considered the minimum necessary to reduce thromboembolic and hemorrhagic events.12 In our sample, the mean TTR among patients on warfarin was even lower (42.91%), further underscoring the fragility of anticoagulation control in this group. Additionally, 12.5% of patients were not on any anticoagulation therapy, despite being in a clinically high-risk context. This may reflect challenges in accessing specialized consultations, regular laboratory testing, and potentially socioeconomic or logistical barriers commonly encountered in populations served by SUS. These factors, combined with NRI instability during the initiation phase of warfarin therapy – which has been associated with a 4.94-fold increased risk of ischemic stroke and a 3.35-fold increased risk of bleeding according to Secco et al. – may partly explain the elevated thrombus prevalence observed. Nevertheless, these interpretations should be viewed as hypothesis-generating, given the absence of systematic data on DOAC adherence and the potential selection of higher-risk patients referred for TEE. Future studies specifically designed to evaluate anticoagulation quality, adherence, and healthcare access are warranted to clarify this association.
Risk factorsSeveral risk factors have been associated with the presence of thrombi in the LAA, with sex, age, and impaired cardiac function being the most prominent. In the present study, male sex, HF, prior stroke/TIA, and previous cardiac surgery were identified, by chi-square test, as having a stronger association with thrombotic events. Moreover, age was significantly higher in the thrombus group compared to the non-thrombus group (p=0.015).
We found a significantly larger LA size in the thrombus group (p<0.001), reinforced by the logistic regression that described LA diameter ≥50 mm as the strongest predictor, classified as a very high-risk factor for thrombus development (OR=5.128; 95% CI: 2.726–9.645; p<0.001). The literature already demonstrated this association, McCready et al. identified an average LA size of 50.6±6.2 mm in patients with thrombus compared to 44.2±7.6 mm in those without (p=0.006).10
The multivariable analysis confirmed that heart failure (OR=1.97; 95% CI: 1.03–3.77), GFR <30 mL/min (OR=6.04; 95% CI: 1.41–25.80), and LA diameter >50 mm (OR=5.13; 95% CI: 2.73–9.64) were significantly associated with the presence of thrombi, while female sex was reinforced as a protective factor (OR=0.29; 95% CI: 0.16–0.55; p<0.001). However, Rekosz et al. reported the opposite, identifying female sex as a significant risk factor (OR=3.80; 95% CI: 1.59–9.07; p=0.003), with women being 3.8 times more likely than men to develop thrombi.13
In parallel, our analysis showed a statistically significant correlation between CHA2DS2-VASc and the presence of thrombus (χ2=38.25; p<0.001). Other studies support this association. Lurie et al. reported a significantly higher prevalence of thrombi in patients with elevated risk scores, with rates of 0.82% in CHADS2 ≤1 and 4.24% in CHADS2 ≥2 (p<0.001), as well as 1.06% in CHA2DS2-VASc ≤2 and 3.61% in CHA2DS2-VASc ≥3 (p<0.001).9
Regarding anticoagulant therapy, the presence of thrombi in the LAA was significantly higher in patients without anticoagulation (χ2=53.32, p<0.05). Rekosz et al. reinforced this association, demonstrating a prevalence of thrombi of 5.9% in patients without anticoagulation compared to 1.2% in those using anticoagulants.13
Concerning the type of anticoagulation, although the literature has demonstrated a thrombus resolution rate close to 80% with the use of VKAs,14 some studies suggest a lower incidence of thrombi in patients using NOACs compared to VKAs. Yang et al. identified a lower prevalence of thrombi in the LAA in patients anticoagulated with NOACs compared to VKAs (OR=0.59; 95% CI: 0.42–0.84),15 a finding reinforced by Troisi et al., who reported an OR of 0.66 (95% CI: 0.52–0.84) for the presence of thrombi in NOAC users.16 Additionally, data from Rekosz et al. highlight that the risk of thrombosis or grade 4 spontaneous echocardiographic contrast was lower among patients using rivaroxaban (NOACs) (OR=0.42; 95% CI: 0.21–0.87; p=0.027) and higher in those using VKAs (OR=2.49; 95% CI: 1.15–5.39; p=0.018),13 further supporting the influence of the type of anticoagulant on thrombus prevention in the LAA.
However, our analysis did not find statistical significance between the administration of NOACs versus warfarin and the occurrence of thrombi (χ2=1.78; p=0.182). This finding aligns with the study by Lurie et al., who also did not identify a significant difference in thrombus prevalence when comparing patients anticoagulated with NOACs versus VKAs (2.8% vs. 3.12%; p=0.674).10
Clinical scoreIn this study, we developed a simple and practical clinical score to predict the presence of thrombus in TEE, based on variables significantly associated with the outcome by multivariate logistic regression. The clinical score assigns points proportional to the OR values: male sex=1 point, previous stroke/TIA=1 point, HF=1 point, GFR <30 mL/min=3 points, and LA diameter >50 mm=3 points.
The performance of the proposed score was assessed using the ROC curve, with an AUC of 0.726 in cross-validation. For comparison, the area under the ROC curve for the CHA2DS2-VASc score in predicting thrombus was 0.60. The difference between AUCs did not reach statistical significance when tested through bootstrap analysis (1000 samples), indicating only a modest improvement in discrimination. The comparison between AUCs was performed using bootstrap resampling rather than the DeLong test.
Otherwise, the CHA2DS2-VASc score demonstrated a sensitivity of 87.6% and a specificity of 22.2% at a cutoff of ≥2, while our new clinical score (cutoff ≥2) showed a sensitivity of 85.4% and a specificity of 53.2%. Compared to the CHA2DS2-VASc score, the clinical score exhibited lower sensitivity but provided a more balanced distribution between sensitivity and specificity. The CHA2DS2-VASc score achieved maximum sensitivity (100%) but with lower specificity. This indicates that while the new score does not improve sensitivity, it meaningfully reduces false positives by offering higher specificity. Overall, the discriminative performance of the new score can be considered moderate, consistent with the AUC values observed in cross-validation.
The clinical score demonstrated superior discriminatory performance compared to the CHA2DS2-VASc score, with a higher area under the ROC curve and a positive NRI, particularly among patients without thrombus. Although the NRI was positive (+28.8%), most of the improvement occurred among non-events (patients without thrombus), reflecting fewer false-positive classifications rather than improved detection of thrombus itself. The NRI for events was slightly negative (−2.2%), indicating minimal impact on upward reclassification for thrombus cases.
Cross-validation also confirmed the consistency of the predictive metrics, reinforcing the consistency of the score's performance even when assessed in different subsets of the total population, increasing its clinical applicability. Thus, the new score may serve as a complementary tool to CHA2DS2-VASc rather than a replacement. While CHA2DS2-VASc prioritizes sensitivity and is useful for initial screening, the clinical score offers better specificity, potentially reducing unnecessary TEEs. Importantly, all thrombi identified by the new score were also detected by CHA2DS2-VASc, supporting a combined approach to optimize patient selection and procedural safety.
Previous scores proposed for predicting left atrial thrombus, such as CATES and CLOTS-AF, were developed primarily in populations with atrial fibrillation undergoing TEE prior to cardioversion and therefore differ substantially from the clinical scenario evaluated in the present study. CATES included only 180 patients and relied on biomarkers and echocardiographic indices not routinely available in the pre-ablation setting, while CLOTS-AF, although larger, combined atrial fibrillation and flutter and incorporated variables such as TAPSE and LAVI that are not consistently assessed in TEE examinations. None of these scores was specifically developed for patients with atrial flutter undergoing catheter ablation, a group in whom thrombus risk and clinical decision-making differ meaningfully. Our score uses only simple clinical and echocardiographic parameters available in any center and demonstrated moderate discriminatory capacity, outperforming CHA2DS2-VASc and yielding a positive NRI of 28.8%, particularly by reducing false-positive classifications. These findings suggest that the proposed score provides incremental value over existing models and may assist in identifying which patients with flutter truly benefit from pre-ablation TEE.
The proposed score only underwent internal validation, and additional performance metrics such as calibration assessment, Brier score, and cross-validated confidence intervals were not obtainable from the retrospective dataset. Therefore, the clinical applicability of this model should be interpreted cautiously until external validation is performed in independent cohorts.
LimitationsThis study has several limitations. First, its retrospective, single-center design limits causal inference and may introduce selection bias. The population consisted exclusively of patients referred for pre-ablation transesophageal echocardiography (TEE), which inherently selects individuals with higher clinical risk and may overestimate thrombus prevalence compared with unselected AFL populations. In addition, the inclusion of both typical and atypical atrial flutter should be acknowledged as a limitation. As detailed electrophysiological characterization and prior atrial ablation history were not systematically recorded in this retrospective cohort, subgroup analyses according to CTI dependency or prior left atrial ablation were not feasible. Given that left atrial flutter frequently occurs after atrial fibrillation ablation and may be associated with a more advanced atrial substrate, this heterogeneity may have influenced thrombus prevalence. Nonetheless, the study reflects a real-world population referred for flutter ablation, in whom pre-procedural thromboembolic risk assessment remains clinically relevant regardless of flutter mechanism.
Detailed characterization of certain high-risk conditions – such as cardiac amyloidosis, rheumatic heart disease, hypertrophic cardiomyopathy, and the presence of mechanical prosthetic valves – was not available due to incomplete documentation in the retrospective dataset, which limited our ability to analyze their association with LAA thrombus. Data on adherence to direct oral anticoagulants (DOACs) were unavailable, precluding a detailed assessment of anticoagulation quality. Misclassification between dense spontaneous echo contrast (“sludge”) and definite thrombus cannot be excluded, as image interpretation relied on TEE reports rather than blinded re-evaluation of stored images. In addition, interobserver variability was not assessed, which may affect reproducibility of echocardiographic findings. Finally, as the study was conducted in a single tertiary center within the Brazilian public health system, generalization of the results to other populations and healthcare contexts should be made with caution.
ConclusionIn summary, our study revealed an unexpectedly high prevalence of LAA thrombi (18.8%), markedly greater than that reported in previous international studies. This finding may reflect challenges specific to the Brazilian public healthcare system, such as suboptimal anticoagulation control, limited access to specialized care, and socioeconomic barriers affecting adherence to therapy. Additionally, we identified significant associations between LAA thrombi and HF, previous stroke/AIT, male sex, lower GFR, LA enlargement, and older age. There was no significant difference between the class of anticoagulant administered, suggesting that the use of NOACs or warfarin alone does not determine a higher or lower occurrence of thrombus in the LAA. Based on the findings, we successfully developed a straightforward and practical clinical score to predict the presence of thrombus in TEE. The score demonstrated a moderate discriminative ability (AUC of 0.726) and provided a more balanced distribution between sensitivity and specificity compared to the CHA2DS2-VASc score.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Conflict of interestThe authors declare that there are no conflicts of interest related to the content of this manuscript.



