



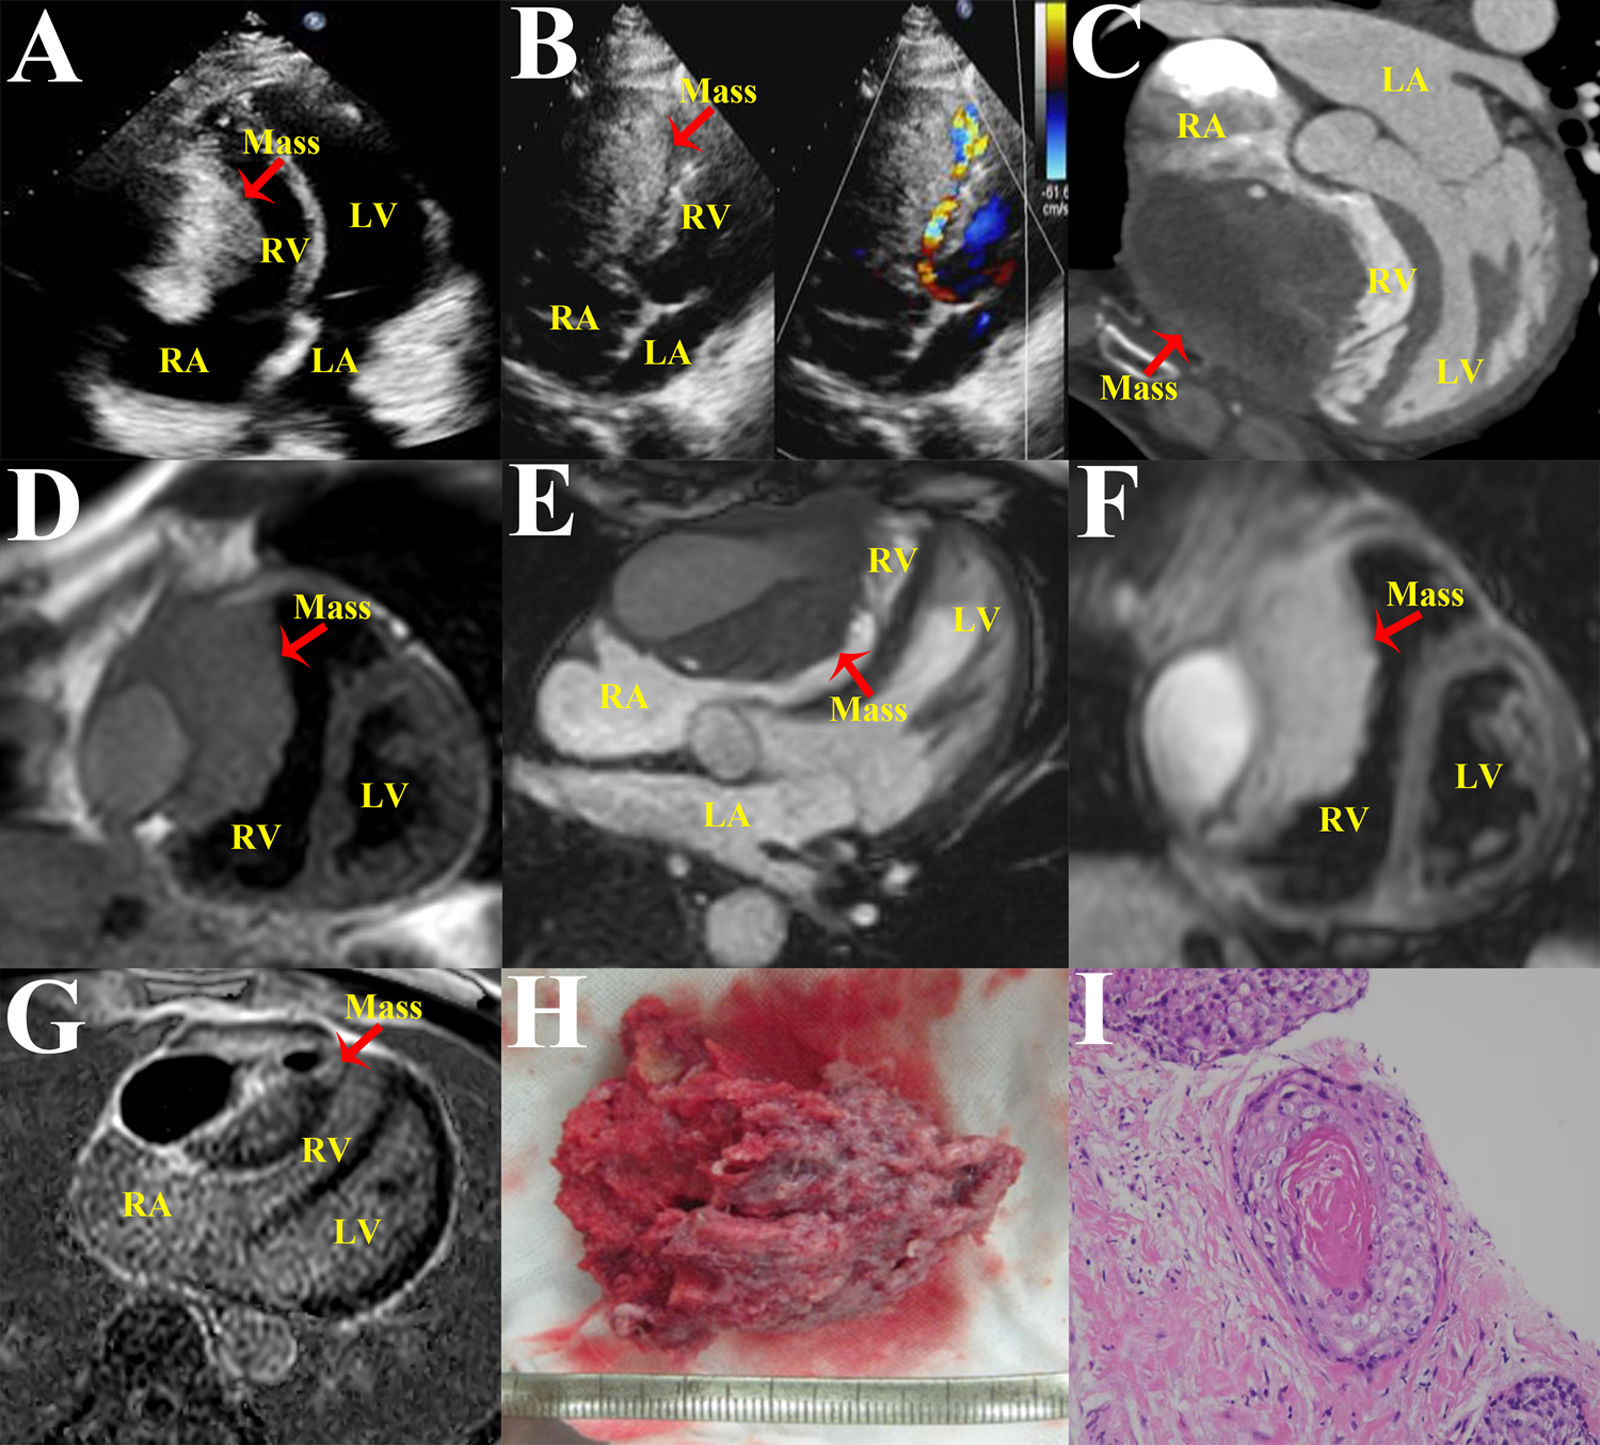
A 41-year-old man presented with intermittent chest tightness and shortness of breath over the past six months. He had no other significant medical history. Transthoracic echocardiography (TTE) revealed a mixed hypoechoic mass measuring 8.1 cm×5.4 cm×5.8 cm, compressing the right ventricle (RV) (Figure 1A). Color Doppler imaging showed blood flow signals within the mass (Figure 1B). Cardiac-enhanced CT revealed a large mass with cystic changes and necrosis that invaded the pericardium and compressed the right ventricle, causing a crescent-shaped deformity (Figure 1C). Cardiac magnetic resonance (CMR) revealed an infiltrative mass that appeared isointense to slightly hyperintense on black-blood imaging (Figure 1D), moderately hyperintense on bright-blood imaging (Figure 1E), markedly hyperintense on T2-weighted short tau inversion recovery imaging (Figure 1F), and showed heterogeneous enhancement with a necrotic core on delayed gadolinium enhancement (Figure 1G).

(A) Transthoracic echocardiography reveals a mixed hypoechoic mass measuring 8.1 cm×5.4 cm×5.8 cm compressing the RV. (B) Color Doppler flow imaging shows the blood flow signal within the mass. (C) Contrast-enhanced cardiac CT reveals a giant mass with cystic changes and necrosis, invading the pericardium and compressing the RV with crescent-shaped alteration. (D–G) Cardiac magnetic resonance shows an infiltrative mass with isointense and slightly hyperintense on black-blood imaging (D), intermediate hyperintense on bright-blood imaging (E), significant hyperintensity on T2-weighted short tau inversion recovery imaging (F) and heterogeneous enhancement and necrotic core on delayed gadolinium enhancement (G). (H and I) The gross and histopathological analysis confirm that tumor is a well-differentiated squamous cell carcinoma. LA: left atrium; LV: left ventricle; RA: right atrium; RV: right ventricle.
Based on these findings, a malignant tumor in the right ventricle was strongly suspected. Subsequent laboratory tests showed that cytokeratin 19 fragment 21-1 (CYFRA 21-1) was elevated at 5.99 ng/ml (normal <3.3 ng/ml), and squamous cell carcinoma-associated antigen was elevated at 28.18 ng/ml (normal <2.7 ng/ml). The gross and histopathological analyses confirmed that the tumor was a well-differentiated squamous cell carcinoma (SCC) (Figure 1H and I). However, despite undergoing comprehensive screening and assessment, including positron emission tomography/computed tomography (PET-CT), the primary origin of the tumor remained unknown. The final diagnosis was cardiac metastatic squamous cell carcinoma of unknown origin.
Programmed cell death ligand 1 (PD-L1) was detected by immunohistochemistry, and postoperative chemotherapy was administered in combination with an immune checkpoint inhibitor. After one year of follow-up, the patient remained well with no signs of tumor recurrence.
Squamous cell carcinoma of unknown primary origin refers to any SCC in which the primary tumor site cannot be identified despite a guideline-directed evaluation.1 Squamous cell carcinoma of unknown primary origin with cardiac involvement is extremely rare. Previous literature has documented only a few cases of squamous cell carcinoma of unknown primary origin metastasizing to the heart, and most of these patients had a poor prognosis.2 The mechanism underlying cardiac metastasis remains poorly understood. The pericardium, myocardium, epicardium, and endocardium are affected in decreasing order of frequency. Accurate and timely diagnosis and treatment remain challenging.3 Multimodality imaging using CMR, contrast-enhanced CT, and TTE plays a significant role in diagnosis and treatment.4 TTE can provide detailed information about the mass, including its morphology, size, location, and mobility. CMR can be used to better characterize the mass and distinguish between fat, fluid, and blood-related components.5 The patient's condition and expected prognosis should be carefully considered when determining treatment options for cardiac metastatic SCC, including surgical procedures. Additionally, postoperative guided by immunohistochemical findings can improve survival rates.
Ethical approvalThe Institutional Review Board of Wuhan Aisa Heart Hospital approved this study and the patient's informed consent was waived (IRB number: SOP-LLWYH-025-03-R1).
FundingThis work was funded by the Wuhan Clinical Medical Research Center for Cardiovascular Imaging (CMRC202307).
Conflicts of interestThe authors have no conflicts of interest to declare.



