



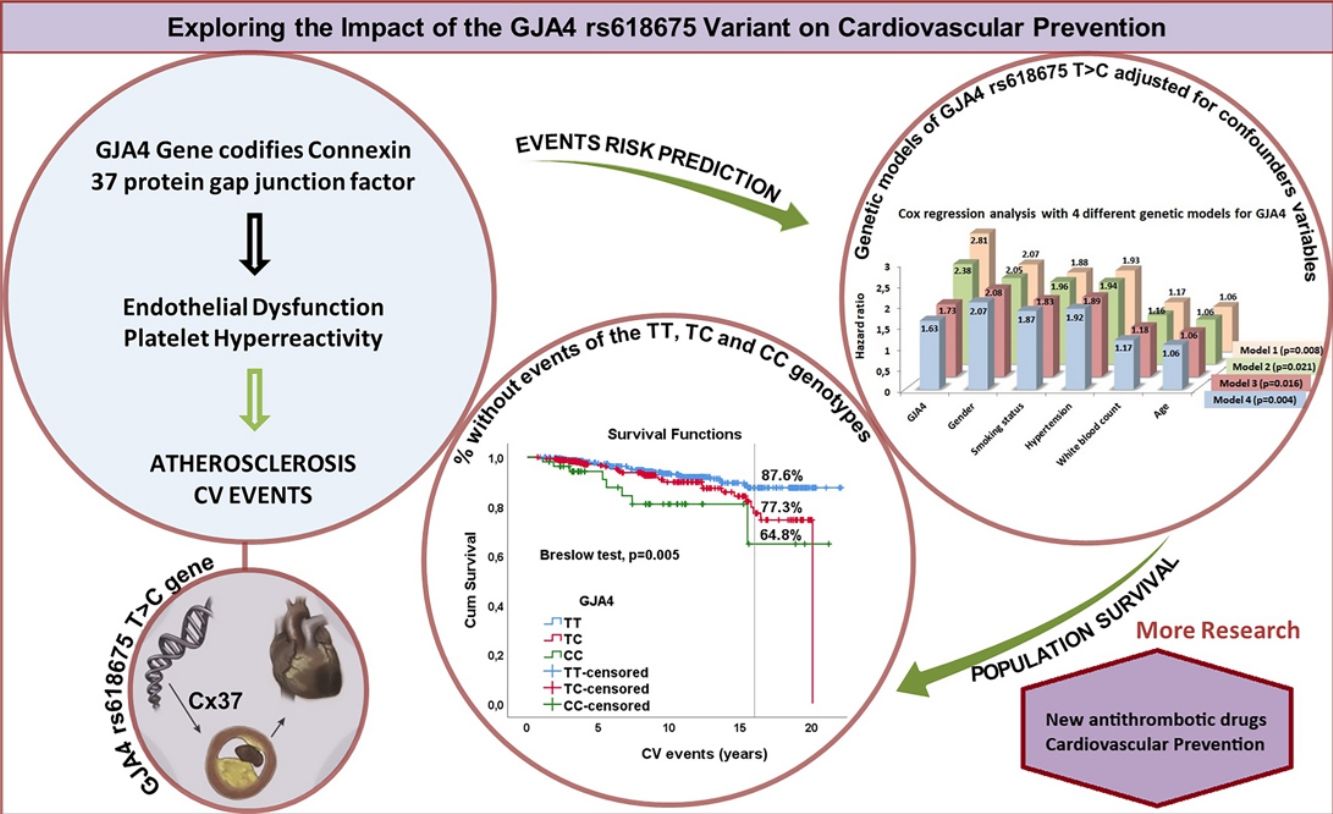
The gap junction alpha-4 (GJA4) gene, which encodes connexin37, regulates endothelial function and influences inflammation, platelet adhesion, and thrombus formation in vascular endothelial cells, which may favour atherosclerosis and cardiovascular (CV) events. The main objective was to assess whether the GJA4 rs618675 T>C variant is a risk factor for the onset of CV events in an asymptomatic Portuguese population.
MethodsOne thousand four hundred twenty-one individuals without CV disease (52.2±8.3 years, 73.6% male) were followed up during a mean of 7.3±6.0 years, and CV events were recorded. GJA4 rs618675 T>C was genotyped by real-time PCR (TaqMan), and four genetic models were created. We analyzed traditional, biochemical and clinical risk factors. We performed bivariate analysis and adjusted logistic regression with respective OR. Kaplan–Meier estimated event-free survival and Cox regression, adjusted for confounding, evaluated the association between four genetic models and CV events (HR).
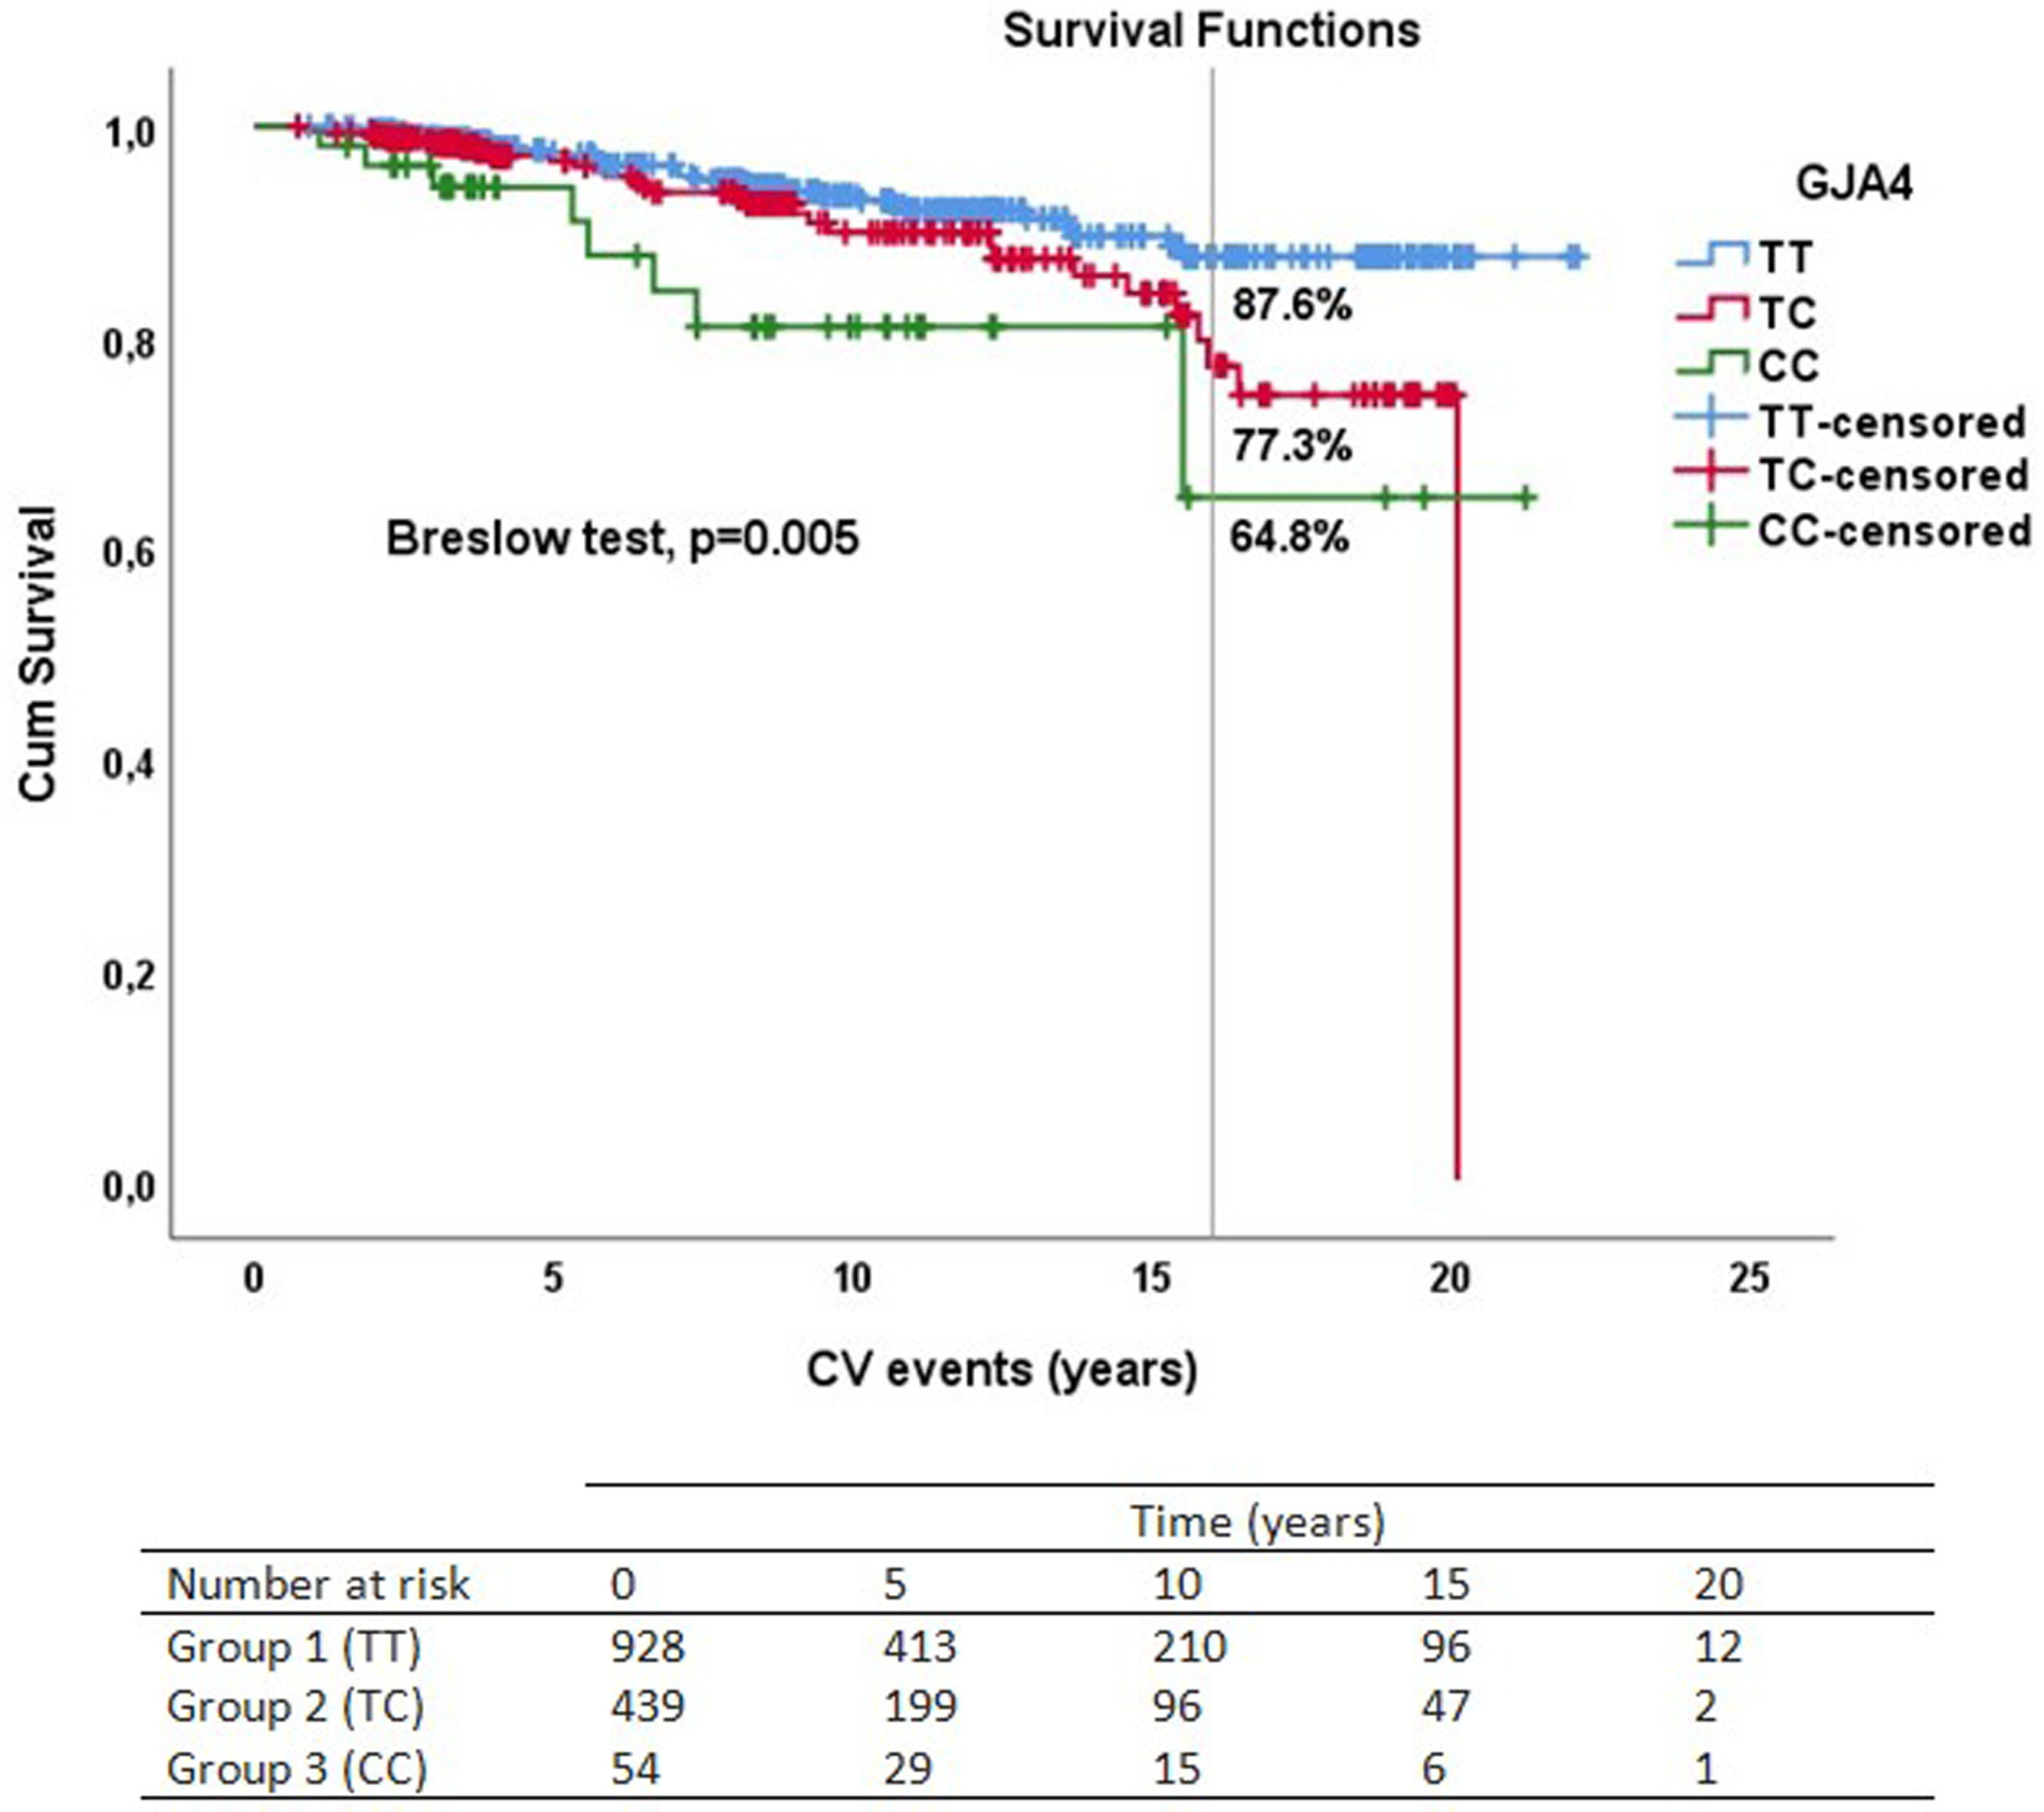
ResultsWild TT genotype, TC, and CC were 50.6%, 39.2%, and 10.1% in the CV events group and 66.2%, 30.4% and 3.4% in the non-events group (p=0.001). After logistic regression, the codominant model (CCvsTT and CTvsTT) showed an OR of 3.9 (p=0.002). Kaplan–Meier showed 87.6% event-free time for TT and 64.8% for CC (p=0.005). Adjusted Cox regression identified the codominant model as the best predictor (HR=2.8; p=0.008), together with male gender (HR=2.1; p=0.020), age (HR=1.1; p=0.001), hypertension (HR=1.9; p=0.014), smoking (HR=1.9; p=0.010), and leukocytosis (HR=1.2; p=0.003).
ConclusionWe have demonstrated that the CC variant of GJA4 is significantly associated with CV events. Further investigations into this biomarker may improve CV risk prediction, leading to better primary prevention.
O gene GJA4 codifica a proteína das junções comunicantes alfa-4 (Conexina37) e regula a função endotelial, influenciando a inflamação, adesão plaquetária e formação de trombos nas células endoteliais vasculares, favorecendo a ocorrência de eventos cardiovasculares (CV). Este estudo procurou avaliar a variante GJA4 rs618675 T>C como fator de risco para o aparecimento de eventos CV numa população portuguesa assintomática.
Métodos1421 indivíduos sem doença cardiovascular (52,2±8,3 anos,73,6% homens) foram seguidos durante 7,3±6,0 anos e os eventos CV registados. GJA4 rs618675 T>C foi genotipado por PCR em tempo real (TaqMan) em quatro modelos genéticos. Foram analisados os fatores de risco tradicionais, bioquímicos e clínicos. Foi realizada uma análise bivariada e regressão logística ajustada. Kaplan-Meier estimou o tempo sem eventos, a regressão de Cox avaliou a associação entre 4 modelos genéticos e os eventos CV.
ResultadosO genótipo selvagem TT, TC e o mutante CC apresentaram, respetivamente, 50,6%, 39,2% e 10,1% no grupo com eventos e 66,2%, 30,4% e 3,4% no grupo sem eventos (p=0,001). Após regressão logística, o modelo codominante (CCvsTT e CTvsTT) apresentou um OR de 3,9 (p=0,002). Kaplan-Meier mostrou 87,6% melhor probabilidade de ausência de eventos para TT e 64,8% para CC (p=0,005). A regressão de Cox mostrou que o melhor modelo foi o codominante (HR=2,8; p=0,008), juntamente com género masculino (HR=2,1; p=0,020), idade (HR=1,1; p=0,001), hipertensão (HR=1,9; p=0,014), tabagismo (HR=1,9; p=0,010) e leucocitose (HR=1,2; p=0,003).
ConclusãoA variante CC do gene GJA4 está significativamente associada a eventos cardiovasculares. Investigação adicional sobre este biomarcador pode melhorar a previsão do risco CV, permitindo uma melhor prevenção primária.

The gap junction alpha-4 (GJA4) gene, which encodes connexin37 (Cx37), belongs to the connexin family. Full-length connexins (Cxs) oligomerise and create channel structures that connect the cytosol of adjacent cells (gap junctions) or the cytosol with the extracellular zone (hemichannels).1 These channels allow the transfer of ions and small molecules, facilitating rapid, efficient communication between cells.2 Cxs proteins play essential roles in vascular cells, ranging from electrical coupling to vascular remodelling, angiogenesis, and vascular permeability.3 Cx37 is a member of the connexin family of proteins and is expressed in endothelial cells, macrophages, and platelets, protecting against atherosclerosis by controlling monocyte adhesion and having a growth-suppressive effect on endothelial cells. Cx37 is essential for endothelial health and helps regulate the inflammatory processes involved in atherosclerosis. Additionally, it maintains the stability of atherosclerotic plaques, preventing their vulnerability.4 Platelets also express GJA4 and Cx37, which are required to form a stable and effective clot when a vascular injury occurs.5 Inhibition of Cx37 function in platelets is controversial, but studies show that it reduces platelet aggregation and thrombus formation in mice, highlighting its critical role in these processes.6,7 Some GJA4 polymorphisms that alter cell adhesion and monocyte function can influence the risk of conditions such as atherosclerosis, coronary artery disease, and myocardial infarction. The GJA4 rs618675 T>C single-nucleotide polymorphism (SNP) has been previously identified in the Framingham Offspring Cohort as being significantly associated with cardiovascular (CV) events (HR=1.73; 95% CI 1.01–2.97; p=0.045).8,9 Although this variant lies in a non-coding intronic region and does not alter the Cx37 protein sequence, its association with CV outcomes may reflect linkage disequilibrium (LD) with a nearby functional missense variant or another regulatory mechanism affecting GJA4 expression and transcription. Given the biological plausibility of these mechanisms and the robust epidemiological association observed in the Framingham Offspring Study, we aimed to replicate and validate the rs618675 variant in our cohort to investigate further its potential contribution to cardiovascular risk in asymptomatic individuals from Madeira Island.
ObjectiveThis work aimed to investigate whether the GJA4 rs618675 T>C variant is a risk factor for the development of CV events in an asymptomatic Portuguese population without apparent CV disease.
MethodsStudy population and data collectionA total of 1421 individuals without apparent CVD, randomly selected from the electoral rolls of the Madeira Archipelago, were included in this study. They were admitted and prospectively enrolled in the research center dataset, SESARAM EPERAM, during a mean follow-up of 7.3±6.0 years. Participants were enrolled between 2000 and 2019. Inclusion/exclusion criteria were used, and asymptomatic individuals aged 35–65 years, without established cardiovascular disease were enrolled. A specialist cardiologist performed a complete clinical examination, including an electrocardiogram, and, when necessary, stress testing or echocardiography, confirming the absence of clinical or functional evidence of cardiovascular disease. Each participant was questioned about their demographic and traditional risk factors such as age, gender, smoking and alcohol habits, diabetes mellitus, dyslipidemia, physical inactivity and arterial hypertension, as previously defined.10 All laboratory analyses (total, LDL, HDL, non-HDL cholesterol, fasting glucose, apolipoprotein B (Apo B), lipoprotein(a), homocysteine, high sensitivity C-reactive protein (hsCRP), fibrinogen, leukocytes count and hamoglobin) were performed in the Clinical Pathology Laboratory of the Central Hospital, with quality accreditation, based on the Agencia de Calidad Sanitaria de Andalucía (ACSA) Model (international version).
A written informed consent was obtained from each participant at the time of enrollment. Approval from the Ethics Committee and from SESARAM was obtained before the start of the study under protocol number 50/2012.
Follow-up and cardiovascular outcomesFollow-up was performed from the date of admission until the occurrence of the first registered CV event. We used outpatient visits, telephone interviews, and hospitalization records to gather follow-up data.
Cardiovascular (CV) events were defined as clinical outcomes resulting from the occurrence or progression of cardiovascular disease. Major or primary events included nonfatal myocardial infarction, unstable angina, nonfatal stroke, and cardiovascular death, consistent with the conventional composite endpoint of major adverse cardiovascular events (MACE). Secondary events were considered in situations requiring hospitalization, such as coronary revascularisation procedures (percutaneous coronary intervention or coronary artery bypass grafting), hospitalization due to heart failure, transient ischemic attack (TIA), or peripheral arterial disease (PAD).11 Two cardiologists independently reviewed all prospective and potential outcomes.
Myocardial infarction (MI) was defined as acute myocardial injury detected by abnormal cardiac biomarkers (specifically, a rise and/or fall of cardiac troponin values with at least one value above the 99th percentile upper reference limit) in the presence of evidence of acute myocardial ischemia, indicated by at least one of the following: symptoms of ischemia (such as typical chest pain); new ischemic ECG changes; development of pathological Q waves; imaging evidence of new loss of viable myocardium or new regional wall motion abnormality consistent with ischemia; or identification of a coronary thrombus by angiography or autopsy.12
Unstable angina (UA) is characterized by myocardial ischemia at rest or with minimal exertion, but without evidence of acute myocardial injury – that is, cardiac troponin concentrations remain within the normal range. It typically presents as prolonged (usually >20 minutes) chest pain at rest, new-onset angina of at least CCS class III severity, or crescendo angina (previously stable angina that has become distinctly more frequent, severe, or prolonged). Because high-sensitivity cardiac troponin assays now detect even small amounts of myocardial injury, many cases that were formerly diagnosed as unstable angina are now classified as non-ST-segment elevation myocardial infarction (NSTEMI). Consequently, UA has become increasingly uncommon in current clinical practice.13
Coronary vascular revascularization (CR) is established as a percutaneous or surgical intervention aimed at re-establishing adequate perfusion to ischemic tissue by reopening or bypassing an obstructed vessel. Percutaneous coronary intervention (PCI) includes balloon angioplasty with or without stent implantation or atherectomy. Coronary artery bypass grafting (CABG) consists of the creation of a graft to bypass blocked coronary arteries.14
Ischemic stroke (IS) was defined as a neurological deficit resulting from occlusion of a cerebral artery (accounting for approximately 85% of all stroke cases). Transient ischemic attack (TIA) was defined as a transient episode of neurological dysfunction caused by focal brain, spinal cord, or retinal ischemia, without acute infarction, typically resolving within 24 hours.15
Cardiovascular mortality in this study was defined as death resulting from an atherosclerotic cardiovascular cause, such as acute myocardial infarction (AMI), sudden cardiac death, heart failure or cardiogenic shock, ischemic stroke, cardiovascular procedures or their complications (e.g., during or after PCI or CABG), or peripheral arterial disease leading to death (e.g., due to limb ischemia).16 For cardiovascular mortality, the criteria used were based on the International Classification of Diseases, 10th Revision (ICD-10) codes I21, I25, I25.9, I46.1, and I50. For ischemic stroke mortality, the Portuguese ICD-10 codes I63, I64, and I69 were adopted. In patients with multiple events, only the time of the first event was used for further analyses.
Genetic analysisDNA was extracted from the peripheral blood leukocytes using a standard salting-out method. A TaqMan allelic discrimination assay for genotyping GJA4 rs618675 T>C polymorphism was performed on a 7300 real-time PCR System using labelled probes and primers pre-established by the supplier (TaqMan, Applied Biosystems). Genotypes were determined without prior knowledge of the individual's clinical data. Quality control of the genotyping technique was maintained by including one non-template control (NTC) on each 96-well plate and a blind duplicate, accounting for 20% of all samples.
Statistical analysisData are expressed as frequencies and percentages, or as means and standard deviations, except for laboratory analyses, which are presented as medians (minimum–maximum). Gene counts consider allelic and genotypic frequencies. Groups with CV events and non-events are compared using the Chi-square test. Hardy–Weinberg equilibrium was assessed using observed and expected genotypic frequencies, verified by Pearson's Chi-square test. The independent Student's t test was used to compare means for continuous variables; a nonparametric test (Mann–Whitney) was used when variables were not normally distributed.
For data analysis, we created four genetic models: model 1 – GJA4 codominant model (CC vs. TT and CT vs. TT); model 2 – GJA4 recessive model (CC compared with TT+TC); model 3 – GJA4 dominant model (TC+CC compared with TT) and model 4 – GJA4 additive model (TT-0; TC-1; CC-2). To report the strength of the association between GJA4 genetic models and the occurrence of an event, we used bivariate and multivariate logistic regression analysis with the respective odds ratios (OR). We used the Kaplan–Meier estimator for event-free analysis, which estimates the survival function from the start date to the event time. To investigate which variables were significantly and independently associated with CV events, we performed four multivariate Cox regression analyses (adjusted for all significant variables from the bivariate analysis), each with hazard ratios (HRs) and p-values for the respective genetic models. The HR measured the effect size of the predictor variables, which were significantly and independently associated with CV events. Finally, we presented a graph comparing the effect sizes (HRs) and significant variables across all genetic models for the risk of CV events. All analyses were made with SPSS software (version 25.0, SPSS Inc.). At p<0.05, significance was considered.
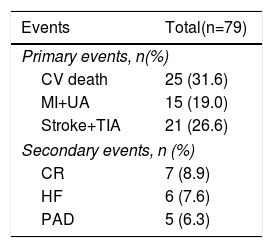
ResultsComparison analysis (bivariate analysis)Our study population comprised 73.6% males with a mean age of 52.2±8.3 years. In the analysis window, CV events occurred in 79 (5.6%) patients, shown in Table 1.
Description of the CV events.
| Events | Total(n=79) |
|---|---|
| Primary events, n(%) | |
| CV death | 25 (31.6) |
| MI+UA | 15 (19.0) |
| Stroke+TIA | 21 (26.6) |
| Secondary events, n (%) | |
| CR | 7 (8.9) |
| HF | 6 (7.6) |
| PAD | 5 (6.3) |
CR: coronary revascularisation; CV: cardiovascular; HF: heart failure; MI: myocardial infarction; PAD: peripheral arterial disease; TIA: transient ischemic attack; UA: unstable angina.
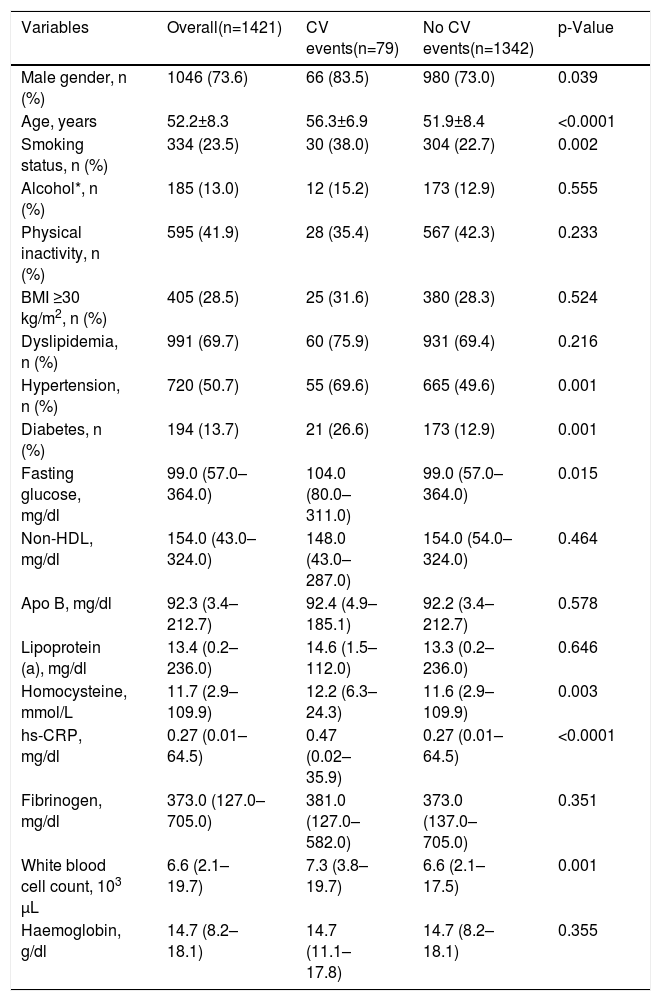
A comparison of the patients with CV events versus non-events, concerning their baseline variables (Table 2) showed a higher mean age (56.3±6.9 vs. 51.9±8.4 years; p<0.0001) as well as a higher frequency of the usual traditional risk factors, such as male gender (83.5% vs. 73.0%; p=0.039), smoking status (38.0% vs. 22.7%; p=0.002), hypertension (69.6% vs. 49.6%; p=0.001), diabetes (26.6% vs. 12.9%; p=0.001), fasting glucose levels (104.0 vs. 99.0 mg/dl; p=0.015); homocysteine levels (12.2 vs. 11.6 mmol/L; p=0.003), hsCRP (0.47 vs. 0.27 mg/dl; p<0.0001), and white blood cell count (7.3 vs. 6.6 103 μL; p=0.001).
Comparison of the baseline characteristics of the population.
| Variables | Overall(n=1421) | CV events(n=79) | No CV events(n=1342) | p-Value |
|---|---|---|---|---|
| Male gender, n (%) | 1046 (73.6) | 66 (83.5) | 980 (73.0) | 0.039 |
| Age, years | 52.2±8.3 | 56.3±6.9 | 51.9±8.4 | <0.0001 |
| Smoking status, n (%) | 334 (23.5) | 30 (38.0) | 304 (22.7) | 0.002 |
| Alcohol*, n (%) | 185 (13.0) | 12 (15.2) | 173 (12.9) | 0.555 |
| Physical inactivity, n (%) | 595 (41.9) | 28 (35.4) | 567 (42.3) | 0.233 |
| BMI ≥30 kg/m2, n (%) | 405 (28.5) | 25 (31.6) | 380 (28.3) | 0.524 |
| Dyslipidemia, n (%) | 991 (69.7) | 60 (75.9) | 931 (69.4) | 0.216 |
| Hypertension, n (%) | 720 (50.7) | 55 (69.6) | 665 (49.6) | 0.001 |
| Diabetes, n (%) | 194 (13.7) | 21 (26.6) | 173 (12.9) | 0.001 |
| Fasting glucose, mg/dl | 99.0 (57.0–364.0) | 104.0 (80.0–311.0) | 99.0 (57.0–364.0) | 0.015 |
| Non-HDL, mg/dl | 154.0 (43.0–324.0) | 148.0 (43.0–287.0) | 154.0 (54.0–324.0) | 0.464 |
| Apo B, mg/dl | 92.3 (3.4–212.7) | 92.4 (4.9–185.1) | 92.2 (3.4–212.7) | 0.578 |
| Lipoprotein (a), mg/dl | 13.4 (0.2–236.0) | 14.6 (1.5–112.0) | 13.3 (0.2–236.0) | 0.646 |
| Homocysteine, mmol/L | 11.7 (2.9–109.9) | 12.2 (6.3–24.3) | 11.6 (2.9–109.9) | 0.003 |
| hs-CRP, mg/dl | 0.27 (0.01–64.5) | 0.47 (0.02–35.9) | 0.27 (0.01–64.5) | <0.0001 |
| Fibrinogen, mg/dl | 373.0 (127.0–705.0) | 381.0 (127.0–582.0) | 373.0 (137.0–705.0) | 0.351 |
| White blood cell count, 103 μL | 6.6 (2.1–19.7) | 7.3 (3.8–19.7) | 6.6 (2.1–17.5) | 0.001 |
| Haemoglobin, g/dl | 14.7 (8.2–18.1) | 14.7 (11.1–17.8) | 14.7 (8.2–18.1) | 0.355 |
Apo B: apolipoprotein B; BMI: body mass index; CV: cardiovascular; *>300 g/week; HDL: high-density lipoprotein; hsCRP: high sensitivity C reactive protein; statistically significant for p<0.05.
According to the Hardy–Weinberg equilibrium, the genotype distribution between the CV events group (χ2=0.295) and the non-event group (χ2=0.011) was not significantly different.
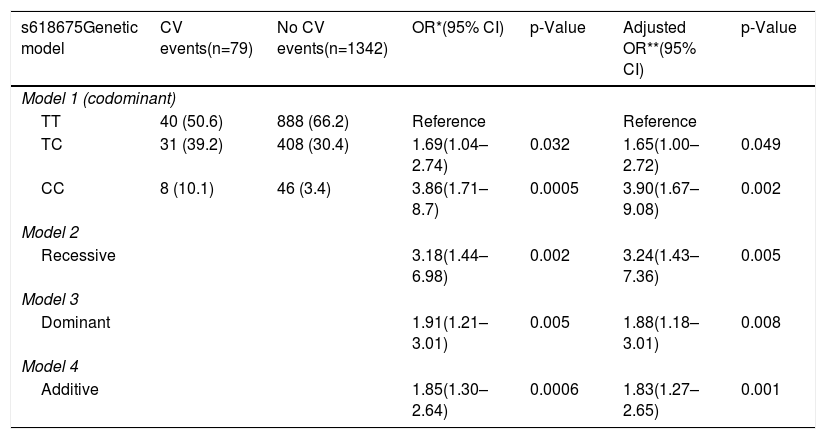
The frequencies of the wild TT, heterozygous TC, and mutant CC genotypes of the GJA4 rs618675 T>C were, respectively, 50.6%, 39.2% and 10.1% in the CV events group and 66.2%, 30.4% and 3.4% in the non-events group (p=0.001).
In bivariate analysis, there was also significant differences in genotypes between the two studied groups, with ORs of 1.69 (p=0.032) for the heterozygous genotype and 3.86 (p=0.0005) for the mutant CC genotype (Table 3).
Association between GJA4 rs618675 T>C and CV events occurrence (bivariate and multivariate logistic regression).
| s618675Genetic model | CV events(n=79) | No CV events(n=1342) | OR*(95% CI) | p-Value | Adjusted OR**(95% CI) | p-Value |
|---|---|---|---|---|---|---|
| Model 1 (codominant) | ||||||
| TT | 40 (50.6) | 888 (66.2) | Reference | Reference | ||
| TC | 31 (39.2) | 408 (30.4) | 1.69(1.04–2.74) | 0.032 | 1.65(1.00–2.72) | 0.049 |
| CC | 8 (10.1) | 46 (3.4) | 3.86(1.71–8.7) | 0.0005 | 3.90(1.67–9.08) | 0.002 |
| Model 2 | ||||||
| Recessive | 3.18(1.44–6.98) | 0.002 | 3.24(1.43–7.36) | 0.005 | ||
| Model 3 | ||||||
| Dominant | 1.91(1.21–3.01) | 0.005 | 1.88(1.18–3.01) | 0.008 | ||
| Model 4 | ||||||
| Additive | 1.85(1.30–2.64) | 0.0006 | 1.83(1.27–2.65) | 0.001 | ||
When we used multivariate logistic regression, adjusted for all co-variables statistically significant in bivariate analysis, the significance remained at OR=1.65 (p=0.049) for the TC genotype and OR=3.90 (p=0.002) for the CC genotype. For the other genetic models, the adjusted ORs were 3.24 (p=0.005) for the recessive model, 1.88 (p=0.008) for the dominant model, and 1.83 (p=0.001) for the additive model (Table 3).
Survival analysisKaplan–Meier estimate analysisWe used the Kaplan–Meier method to compare the wild (TT), heterozygous (TC), and mutant homozygous (CC) genotypes to estimate subjects’ probability of remaining event-free over time.
The CC genotype was associated with worse prognosis throughout the follow-up period (p=0.005). Specifically, at 16 years of follow-up, CC showed a lower event-free rate of 64.8% compared with wild-type (87.6%) and heterozygous (77.3%) (Figure 1).
Multivariate Cox regression analysis
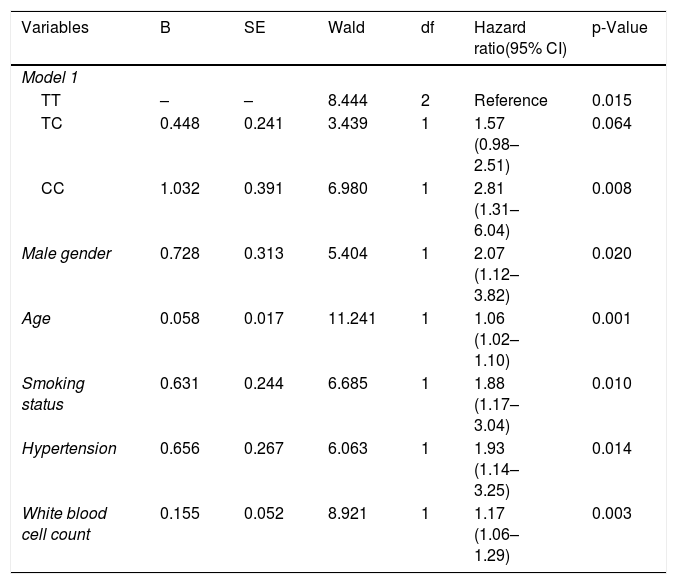
Considering the time to the first event, Cox regression analysis estimates the survival function for all GJA4 genetic models, adjusting for significant variables (gender, age, diabetes, hypertension, smoking status, homocysteine, hs-CRP, and white blood cell count). We considered model 1 (codominant) the best for comparison as it presented the strongest association (HR) with the onset of CV events.
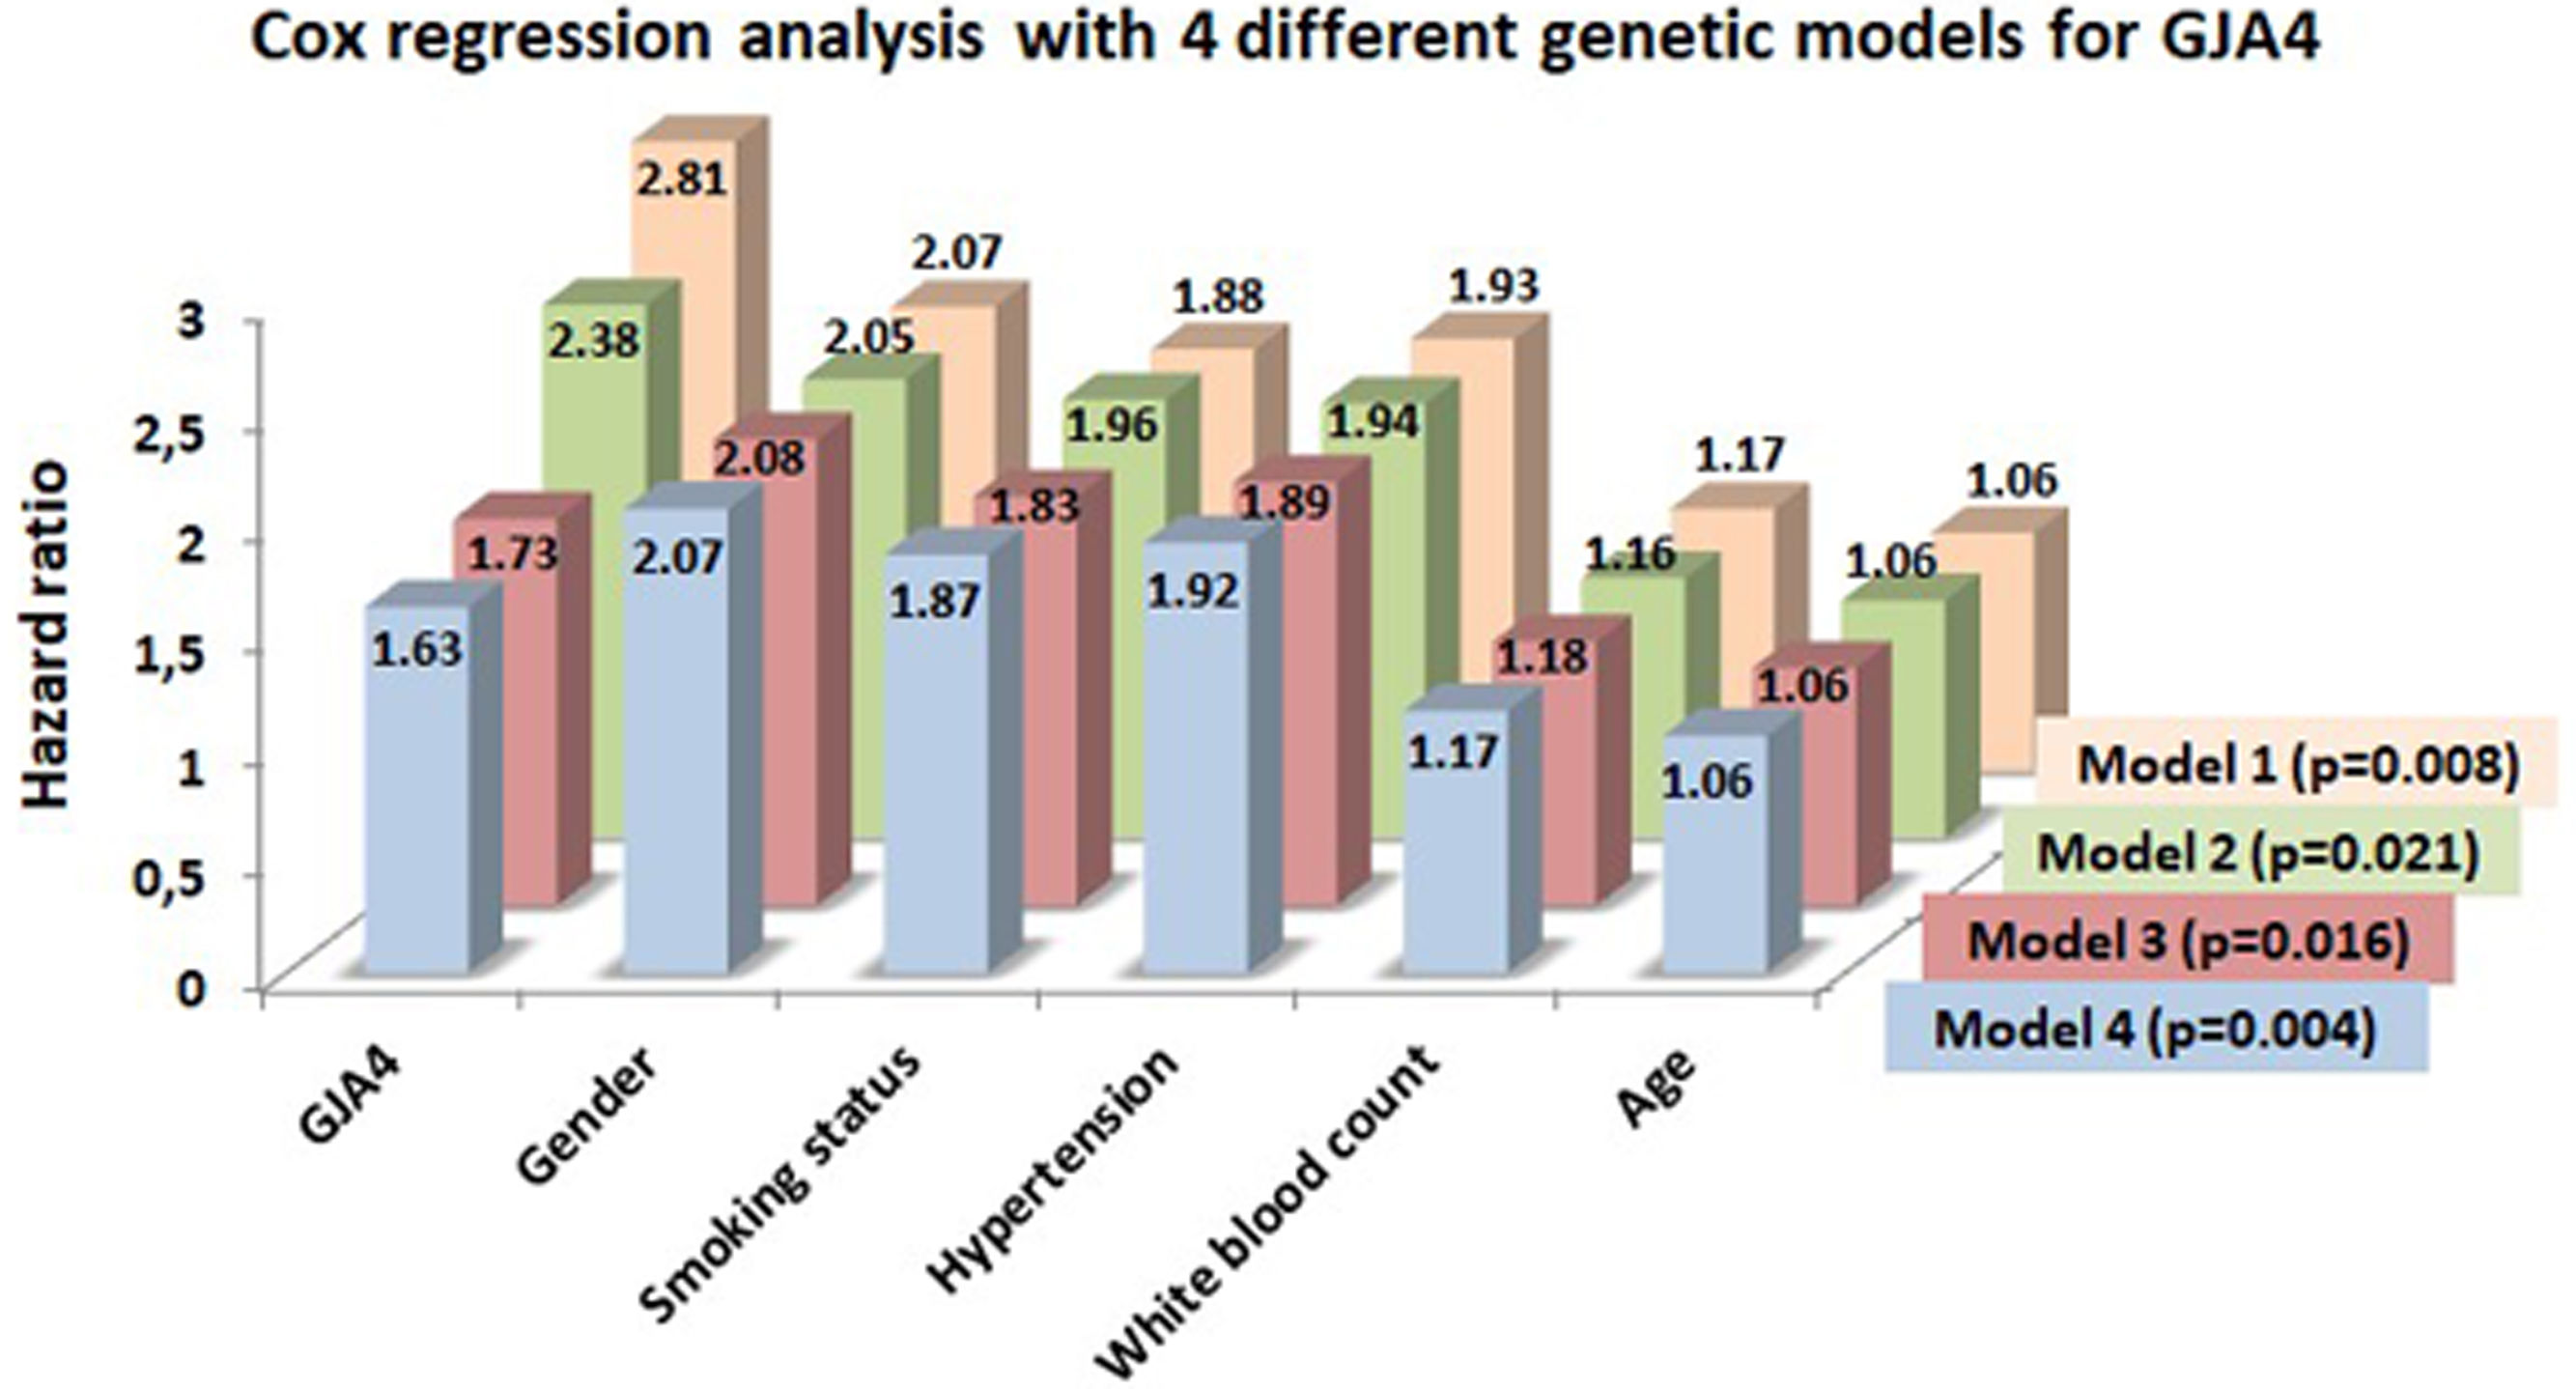
Results show that, in this analysis, the risk CC genotype presented an adjusted HR of 2.81 (p=0.008) and the TC heterozygous had an HR of 1.57 (p=0.064), together with the male gender (HR=2.07; p=0.020), age (HR=1.06; p=0.001), smoking status (HR=1.88; p=0.010), hypertension (HR=1.93; p=0.014), and white blood cell count (HR=1.17; p=0.003) (Table 4).
Cox proportional hazard analysis for assessing the relation between GJA4 rs618675 T>C and CV events.
| Variables | B | SE | Wald | df | Hazard ratio(95% CI) | p-Value |
|---|---|---|---|---|---|---|
| Model 1 | ||||||
| TT | – | – | 8.444 | 2 | Reference | 0.015 |
| TC | 0.448 | 0.241 | 3.439 | 1 | 1.57 (0.98–2.51) | 0.064 |
| CC | 1.032 | 0.391 | 6.980 | 1 | 2.81 (1.31–6.04) | 0.008 |
| Male gender | 0.728 | 0.313 | 5.404 | 1 | 2.07 (1.12–3.82) | 0.020 |
| Age | 0.058 | 0.017 | 11.241 | 1 | 1.06 (1.02–1.10) | 0.001 |
| Smoking status | 0.631 | 0.244 | 6.685 | 1 | 1.88 (1.17–3.04) | 0.010 |
| Hypertension | 0.656 | 0.267 | 6.063 | 1 | 1.93 (1.14–3.25) | 0.014 |
| White blood cell count | 0.155 | 0.052 | 8.921 | 1 | 1.17 (1.06–1.29) | 0.003 |
B: beta coefficient; CI: confidence interval; CV: cardiovascular; df: degrees of freedom; SE: standard error; variables excluded from the equation: diabetes; homocysteine; hs-CRP. Statistically significant for p<0.05.
Subsequently, we performed three additional Cox regression analyses using the remaining genetic models, each adjusted for its respective confounder variables. We compared the effect sizes (HRs) of all genetic models on the risk of CV events (Figure 2). This graph shows that all genetic models are significant predictors; however, model 1 (CC vs. TT) has the largest magnitude of association for predicting CV events.

The effect size of all CV events risk predictors. Model 1 – GJA4 codominant model (CC vs. TT) (p=0.008); Model 2 – GJA4 recessive model (CC vs. TT+TC) (p=0.021); Model 3 – GJA4 dominant model (TC+CC vs. TT) (p=0.016); Model 4 – GJA4 additive model (TT – 0; TC – 1; CC – 2) (p=0.004). Variables excluded from the equation: diabetes, homocysteine, and hs-CRP. Statistically significant at p<0.05.
Coronary artery disease (CAD) is often clinically silent and may progress insidiously over many years before the onset of symptoms. Individuals with subclinical atherosclerosis frequently remain undiagnosed and may appear healthy until the occurrence of a major adverse cardiovascular event, including sudden cardiac death. Early identification of these high-risk individuals provides an opportunity for timely intervention aimed at preventing severe outcomes. Achieving more accurate risk stratification remains a major clinical challenge but could substantially reduce the incidence of myocardial infarction and cardiovascular mortality.17
Although cardiovascular disease (CVD) has a strong environmental component, a genetic predisposition also contributes significantly to its development. Genetic analysis can complement traditional risk assessment by identifying inherited susceptibility before clinical manifestations.18 Advances in sequencing technologies have markedly reduced costs, making such analyses more accessible. Incorporating genetic data into conventional risk models – alongside factors such as age, cholesterol, and blood pressure – can improve risk stratification, especially in asymptomatic individuals with subclinical atherosclerosis.19
As previously described, the GJA4 gene encodes connexin 37 (Cx37), a gap junction protein essential for intercellular communication in various tissues, including the heart and vascular endothelium. Cx37 plays a key role in endothelial function by modulating inflammatory responses, platelet adhesion, and thrombus formation. Polymorphisms within GJA4 have been associated with an increased risk of atherosclerosis and myocardial infarction. Such alterations may impair gap junction–mediated signaling in endothelial cells and platelets, promoting abnormal platelet aggregation and thrombus formation, thereby contributing to the development of coronary artery disease and ischemic stroke.20,21
Our longitudinal study, with comprehensive follow-up, investigated whether the GJA4 rs618675 T>C genetic variant is associated with the occurrence of cardiovascular events in an asymptomatic population without known coronary artery disease. Carriers of the CC genotype exhibited an adjusted odds ratio of 3.9, indicating approximately 3.9-fold higher odds (≈290% increase) of experiencing cardiovascular events compared with individuals with the TT genotype, after adjustment for other covariates. CC showed a lower event-free rate of 64.8% compared with CT (77.3%) or TT (87.6%) genotypes. Furthermore, the hazard ratio (HR) for cardiovascular event risk was 2.81 for the CC genotype relative to the wild-type TT genotype. These findings suggest that the GJA4 rs618675 CC genotype was associated with worse prognosis throughout the follow-up period.
The rs618675 variant is a non-coding tagging SNP located within the GJA4 locus and has been associated with increased atherosclerosis and a higher risk of cardiovascular events in several population-based studies. Although it does not alter the amino acid sequence of connexin 37 (Cx37), its association with cardiovascular outcomes was confirmed in the Framingham Offspring Cohort, where CC homozygotes demonstrated a 1.7-fold higher hazard of coronary events compared with TT carriers.8,9 This association is likely driven by linkage disequilibrium with the nearby functional missense variant GJA4 rs1764391 (C1019T, p.Pro319Ser) or by regulatory effects influencing GJA4 transcription or expression. However, the Framingham analysis was purely epidemiological and did not explore the functional consequences of rs618675. To date, no experimental evidence has demonstrated a direct regulatory role for this non-coding variant, although its position suggests a potential influence within a regulatory or enhancer element modulating GJA4 gene activity.
Our asymptomatic population was recently reclassified by SCORE2, which showed that, under the new scoring system, the low-to-moderate group lost population comprised only 24.7% of the overall sample. In comparison, the high- and very-high-risk categories accounted for 75.2% of the total population with a high probability of CV events.22 Adding the GJA4 rs617586 variant to SCORE2 could enhance cardiovascular risk prediction by capturing lifelong genetic susceptibility and vascular dysfunction not reflected by traditional factors.23,24 This may improve risk discrimination and reclassification, particularly among intermediate-risk individuals, enabling more personalized preventive strategies identifying those who would benefit most from lipid-lowering, anti-inflammatory, or lifestyle interventions. The effect is expected to be stronger when combined with other GJA4 polymorphisms at the same locus, a polygenic risk score or other markers like coronary calcium scoring.
Several studies,6,7,25 using different methodologies, investigated the Cx37 rs1764391 polymorphism C1019T. This proline-to-serine change is very close to GJA4 rs618675 at the same locus. They speculate that this amino-acid alteration affects the tertiary structure of the protein and, consequently, the regulation of its functionality, particularly concerning myoendothelial gap junction intercellular communication and platelet activation and thrombus function. The structure of the Cx37 protein can be affected or modulated by connexin polymorphisms, which impair the EC barrier and platelet reactivity, influencing the progression of atherosclerosis and CV events. Nevertheless, their findings have not yet been validated.
Understanding the predictors of arterial thrombosis and atherosclerosis development is critical and will aid in developing personalised medication to prevent and treat the complications of atherosclerosis and vascular injury. Also, significant effort is needed to create accurate risk-stratification tools based on clinical and traditional factors. However, genetic factors and the genetic and environmental influences on an individual's risk remain essential. With the emergence of advanced techniques for analysing human genetic profiles, researchers have moved away from genetic linkage analysis and a candidate gene approach to genome-wide association studies. They focus on studying glycoproteins, receptors expressed on platelet surfaces, and mutations that significantly impact platelet function. There is considerable interindividual variability in platelet responses to agonists and drugs, and the hyperreactivity phenotype appears to be heritable.26 The use of antiplatelet medications to prevent cardiovascular events in individuals without established atherosclerotic disease should be considered for primary prevention in exceptional cases, such as in people with a genetic predisposition to the formation of thrombi, as this tendency can anticipate fatal occlusive cardiovascular and cerebrovascular pathologies. However, the main challenge for future approaches will be individualised antithrombotic therapy, which involves agents targeting genetic defects to alter platelet function, thereby reducing the risk of bleeding and balancing safety with efficacy.
Strengths and limitationsAs far as we know, this is the first study in a Portuguese population to establish a correlation between a specific genetic polymorphism in the GJA4 gene encoding Connexin37 and cardiovascular events. The original sample is relevant: more than 1400 persons, and the mean follow-up exceeded seven years. Given that the survey was conducted at the island's only tertiary hospital, we had few opportunities for loss to follow-up. These results are relevant, demonstrating the importance of this polymorphism in the development of cardiovascular events.
Although the initial sample size was adequate, the number of patients with CV events was low, which reduced the accuracy and reliability of the results. Also, the participants were randomly selected, but we cannot assure they are representative of the entire Portuguese population in terms of gender, age, and geographic origin.
There is a need for multicentre studies with larger sample sizes from different regions and diverse ethnic and social backgrounds to confirm the present results.
ConclusionsMost cardiovascular prevention has focused on lipid and cholesterol-lowering therapies guided by LDL values. Antiplatelet therapy has traditionally been prescribed on the basis of estimated cardiovascular risk, without biomarkers to predict treatment response.
Our study demonstrated that the GJA4 rs618675 T>C polymorphism, expressed in platelets, is significantly associated with cardiovascular (CV) events in an asymptomatic population. If confirmed in larger cohorts, this easily and inexpensively genotyped variant could serve as a valuable biomarker for primary prevention, particularly among younger individuals with few traditional risk factors but a family history and a strong genetic predisposition for CV events. Further research into the functional modulation of the GJA4 gene, implicated in vascular inflammation and thrombosis, may offer new opportunities to reduce CV risk and develop novel antithrombotic therapies.
Ethical approvalEthics Committee of Funchal Hospital Centre approved the study under protocol number 50/2012.
Conflicts of interestNone declared.



