



Arguably, one of the advantages of a scientific editorial is to present the writer's opinion on a particular topic. Some subjects are more controversial than others. This is especially true for the work presented in this issue of the Portuguese Journal of Cardiology by Cunha et al.1 In their work, they address the comparative use of two cardiovascular risk scores: the comparison between the “old” SCORE2 risk calculator with the newer SCORE2 Diabetes.3 At the time this work was produced the Portuguese public family health system software was not equipped with SCORE2 Diabetes. We also believe that the same was true for the more recent SCORE24 and its counterpart for older people, SCORE2-OP.5
The same logic was used and a similar study was produced by another group in the Portuguese primary care setting; they advocated a software update and the benefits of SCORE2 versus SCORE.6 This demonstrates the active role of the family doctor community in Portugal, which has also been responsible for important epidemiological studies in the field of diabetes using the same publicly available software data.7,8
It is well known that many cardiovascular risk calculators exist; it is also widely accepted that no risk calculator is perfect – they are all approximations of the biological variation inherent in human biology. Moreover, they also reflect our understanding of the biological risk factors associated with chronic diseases such as diabetes. Through the analysis of epidemiological risk factors, used in risk factor calculators (starting with the famous Framingham Risk Score9,10), the importance of the “three riders of the apocalypse” (hypertension, diabetes mellitus and dyslipidemia) in any risk factor calculator was made clear. Risk calculators also lead us to understand the overwhelming materialized importance of smoking as far as cardiovascular risk is concerned. However, any physician understands that age is the most important cardiovascular risk factor – regardless of which risk calculators one is using. Therefore, it is possible to be clinically accurate without relying solely on mathematical assessments of a patient's cardiovascular risk. This is also true for other common-sense issues, such as taking family medical history, which requires careful listening skills. This is something that is very difficult to achieve in today's busy clinics where time is limited. Understandably, no cardiovascular risk calculator is perfect and the search for the Holy Grail of risk calculators is a never-ending story…
Another, often forgotten notion, is that cardiovascular risk calculators have regional and political contexts, inasmuch as some are intended for use in several continents, like the OMS/OPAS – HEARTS (WHO Cardiovascular Risk Charts),11 while others are regional such as the European SCORE calculators. Risk percentages from one particular risk calculator often do not correspond to those from others. Even the SCORE charts are adapted to several distinct geographical regions within Europe, each with different levels of risk exposure.
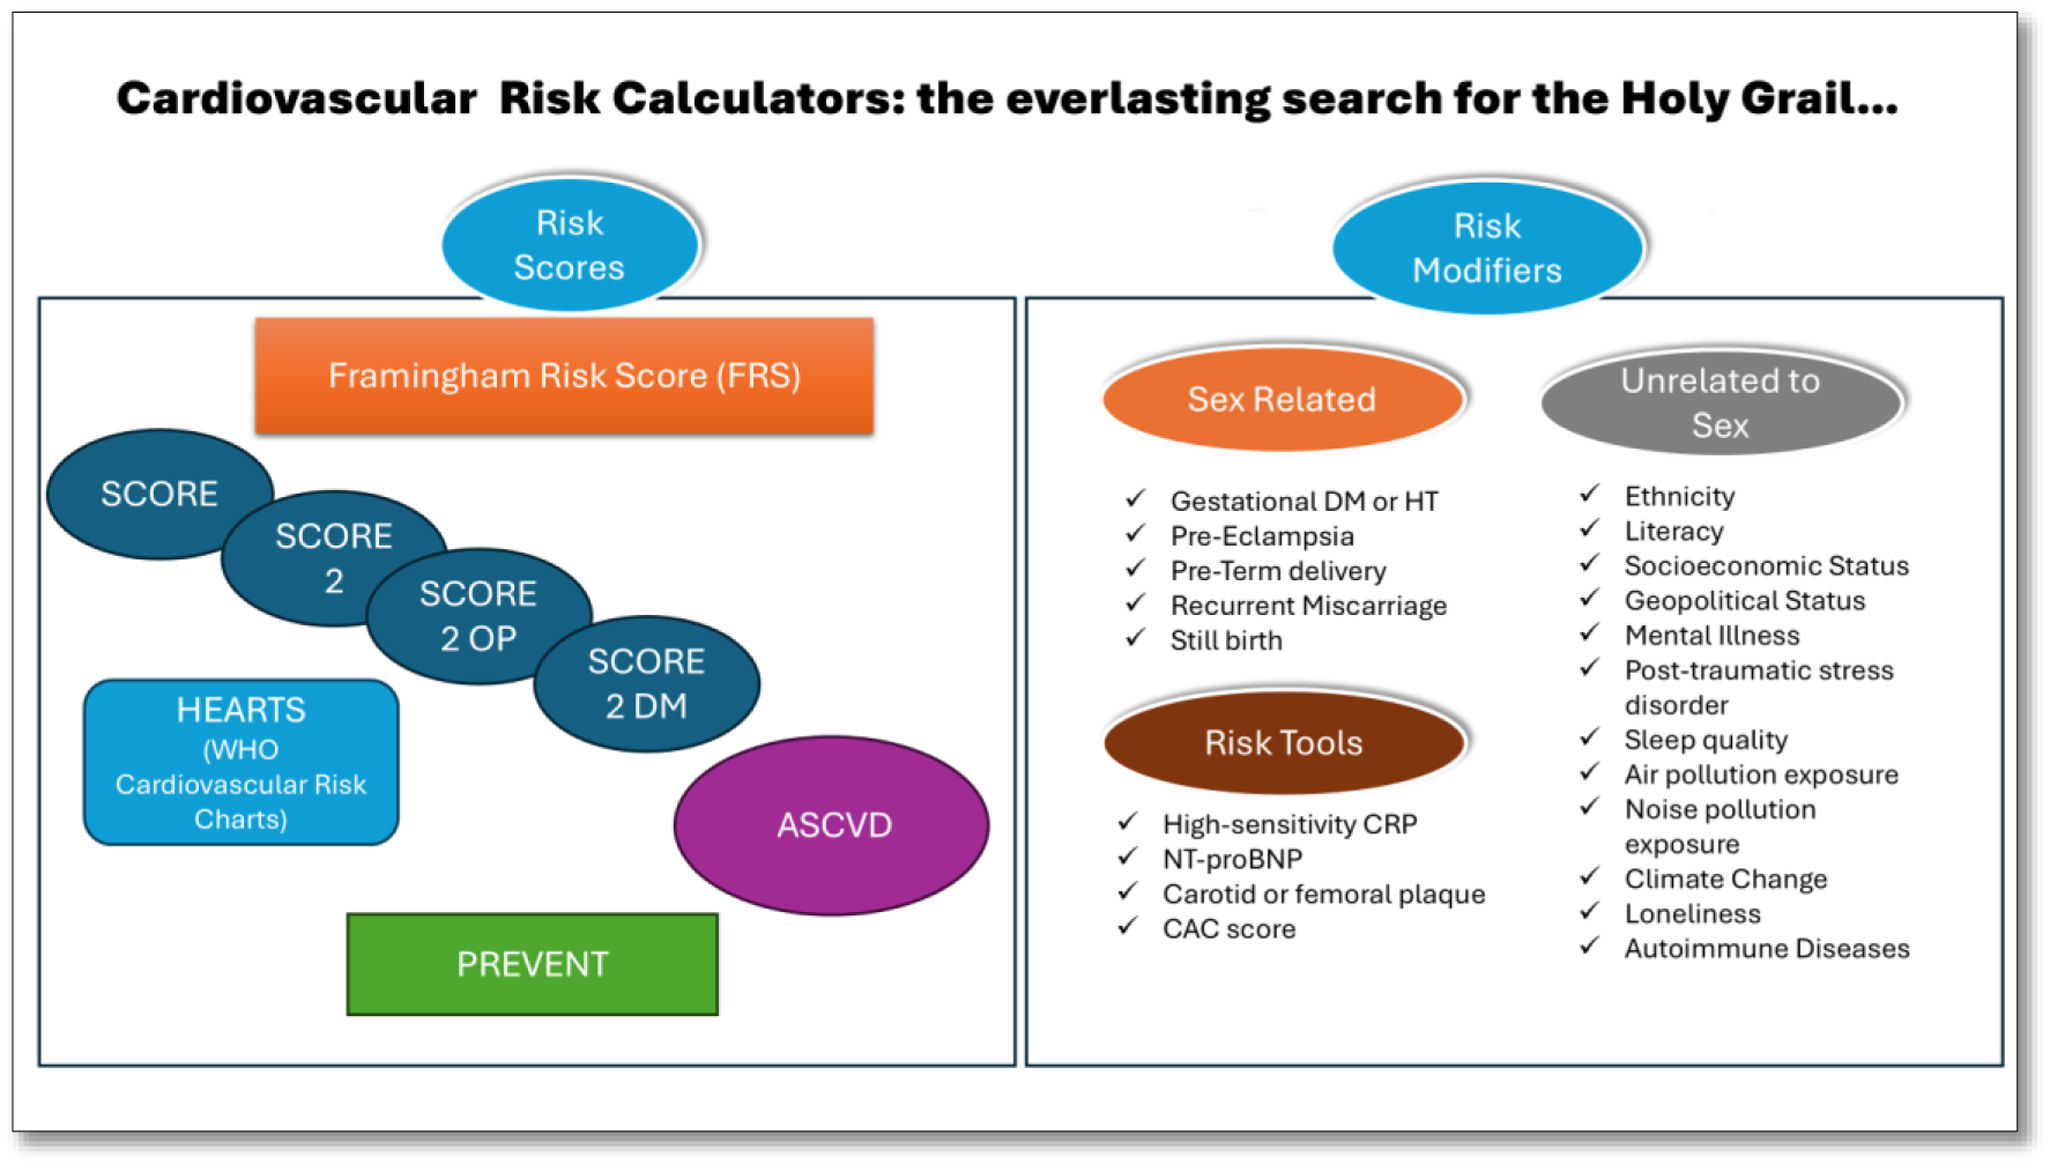
However, our understanding of the importance of many risk factors has changed significantly over time, yet risk calculators do not take this into account. Therefore, the concept of “risk modifiers” has become an important trend in the recent European Society of Cardiology guidelines12–14 (particularly for hypertension and dyslipidemia). The risk modifiers (see Figure 1) aim to incorporate new risk factors (psychosocial, immune and sex-related factors) to guide risk assessment decisions and inform subsequent therapeutic approaches. Here the North American Prevent Score15 (itself an update for the ASCVD calculator16) comes into play, enabling the direct use of, for example, the “social context”. It is accepted in several regions, including in the recent Brazilian Hypertension guidelines.17

Risk modifiers also aim to incorporate information from the growing availability of cardiovascular biomarkers – especially imaging markers (see Figure 1) – which are not included in standard risk calculators. They try to help the physician decide, for example, if the patient should start preventive aspirin (now recommended for secondary prevention18) in a patient presenting discernible, although nonsignificant, atherosclerotic plaques in carotid arteries, or with a high coronary calcium score, as a preventive measure. This is one of the most pressing questions at hand, prompting, in any case, the wider and more tailored use of dyslipidemia treatments, as claimed by the work under scrutiny.
This study has some limitations, beginning with the use of data from a single health center. Nevertheless, it once again demonstrates the importance of public health data, which are now widely accessible in Portugal. The recommendation is to update SCORE to SCORE2 Diabetes, to be used in patients with diabetes within the health centers’ software package. In some way, this paper from a single primary care unit demonstrates the importance of the update. The work also stresses the underutilization of lipid lowering therapy, something that is widely acknowledged,19 demonstrating that in many aspects the authors should be praised.
In conclusion, cardiovascular risk calculators are important for proper risk management of chronic diseases, but I am also sure that other points need to be addressed. The most important of these is easy access to a family doctor, with sufficient time for consultations, and, of course, the physician's own awareness of the importance of curbing cardiovascular risk. It is also important to provide patients with ample information about the risks of serious diseases such as diabetes and other lifestyle-related illnesses, which are clearly on the rise in our predominantly urban society. These objectives do not depend on doctors alone, but rather on public health policy focused on prevention. This is much cheaper than treatment, thus avoiding patient non-adherence to treatment and doctor inertia – which is still very common among us.
Conflicts of interestThe author has no conflicts of interest to declare.



