



This national expert consensus statement, endorsed by the Portuguese Association of Interventional Cardiology of the Portuguese Society of Cardiology (APIC-SPC) and the Portuguese Society of Hypertension (SPH), provides practical guidance on the appropriate use of renal denervation for blood pressure management in adults with uncontrolled hypertension in spite of optimally tolerated guideline-directed therapy and lifestyle measures. It synthesizes evidence from contemporary sham-controlled trials and large real-world registries, which show sustained blood pressure reductions with both radiofrequency and ultrasound systems, and a favorable and consistent safety profile, while acknowledging remaining uncertainties in long-term clinical outcomes and individual response prediction. The document emphasizes rigorous patient selection within a structured pathway coordinated by multidisciplinary hypertension teams. It outlines organizational requirements for centers performing renal denervation, key elements of pre-procedural imaging and peri-procedural management, and a standardized follow-up strategy using office, home, and ambulatory monitoring to enable timely therapy adjustment. Beyond resistant hypertension, this statement discusses carefully selected scenarios in which RDN may be considered as an adjunctive option, while reinforcing that renal denervation is not first-line therapy and should be integrated into a comprehensive hypertension care. This consensus aims to clarify for which patients renal denervation may be a viable therapeutic option, identify the main clinical and procedural considerations for its implementation, and promote its optimal and safe use through appropriate patient selection and multidisciplinary evaluation.
Este documento nacional de consenso, desenvolvido em colaboração com a Associação Portuguesa de Intervenção Cardiovascular da Sociedade Portuguesa de Cardiologia (APIC-SPC) e com a Sociedade Portuguesa de Hipertensão (SPH), fornece orientações práticas sobre a utilização adequada da desnervação renal no controlo da tensão arterial em adultos com hipertensão não controlada, apesar de terapêutica médica otimizada e da adoção de medidas de estilo de vida. O documento sintetiza a evidência proveniente de ensaios clínicos contemporâneos com grupo de controlo (sham-controlled trials) e de grandes registos do mundo real, que demonstram reduções mantidas da tensão arterial, tanto com sistemas de radiofrequência como de ultrassons, mantendo um perfil de segurança favorável e consistente, e reconhecendo que permanecem incertezas relativamente aos resultados clínicos a longo prazo e à previsão da resposta individual. O documento destaca a importância de uma seleção rigorosa dos doentes, enquadrada num percurso estruturado e coordenado por equipas multidisciplinares dedicadas à hipertensão. São descritos os requisitos organizacionais dos centros que realizam desnervação renal, os elementos essenciais da avaliação pré-procedimento e da abordagem peri-procedimento, bem como um plano de seguimento baseado em medições no consultório, no domicílio e em monitorização ambulatória, permitindo o ajuste atempado da terapêutica anti-hipertensora. Para além da hipertensão resistente, são discutidos cenários específicos em que a desnervação renal pode ser considerada como uma opção terapêutica adicional, reforçando que a mesma não constitui uma terapêutica de primeira linha e deve ser integrada numa abordagem global do tratamento da hipertensão. Este consenso tem como objetivo clarificar em que doentes a desnervação renal pode constituir uma opção terapêutica viável, identificar os principais aspetos clínicos e técnicos para a sua implementação e promover uma utilização segura e otimizada através de uma seleção adequada dos doentes e de uma avaliação multidisciplinar.
High blood pressure (BP), one of the most important global health concerns, remains the most prevalent risk factor for cardiovascular (CV) diseases. Approximately 46% of adults are unaware of their condition.1,2 In Portugal, the prevalence of hypertension has been estimated at around 42% of adults, of which only 43% are controlled.3
Many factors contribute to poor BP control, such as environmental, societal, biological and patient-related factors, especially poor treatment adherence. These factors all need to be addressed when dealing with difficult-to-control hypertension. Resistant hypertension affects approximately 10% of treated patients with hypertension. This subset of patients is at an increased risk of adverse CV events, which highlights the need for alternative therapeutic approaches.4
Transcatheter renal denervation (RDN) has emerged as a promising treatment for resistant hypertension, by targeting the renal sympathetic nervous system (SNS) tonus and aiming to readjust neurogenic influence on BP elevation. SNS activity plays an important role in BP regulation and is increasingly recognized in current antihypertensive treatment strategies. It is highly variable and affects the function of several organs beyond the heart, such as the kidney, via efferent and afferent sympathetic pathways, and therefore modulating the renin–angiotensin–aldosterone system, the sodium retention and vascular resistance.5 RDN aims to favorably modulate the nerve traffic in this ceaseless loop, offering a non-pharmacological option for BP control.
Renal denervation has faced considerable challenges over the past 15 years. Short- and long-term efficacy and safety have been proven by a sequential set of well designed, rigorous, randomized, sham-controlled trials, addressing a large number of patients, mainly with resistant hypertension or without ongoing antihypertensive medication, applying different sources of energy to SNS renal nerves.
Trials with second generation RDN systems addressed some of the methodological limitations and flaws of earlier studies,6,7 by introducing more advanced catheters capable of circumferential ablation, tighter procedural protocols and carefully controlled medication regimens. Systems exist that apply radiofrequency (RF) energy, simultaneously, via multielectrode catheters, to thermally ablate sympathetic nerve traffic that surround the renal vasculature (Symplicity Spyral System, Medtronic) or ultrasound (US) energy to the renal artery via an inflated balloon (Paradise System, Recor Medical). The Peregrine System (Ablative Solutions), with less published clinical data, delivers small amounts of alcohol, via microneedles that puncture the renal artery wall.8
The Spyral HTN-OFF MED9,10 and ON MED11 trials showed significant and consistent reductions of BP in RDN arms, both in patients free from medication and in those on anti-hypertensive regimens. These trials demonstrated efficacy in reducing ambulatory systolic BP between 4 and 7.5 mmHg. The Global Symplicity Registry (GSR Define),12 a large-scale, prospective, real-world registry, which included over 3000 patients worldwide, has provided complementary effectiveness and safety data, showing sustained BP reductions beyond 36 months, with minimal adverse events. This research shows that RDN is most effective when multi-level, circumferential ablations are performed, which is consistent with previous studies that recommend the delivery of RF energy in both the main artery and branches, to derive maximum benefit and achieve greater reductions in sympathetic activity.13
The Radiance Trials, using the Paradise System, were also performed in patients free from medication (RADIANCE-HTN SOLO and RADIANCE II) and on anti-hypertensive regimens (RADIANCE-HTN TRIO). They also showed significant reductions in mean ambulatory SBP between 4 and 6 mmHg.14–16
Collectively, these trials position RDN as a safe therapeutic option. It is effective, particularly in patients with moderate hypertension, equivalent to one potent medication. Nevertheless, despite its efficacy, patients are unlikely to become medication free.17
Regarding treatment effect durability, long-term RDN data from registries support the sustained efficacy of the procedure in managing resistant hypertension. A non-controlled single-center 10-year follow-up study demonstrated significant and durable reductions in 24-hour ambulatory systolic BP, with an average decrease of 16 mmHg.18 The body of evidence available at this point supports that RDN, whether with RF or US energy, lowers BP when compared to placebo, demonstrating benefit across a range of hypertensive phenotypes and with favorable safety outcomes. However, it should be emphasized that, in current ESC and ACC/AHA guidelines, RDN carries a Class IIb recommendation,19,20 reflecting modest BP reductions without demonstrated impact on hard cardiovascular outcomes and persisting uncertainties regarding long-term durability and response in specific subgroups.
This consensus document does not aim to replicate existing international guidelines. Instead, it seeks to clarify which patients may benefit from RDN, to outline the key considerations for its implementation, and to promote its appropriate use to improve hypertension control through careful patient selection. To this end, we advocate the establishment of multidisciplinary teams to assess all patients before a decision is made regarding RDN.
This document was developed through structured interdisciplinary discussion among representatives formally appointed by APIC-SPC and SPH, followed by institutional review and endorsement by both societies.
Patient selectionResistant hypertensionResistant hypertension has historically represented the main indication for RDN. It is defined as BP above guideline-recommended targets, despite concurrent use of three or more antihypertensive agents at maximum tolerated doses, including a renin–angiotensin system blocker, a calcium channel blocker, and a diuretic.19–21
Resistant hypertension is more frequent in men, black patients, and in association with obesity, diabetes, and chronic kidney disease.22 Inadequately treated resistant hypertension is linked to increased risk of hypertension-mediated organ damage and major CV events, including heart failure, ischemic heart disease, stroke, and renal failure.4,23
Estimated prevalence of resistant hypertension varies widely due to heterogeneous definitions, diverse populations, and incomplete exclusion of pseudo-resistance.24 After rigorous exclusion of pseudo-resistance, the true prevalence is approximately 10% of hypertensive patients treated.25 Distinguishing true resistant hypertension from pseudo-resistant hypertension highlights the importance of referring these patients to specialized hypertension centers with coordinated and multidisciplinary teams.23,26
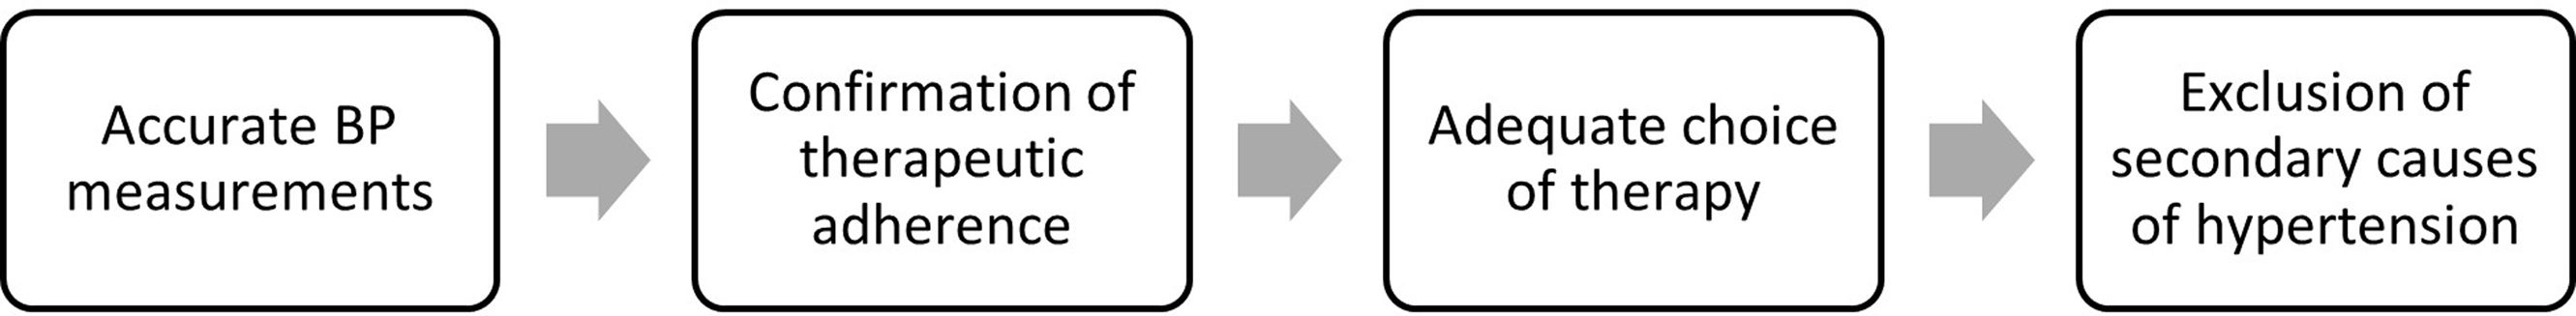
Figure 1 represents a proposed 4-step pathway for the diagnosis of true resistant hypertension.
- a.
Accurate BP measurements

An accurate diagnosis of resistant hypertension depends on proper measurement techniques with adequate patient preparation and use of validated devices with appropriate cuff size,26 as outlined in the 2021 ESH practice guidelines for office and out-of-office BP measurement.27 Exclusion of white-coat phenomenon through out-of-office BP measurements with 24-hour ambulatory BP monitoring (ABPM) (gold standard when available) and home BP monitoring is recommended.23,26,28
- b.
Confirmation of therapeutic adherence
Partial or total non-adherence to therapy is a common and a major cause of uncontrolled BP, which consequently leads to increased CV risk.4,24 Adverse drug reactions are a frequent cause of therapeutic discontinuation and should be routinely assessed and promptly addressed.23,26
Several direct and indirect methods are available for assessing adherence, none of which are considered gold standard as they all have advantages and limitations.25 Indirect methods are relatively inexpensive and easy to implement. They include questionnaires, pill count, prescription refill rates, and electronic medication monitors. These methods are prone to report and interpretation bias. Direct methods show higher sensitivity and include monitoring of metabolites of anti-hypertensive drugs in biologic fluids (serum or urine). However, they are expensive and not feasible in most clinical settings.20,29 It may be appropriate to use an indirect method as a screening test followed by a direct method when available.30
- c.
Adequate choice of therapy
Another reason for suboptimal BP control that clinicians should consider is therapeutic inertia which leads to the prescription of insufficient drug doses, lack of up-titration or use of ineffective drug associations.4
Optimizing antihypertensive medicationIn the treatment of hypertension, five major drug classes are considered to be first-line agents: angiotensin converting enzyme inhibitors (ACEI), angiotensin receptor blockers (ARB), calcium channel blockers (CCB), thiazide/thiazide-like diuretics (T/TLD) and beta-blockers (BB).
In most patients, antihypertensive treatment should be initiated with dual combination therapy and should be titrated to triple therapy if needed. In this case, an ACEI or ARB, a CCB and a T/TLD should be used. BBs should be used as a first-line choice in the presence of specific indications for their use, such as coronary artery disease, heart failure with reduced ejection fraction or atrial fibrillation. Regarding T/TLD, chlorthalidone and indapamide are more potent and have a longer duration of effect than hydrochlorothiazide. In the setting of an estimated glomerular filtration rate (eGFR) <30 ml/min/1.73 m2, they should be replaced by loop diuretics. Chlorthalidone may be effective with an eGFR between 15 and 30 ml/min/1.73 m2 either alone or in association with a loop diuretic.31 Single-pill combinations that include drugs with long half-lives (allowing for once-daily administration) should be preferred to promote adherence to therapy. The association of an ACEI and an ARB should be avoided.
If BP is not controlled with three drugs at the maximum recommended and tolerated dose, the fourth-line choice should be spironolactone.32 If such treatment is not effective, other drug classes may be used, such as BBs (if not used before), alpha-1 blockers and centrally acting drugs. Emerging pharmacological strategies, including sodium–glucose cotransporter-2 inhibitors, glucagon-like peptide-1 receptor agonists, non-steroidal mineralocorticoid receptor antagonists, aldosterone synthase inhibitors, and endothelin receptor antagonists, may further refine the management of difficult-to-control BP; however, their role in resistant hypertension requires further evidence and is beyond the primary scope of this document.
Exclusion of secondary causes of hypertensionSecondary hypertension is often associated with resistant hypertension.4 Although a detailed review of the diagnosis of secondary causes of hypertension is beyond the scope of this document, their study in patients with resistant hypertension is important. Early detection of secondary hypertension enables prompt intervention aimed at correcting the cause of hypertension and thus preventing irreversible organ damage.24 Particular attention should be given to the identification of primary or secondary hyperaldosteronism, given its vital role in treatment resistance.
Certain medications may also elevate BP. Common examples are nonsteroidal anti-inflammatory drugs (NSAIDs), combined oral contraceptives, hormone replacement therapy, decongestants, recombinant erythropoietin, immunosuppressive drugs, and chemotherapy (tyrosine kinase inhibitors, calcineurin inhibitors and vascular endothelial factor inhibitors).33 The use of recreational substances such as alcohol, tobacco, cocaine, and amphetamines is also implicated in BP elevation and should be considered in high suspicion cases.20
Broadening the use of renal denervationWhile resistant hypertension remains the most established indication, recent consensus documents and guidelines consider potential roles of RDN beyond this group, including:
- -
Patient preference – in patients with mild to moderate hypertension who are unwilling to initiate drug treatment, RDN may be considered. However, it must be stressed that trials performed without adjunctive drug treatment showed that BP improved but was not controlled with RDN alone.9,14,15
- -
Patients with established CV disease and very high CV risk were excluded from most recent trials; however, recent guidelines and consensus documents have advocated the use of RDN in these patients, based on expert opinion.34,35
- -
Patients whose BP remains uncontrolled while being treated with <3 drugs, because they are intolerant or unwilling to add other drugs, may benefit from RDN as an adjunctive option, after shared risk–benefit discussion.19,21
It is important to emphasize that RDN should be considered an adjunctive therapy for BP lowering, not a first-line intervention, and only after guideline-directed lifestyle and pharmacological measures have been optimized. Contraindications include severe renal dysfunction (eGFR <40 mL/min/1.73 m2), active secondary hypertension, and unfavorable renal artery anatomy.
Preparation and referral of patientsAppropriate preparation and referral are essential to ensure that RDN is performed safely, effectively, and in patients most likely to benefit. Careful patient selection, guided by standardized diagnostic pathways and therapeutic optimization, must be coordinated by specialized teams. This process minimizes unnecessary procedures, improves treatment outcomes, and guarantees that RDN is embedded within a comprehensive hypertension management program.
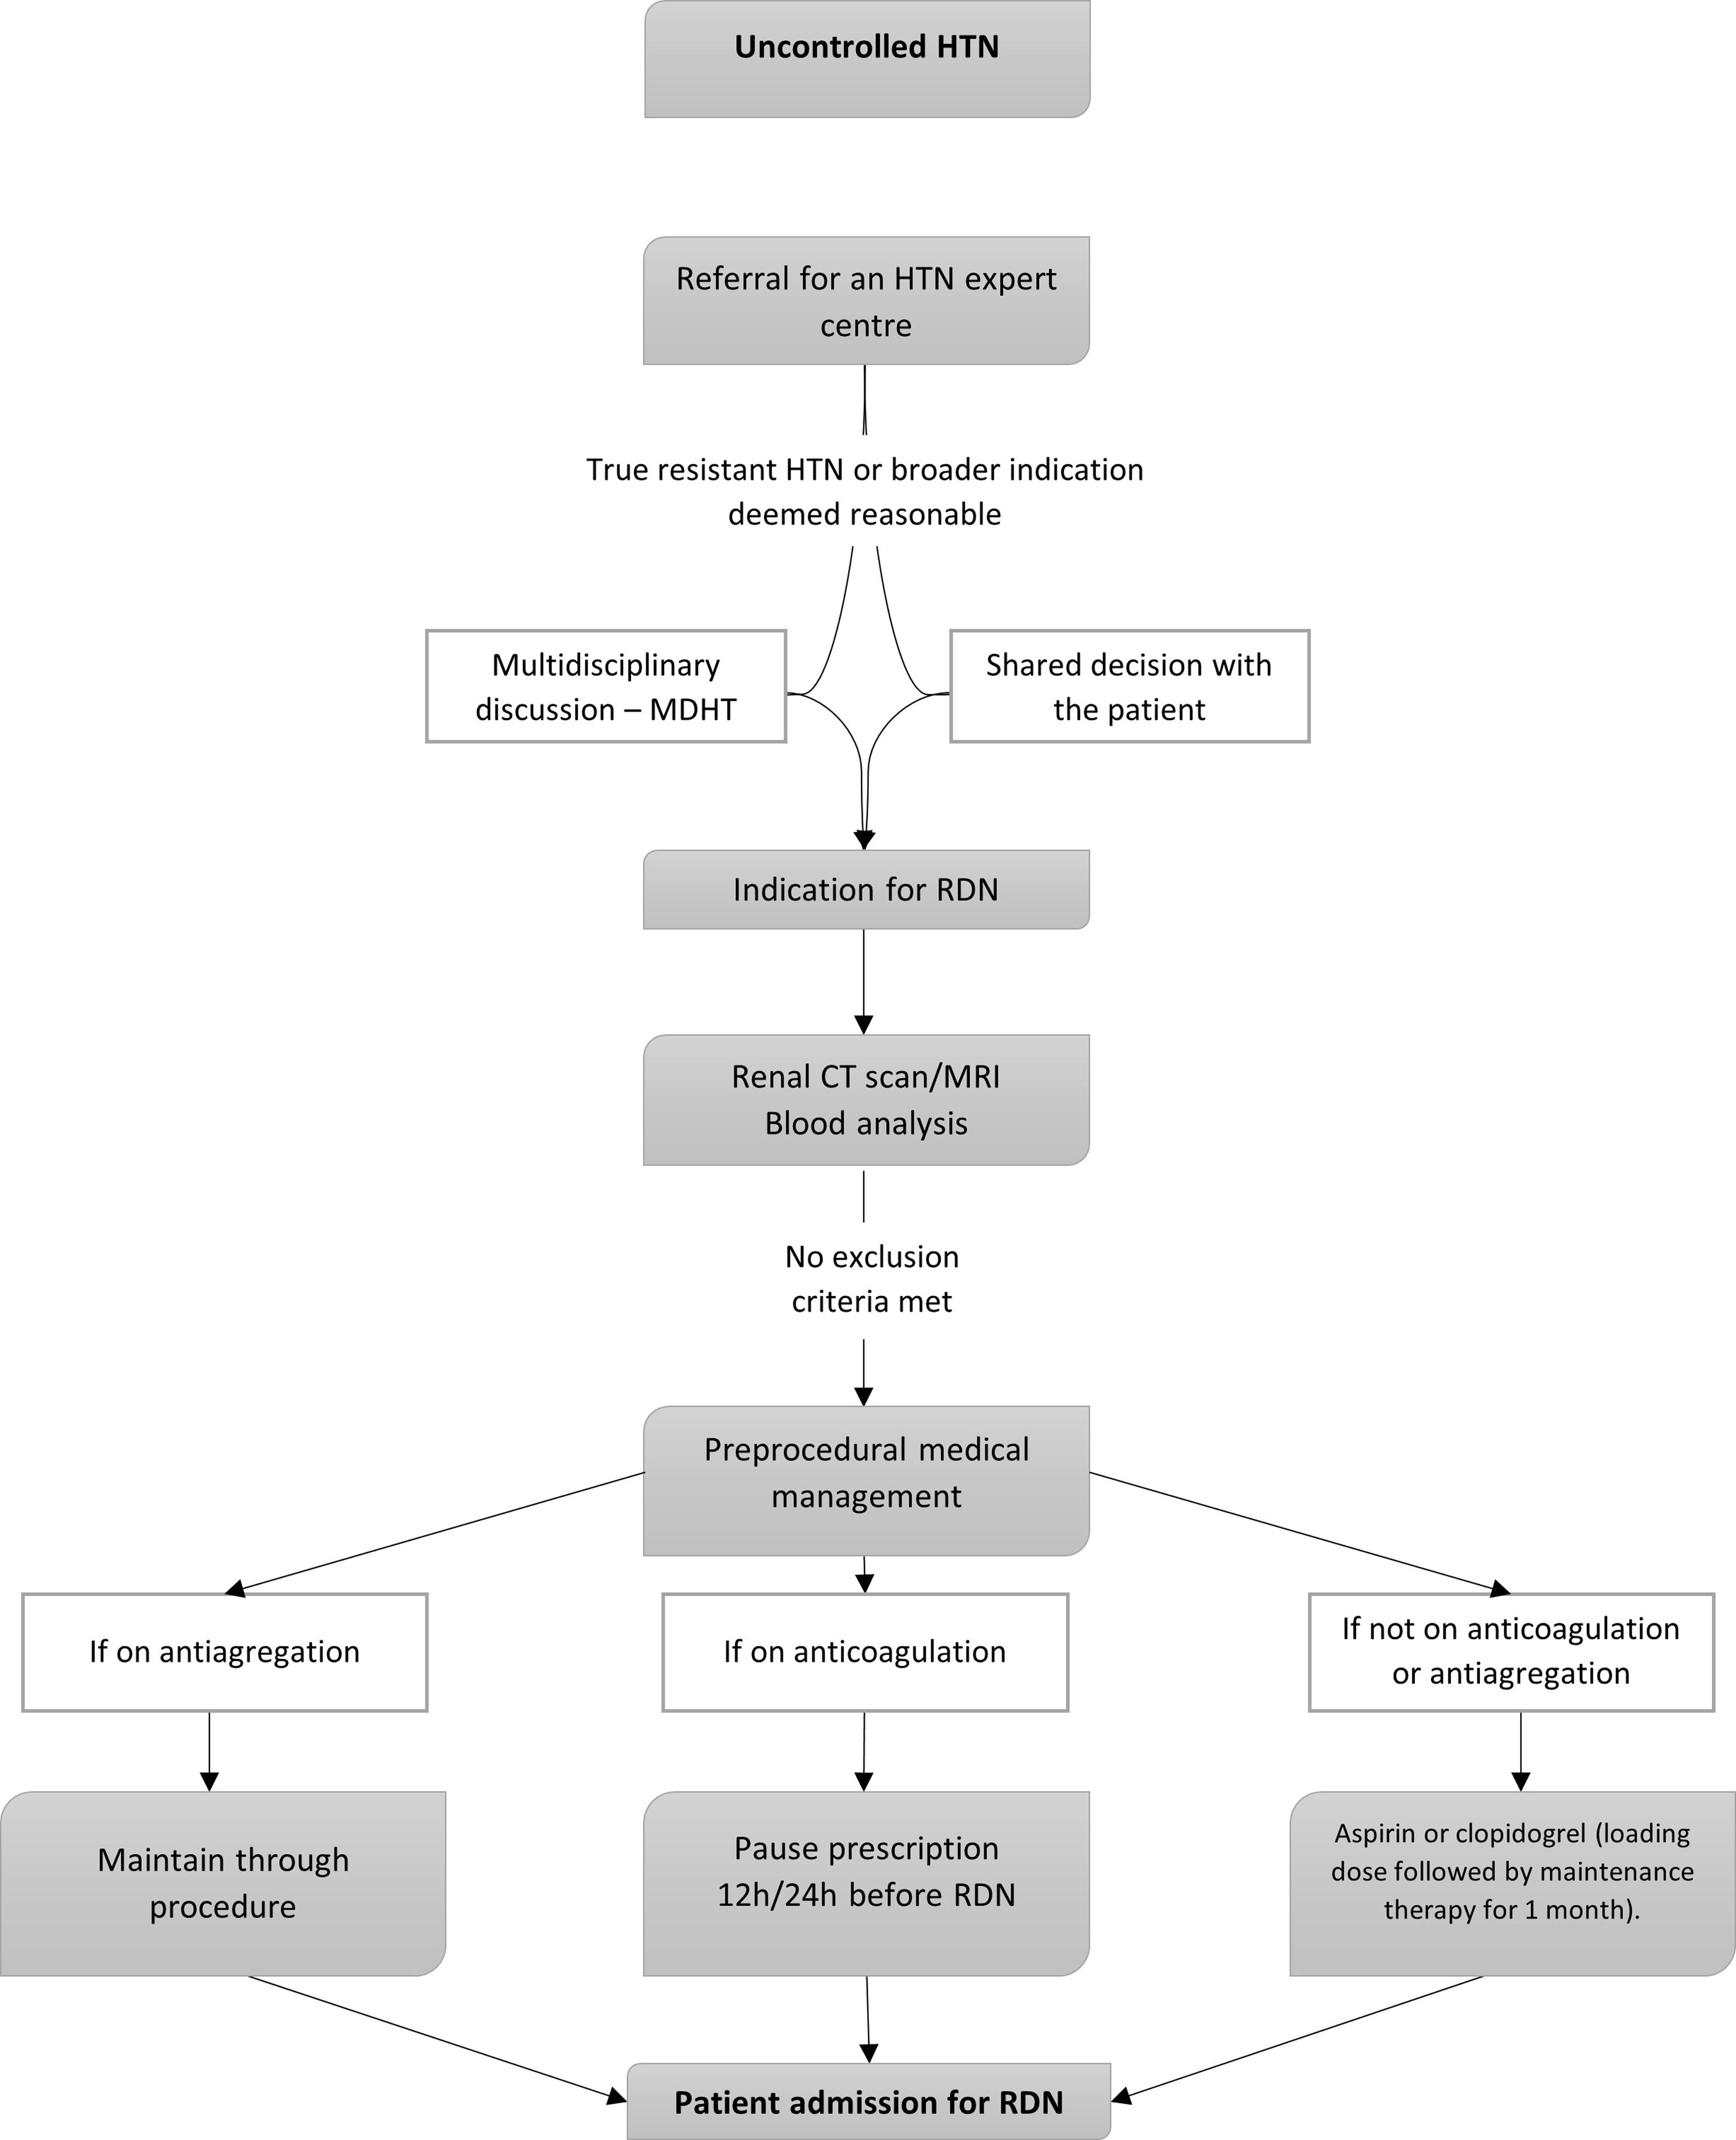
Figure 2 represents a flowchart summarizing the recommended pathway from the diagnosis of resistant hypertension to referral and preparation for RDN.

Renal denervation programs should be overseen by multidisciplinary hypertension teams and ideally take place in hypertension excellence centers, recognized by the European Society of Hypertension (ESH).21,34 Alternatively, they may be implemented in hospitals, where it is possible to build teams that include both hypertension specialists and experts in percutaneous CV interventions, provided the institution has at least:
- a.
A dedicated hypertension outpatient clinic and an inpatient ward;
- b.
A radiology department;
- c.
Clinical and hormonal laboratory facilities;
- d.
Access to 24-hour ABPM devices;
- e.
Access to a cardiac catheterization laboratory (Cath Lab);
- f.
A coronary care unit or intensive care unit;
- g.
Immediate or guaranteed access (onsite or remote) to vascular surgery in case of an emergency.19,34,36
Hypertension specialists should be formally recognized by accredited bodies, such as the ESH, and bear primary responsibility for patient selection. Their role includes confirming the diagnosis of uncontrolled hypertension, ensuring optimization of antihypertensive therapy, excluding secondary causes when appropriate, and verifying that the patient meets the eligibility criteria for RDN as defined in this consensus. No patient should be referred for RDN without prior evaluation by a hypertension specialist.
Interventionalists are responsible for performing the procedure itself and must therefore be highly skilled and specifically trained in RDN to minimize the risk of complications. Depending on the institutional setting or healthcare system, the multidisciplinary hypertension teams may also include a clinical cardiologist and/or a nephrologist.34
The multidisciplinary hypertension teams should provide patients with clear and objective information regarding RDN: risks and benefits, realistic expectations of BP reduction based on current scientific evidence, and the existing limitations, including the absence of long-term data on drug-free persistence after RDN and the inability to reliably predict individual clinical response. In cases where the multidisciplinary hypertension teams identify eligible patients but lacks a structured RDN program with adequately trained interventionalists, referral to an experienced center is recommended.36
The multidisciplinary hypertension teams should meet regularly to review complex cases and to update protocols or indications for RDN and related management strategies. Furthermore, the multidisciplinary hypertension teams have an essential role in the clinical follow-up of patients undergoing RDN, encompassing both assessment of BP response and adjustment of antihypertensive therapy, as well as surveillance for potential adverse events.
Referral processAs the eligibility criteria for RDN are defined by the multidisciplinary hypertension teams, the formal referral should preferably be made by a hypertension specialist. Nevertheless, any healthcare professional involved in the care of hypertensive patients may initiate the process by identifying potentially eligible individuals and referring them to a dedicated hypertension clinic.
Renal denervation procedurePatients being considered for RDN should undergo a thorough preprocedural assessment to determine eligibility, ensure safety and optimize procedural outcomes.
Preprocedural evaluation and managementAfter the previous steps are completed, the following course of action is strongly recommended:
- a.
Ensure anatomical and functional renal appropriateness for RDN through imaging assessment and laboratory evaluation.
- i.
It is highly recommended to obtain prior imaging of the renal arteries, in addition to the renal doppler US such as contrast-enhanced renal computed tomography (CT) or magnetic resonance (MRI).
- ii.
Full blood count and biochemistry profile.
- -
Correct electrolyte abnormalities, especially hypokalemia.
- -
Assess baseline renal function.
- -
- i.
- b.
Inclusion and exclusion criteria
- i.
Renal artery length ≥20 mm (RF system) or ≥25 mm (US system).
- ii.
Renal artery diameter ≥3 and ≤8 mm.
- iii.
Absence of significant stenosis, fibromuscular dysplasia or single functioning kidney.
- iv.
In the presence of renal artery stents – avoid ablation in stented segments, a distance of at least 5 mm between the stent struts and any ablation point is recommended.
- v.
In the presence of renal aneurysm, atheroma or calcification – distance of at least 5 mm between the abnormality and any ablation point is recommended.
- vi.
eGFR ≥40 mL/min/1.73 m2 (threshold may vary by protocol and device).
- i.
- c.
Multidisciplinary decision-making
- i.
Review of the case by a multidisciplinary hypertension team, including experts in hypertension and in percutaneous cardiovascular interventions.
- ii.
Shared decision-making with the patient.
- -
Discuss the mechanism, expectations, and alternatives.
- -
Ensure understanding of the need for continued BP monitoring and probable ongoing medications.
- -
- i.
Appropriate patient preparation is essential to ensure safety, procedural success and an optimal recovery following RDN. The following steps are strongly recommended:
- a.
Fasting and hydration
- i.
Fasting for a minimum of six hours prior to the procedure.
- ii.
Ensure adequate hydration to minimize the risk of contrast-induced nephropathy.
- i.
- b.
Informed consent and patient education
- i.
Provide clear information on the benefits and potential risks associated with RDN.
- ii.
Obtain signed informed consent from the patient.
- iii.
Emphasize the importance of post-procedural follow-up.
- i.
- c.
Medication management
- i.
Pre-procedural
- -
Aspirin loading dose followed by 100 mg per day for one month. Consider clopidogrel (loading dose followed by 75 mg per day for one month) if aspirin allergy or intolerance.
- -
Oral anticoagulants should be paused according to their pharmacokinetics. Bridging is not typically necessary unless specific indications are present (e.g., mechanical prosthetic valves).
- -
Prophylactic antibiotics are not generally recommended.
- -
- ii.
Peri-procedural
- -
RDN can be performed under conscious sedation (low doses of opioids and benzodiazepines such as propofol/midazolam) or general anesthesia. The presence of an anesthesiologist is recommended to ensure appropriate pain management during the procedure, according to institutional protocols.
- -
Consider using diluted contrast dye in all patients, but especially in those with impaired renal function.
- -
Administer intravenous or intra-arterial unfractionated heparin to achieve an activated clotting time of >250 seconds.
- -
- i.
- d.
Vascular access planning
- i.
Perform a physical examination of the vascular access site.
- ii.
Prepare the right or left groin area (trichotomy, disinfection).
- i.
The following steps are recommended to optimize the technical performance of RDN and can be applicable to both RF- and US-based systems.
- a.
Patient positioning and monitoring
- i.
Initiate vital signs and continuous electrocardiogram (ECG) monitoring.
- ii.
Obtain an intravenous line for sedation, fluid management and emergency drugs.
- iii.
Administer peri-procedural medication as previously described.
- i.
- b.
Vascular access
- i.
Common femoral access is preferred. It is strongly recommended to puncture under US guidance.
- ii.
Radial-compatible RDN systems are under development and may become available in the near future, potentially reducing vascular access-related complications and further enhancing procedural safety.
- iii.
Insert a 6 (RF system) or 7 French (US System) introducer sheath and administer heparin as described.
- i.
- c.
Renal artery cannulation and imaging
- i.
Perform an aortography to document the location and anatomy of the main renal arteries.
- ii.
Perform selective angiography of the renal arteries using a 55 cm guiding catheter (Internal mammary artery, Amplatz, Multipurpose, RDN-1 and RDC shapes can be used). Antero-posterior, left anterior oblique or right anterior oblique projections are the most used.
- i.
- d.
Renal denervation
- i.
Advance a non-hydrophilic 0.014″ guidewire to the distal segment of the renal artery, keeping the tip always in view.
- ii.
Over the guidewire, advance the ablation catheter to the distal segment of the renal artery or into any of its branches eligible for treatment.
- iii.
Start the ablation from the distal segment of the renal arteries or any branches eligible for treatment. Avoid delivering energy within the renal parenchyma.
- iv.
RF RDN: Advance the multipolar RF catheter into the distal part of the renal artery and perform ablation in multiple segments, ensuring circumferential coverage.
- v.
US RDN: Advance the balloon catheter into the main renal artery, proximal to the distal branches, and ensure full apposition to the artery wall when inflated. Perform 2–3 energy deliveries from distal to proximal.
- vi.
Repeat the procedure in the contra-lateral renal artery and in any accessory renal arteries that meet the anatomical and technical criteria for RDN.
- vii.
It is strongly recommended to administer intra-arterial vasodilators (e.g., nitrates) to avoid renal artery spasm.
- i.
- e.
Final angiography and access site closure
- i.
Perform a final selective renal angiogram to confirm vessel patency and exclude complications (thrombosis, dissection, perforation, etc.).
- ii.
Use of a vascular closure device is recommended, according to operator experience.
- i.
Post-procedural care, following RDN, focuses on early complication detection, a prompt recovery and assuring long-term surveillance.
- a.
Immediate and in-hospital post-procedure assessment
- a.
The patient should remain in the supine position for at least 3–4 hours after the procedure, to ensure adequate hemostasis.
- b.
Check the vascular access site every 15–30 minutes for the first 2 hours. Assess for signs of complications such as bleeding, swelling, hematoma, pain disproportionate to local findings (suggesting retroperitoneal bleeding), or color/temperature changes in the distal limb (suggesting jeopardy of arterial distal flow).
- c.
Overnight stay for continuous ECG monitoring, vital signs evaluation and vascular access vigilance. Watching for hypotension or tachycardia as early indicators of bleeding, is recommended.
- d.
Mild flank or abdominal discomfort is common and usually self-limited – treat with NSAIDs or acetaminophen if necessary. Suspect a rare complication in the presence of sudden and/or severe pain and manage accordingly.
- e.
Reassess renal function and hemoglobin within 24 hours. In patients at risk of contrast-induced nephropathy, repeat renal function assessment 48–72 hours after contrast administration.
- f.
Resume the patient's anti-hypertensive regimen promptly, as BP response to RDN is not immediate in many patients.
- a.
- b.
Discharge
- a.
The patient may be safely discharged if:
- i.
Hemodynamically stable.
- ii.
No access-site related complications.
- iii.
Tolerating oral intake and mobilizing independently.
- iv.
Renal function within acceptable range.
- i.
- b.
Prescribe Aspirin 100 mg per day for 2–4 weeks (or clopidogrel 75 mg per day, 2–4 weeks, if aspirin allergy or intolerance).
- c.
Adjust anti-hypertensive medication if excessively low BP. Otherwise, maintain the same therapeutic regimen.
- a.
Follow-up has not yet been fully standardized, but recommendations have been produced based on major clinical trials and recent consensus statements. It should be performed by a multidisciplinary team, similar to the one responsible for patient selection.
- a.
Clinical assessments are recommended at 1, 3, 6, and 12 months after the procedure, and annually thereafter to evaluate response to treatment, adjust therapy, and reinforce adherence.36
- b.
BP monitoring:
- a.
Office BP measurement at each visit.
- b.
Home BP monitoring regularly.
- c.
ABPM at 6 and 12 months. Annually thereafter.
- a.
- c.
Renal function and laboratory tests:
- a.
Assess serum creatinine, potassium, and eGFR at the scheduled follow-up visits.
- a.
- d.
Symptoms and adverse events:
- a.
Monitor for new or worsening symptoms, including abdominal or flank pain, urinary changes, or other procedure-related events.
- a.
- e.
Medication adjustment:
- a.
Review and titrate antihypertensive therapy as appropriate, aiming for guideline-directed targets.
- a.
- f.
Imaging
- a.
Consider renal US at 6 and 12 months to evaluate for possible renal artery stenosis.
- a.
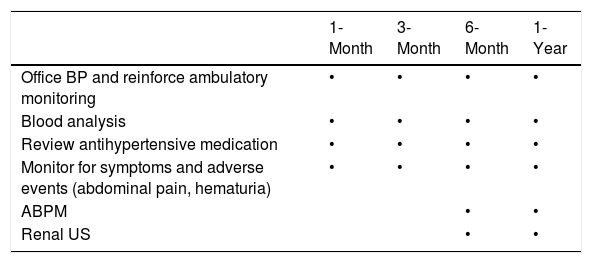
Table 1 outlines the recommended follow-up visits after RDN.
Follow-up schedule after renal denervation.
| 1-Month | 3-Month | 6-Month | 1-Year | |
|---|---|---|---|---|
| Office BP and reinforce ambulatory monitoring | • | • | • | • |
| Blood analysis | • | • | • | • |
| Review antihypertensive medication | • | • | • | • |
| Monitor for symptoms and adverse events (abdominal pain, hematuria) | • | • | • | • |
| ABPM | • | • | ||
| Renal US | • | • |
ABPM: ambulatory blood pressure monitoring; BP: blood pressure; US: ultrasound.
An important consideration, when evaluating the long-term efficacy of RDN, is the potential for renal nerve regeneration, or reinnervation, which could impact the durability of BP reduction. Pre-clinical studies are controversial. Research in sheep, for instance, showed evidence of both anatomical and functional reinnervation,37 but other studies identified a growth of disorganized neuromatous tangles, making functional innervation unlikely.38 In human studies, evidence for renal nerve reinnervation is also not clear. Several studies report sustained reductions in BP within the first three years of the procedure, making functional recovery highly unlikely, at least during this period.39 However, there are instances where patients experienced a significant initial reduction in BP, following RDN, followed by a return to baseline levels over time. While these cases do not provide direct evidence of nerve regrowth, they raise the possibility that reinnervation may influence long-term outcomes.40 Re-denervation should be considered cautiously and only after a structured re-evaluation by a multidisciplinary hypertension team.
The following criteria may be adopted in the decision-making process to support a second RDN.
- a.
Re-denervation feasibility
- a.
Repeat CT or MRI angiography to:
- i.
Confirm renal arteries patency.
- ii.
Confirm the absence of complications from the prior procedure.
- iii.
Identify untreated accessory renal arteries (missed in the first procedure).
- i.
- b.
Stable renal function (eGFR ≥40 mL/min/1.73 m2)
- a.
- b.
Multidisciplinary team evaluation and patient informed consent.
- a.
The case should be reviewed and discussed by a multidisciplinary hypertension team.
- b.
The patient understands the limited evidence regarding repeat procedure and the uncertainty around efficacy.
- a.
Renal denervation may be considered as a complementary strategy for blood pressure reduction in adults with uncontrolled hypertension. In line with recent European and international consensus documents, RDN should be considered in patients carefully selected by hypertension specialists and validated by a multidisciplinary hypertension team, after confirmation that lifestyle modification and guideline-directed pharmacological therapy have been optimized.
With this APIC–SPH consensus, we aim to standardize referral, patient selection, procedural execution, and follow-up pathways in Portugal. We recommend that RDN be performed preferentially in centers with structured programs and trained interventional operators, ensuring procedural safety and appropriate post-procedure surveillance. The integration of RDN within a multidisciplinary model also guarantees shared decision-making, transparent discussion of expected benefits and risks, and monitoring of long-term outcomes.
Conflicts of interestThe authors have no conflicts of interest to declare.



